Global Health Watch: LEN Access Pathways, NIAID Reorganization, Global Fund Report, NIH Lawsuit

Issue 86

This week’s issue covers developments shaping access to HIV prevention and the future of US biomedical research, including new pathways to accelerate access to lenacapavir for HIV PrEP, calls for greater transparency around a proposed NIAID restructuring, and a new lawsuit challenging NIH’s screening of research grants. With today as the final day to comment on the NIAID proposal, make your voice heard. And read on for a provocative Lancet commentary on the challenges of trying to reform global health architecture.

Lenacapavir Access Pathway

Two new agreements from Gilead Sciences, the developer of lenacapavir, this week could expand access to lenacapavir for HIV PrEP (LEN), both for the current every six month injectable and a potential once-yearly option still in development. Gilead and the Pan American Health Organization (PAHO) announced new steps to establish a procurement pathway through PAHO’s Regional Revolving Funds that will allow 14 countries in Latin America and the Caribbean – including Argentina, Brazil, Peru and Mexico (all of which participated in one of the pivotal efficacy trials) – to procure twice-yearly LEN. This mechanism complements the 24 countries already covered in the region by Gilead’s existing voluntary licensing agreements. Gilead also committed to advance a technology-transfer process in Brazil, although timelines, prices, and volumes were not defined in the release. Separately, Gilead expanded its six royalty-free voluntary licenses for lenacapavir to include the investigational once-yearly formulation being studied in the Phase 3 PURPOSE 365 trial. This would extend once-yearly LEN generic plans for 120 high-incidence, resource-limited countries before efficacy results or regulatory approval.

IMPLICATIONS: These LEN announcements are a step forward in rolling out new HIV prevention options with speed and scale, but equity continues to remain a central issue. Advocacy partners, ITPC Global and Make Medicines Affordable, welcomed the PAHO mechanism as an important step for countries that were initially excluded from Gilead’s voluntary licenses. However, they warned that important details including price, volumes, supply commitments and delivery timelines remain unknown and that governments cannot plan national scale-up without that information.

At the same time, expanding voluntary licenses to the prospective once-yearly formulation while it is still in Phase 3 development is an important step forward in early access planning and could shorten the gap between approval and generic supply, should the once-yearly formulation prove safe and effective. This early licensing approach mirrors Merck/MSD’s recent licensing agreements for their investigational monthly oral PrEP option, alimatravir. AVAC’s projections of potential LEN supply and demand through 2028 illustrate the scale of the opportunity—and the gap that remains between potential demand and current commitments. Whether these two LEN access agreements translate into affordable, predictable supply that countries can actually finance and deliver at scale and speed will be the true test of equity.

READ:

NIAID Reorganization: Last Day for Public Comment 

Advocates led by the Save HIV Funding campaign, founded by PrEP4All, HIVMA and AVAC, are demanding more transparency and a withdrawal of the proposed restructuring of the National Institute of Allergy and Infectious Diseases (NIAID) to allow time for meaningful opportunities for the HIV community to provide input on the reorganization proposal. Last week, the National Institutes of Health (NIH) released a proposed reorganizational chart with public comments due today, September 18. The proposal would eliminate NIAID’s Division of Clinical Research and redistribute clinical research functions across the Institute. Little accompanying detail has been provided about the rationale for the changes, how responsibilities would be reassigned or what the restructuring could mean for NIAID’s domestic and international clinical research infrastructure.  
 
The Save HIV Funding campaign developed a template for comments for individuals and organizations that would like to comment on the NIH proposed reorganization of NIAID.

IMPLICATIONS: The proposed restructuring comes at a particularly uncertain moment for the HIV research infrastructure NIAID has built over decades. The long-delayed announcement for the next seven-year cycle of the trial networks creates the possibility of funding gaps that could disrupt ongoing trials, research sites, staff and study participants; infectious-disease groups have warned that lapses could destabilize research capacity that has contributed to advances across HIV, TB, hepatitis and other infectious diseases. With fundamental questions about the reorganization still unanswered, advocates are pressing NIH not to restructure that system without greater transparency and meaningful community input. The uncharacteristically shortened timeline for public comment and scant details available about the proposed reorganization has been criticized as obfuscating meaningful community engagement and involvement in NIAID processes. Furthermore, NIAID has provided little justification for eliminating pertinent divisions such the Division of Clinical Research – which provides substantial clinical and regulatory support for NIAID-funded studies.  

READ:

Global Fund Releases New Report: Treatment Sustained, Prevention Impacted

The Global Fund to Fight AIDS, TB and Malaria released its 2026 Results Report, which positions sustained progress against all three diseases in 2025 despite the decimation of global health foreign assistance and financing. In Global Fund invested countries, the report shows that 26.9 million people received antiretroviral therapy for HIV, which is an increase from 25.6 million in 2024. However, despite sustainability of treatment, the report also documents the effects on prevention where programs were scaled back or suspended altogether in some countries. Notably, the number of people receiving PrEP in Global Fund-supported countries fell from 1.4 million in 2024 to 1.1 million in 2025

IMPLICATIONS: These findings suggest a similar pattern across recent analyses of the global HIV response, including the recent UNAIDS report and latest PEPFAR data. HIV treatment programs have so far proved relatively resilient to the funding pitfalls, while HIV prevention has been much more severely disrupted. AmfAR’s Brian Honerman and co-authors, Jirair Ratevosian, KFF and AVAC’s own analysis of the latest PEPFAR data, all sound the alarm that the front end of the HIV response is weakening.

READ:

Scientists Sue NIH Over Grant Screening Process 

Seventeen US researchers filed a class-action lawsuit challenging a new National Institutes of Health (NIH) grant-screening process that they say unlawfully allows political considerations to override scientific merit. According to the complaint, NIH is using a computational tool to flag at least 235 terms—including “gender,” “health disparities,” “racist” and “climate change”—in new and existing grants, and in some cases requiring researchers to remove or change flagged language before funding can proceed. The lawsuit alleges that the process violates First Amendment protections against viewpoint discrimination as well as federal requirements governing how NIH awards and terminates grants. They are asking the court to halt the screening policy, restore terminated grants and reconsider applications denied under the process.  

IMPLICATIONS: The lawsuit represents a new legal challenge to the Administration’s efforts to reshape federally funded research. Following the mass grant terminations in early 2025, this evolution of political overstep is being played out in a new way. The 17 researchers argue that requiring scientists to remove terms related to populations or subjects they are studying can alter how research is described and, in some cases, undermine its scientific design. Because this lawsuit is filed as a class action, its implications could extend beyond their specific grants and to researchers around the country affected by the screening policy. This new challenge follows AVAC’s lawsuit, which unlocked the payment of millions of dollars of development assistance for work that was done in January and February 2025. 

READ:

Webinar: What’s Next for bNAbs?

On September 30, join AVAC for a global webinar: Combo bNAbs for HIV Prevention – Latest Developments.

Register

What We’re Reading

All things alimatravir (AMI)

Alimatravir (AMI, known as MK-8527) is an investigational monthly pill being studied for PrEP in the EXPrESSIVE program. The addition of a monthly PrEP pill, if proven safe and effective in the EXPrESSIVE trials, will expand the number of prevention options and open the door to new and innovative delivery models.

AVAC and partners have been engaging with Merck/MSD since the very start of the Alimatravir product development program and helped conceptualize the EXPrESSIVE efficacy trial design. Building on this foundation of community-centricity, advocates can now push for AMI to be rolled out with speed, scale and equity. Since 2012, each successive PrEP introduction has gone faster than the previous one, yet the time to market and to public health impact for PrEP remains too slow. Read on for AVAC’s insights on AMI, from accelerated licensing and affordability to community priorities and meaningful engagement.

The Latest on AMI

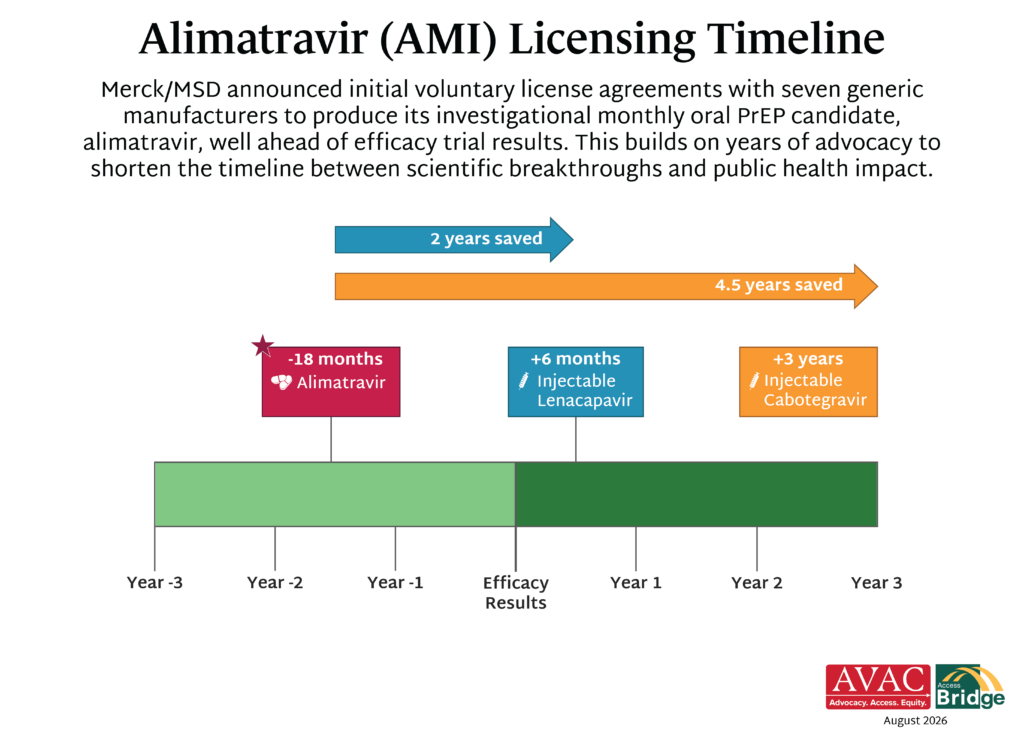
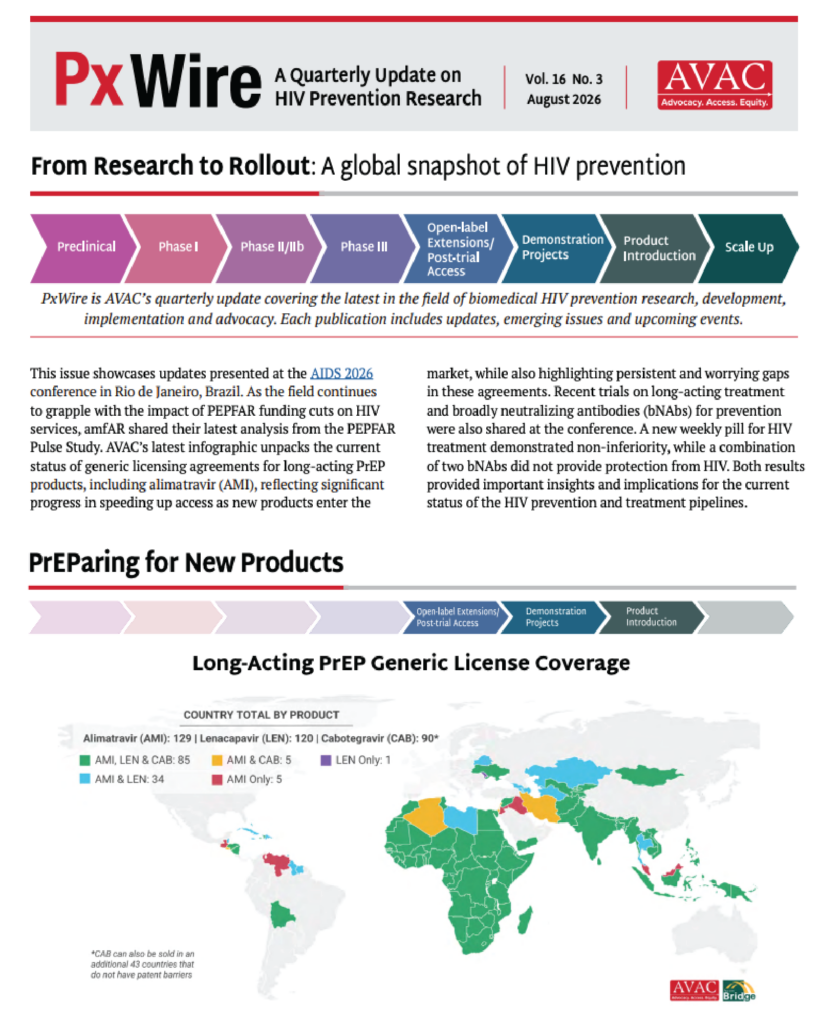
Just before the AIDS 2026 conference in July, AMI developer Merck/MSD granted seven direct licenses to generic manufacturers to produce and market the drug in 129 low- and middle-income countries, including all of Africa and much of Asia, while the trials are still enrolling. These agreements are in place 18 months before a possible efficacy result, and substantially earlier than for lenacapavir or cabotegravir. If AMI is found safe and effective, these agreements could greatly accelerate the introduction process. AVAC and Access Bridge welcomed the announcement, highlighting the challenges that remain to ensure future access is equitable and widespread among the populations that need it most.  

While overall good news, several countries that are hosting the EXPrESSIVE 11 trial are left out of the voluntary license territory, reflecting a broader trend of ;excluding Latin American countries and some Asian countries from voluntary licenses. Merck/MSD did subsequently sign a memorandum of understanding with Fiocruz, a Brazilian manufacturer, to supply AMI for Brazil and the region, but the terms, timing and next steps remain unclear. Furthermore, key populations in high-income countries also face access disparities.

Find all the latest updates on AVAC’s alimatravir page.

PxWire Explores AMI Generic Licensing Agreements

AVAC’s latest edition of PxWire features an analysis of generic licensing for AMI and what it means for the field, and an explainer on generic licensing agreements and current coverage across long-acting prevention products. The explainer examines the promise of generics for advancing affordable, equitable access and raises questions about the persistent and worrying gaps in these agreements. 

Read the latest edition of PxWire.

AMI Could Be the Cheapest HIV Prevention Option Yet, But Does Affordable Mean Accessible? 

Photo credit: aidsmap

A new academic analysis presented at AIDS 2026 suggests that AMI could be manufactured at large scale by generic companies and sold for as low as $3 per person per year, and a separate New York Times report highlighted estimates that generic AMI could be sold to national health systems for as little as $5 per person per year. But an affordable product is only impactful if people can access it. As the Gates Foundation’s Max Lataillade said in an AVAC satellite session at AIDS 2026, “Innovation without global access or implementation does not create the impact that we want. Science creates the possibility, collaboration creates the impact, but communities create the future.”

Read AVAC’s coverage of the AMI modeling data presented at AIDS2026.

From Research to Access: Community Statement from the Global Community Advisory Group (GCAG) on the Future of Alimatravir for HIV Prevention 

Following Merck/MSD’s generic licensing announcement for AMI, the EXPrESSIVE-10 Global Community Advisory Group (GCAG) released a statement on community perspectives and priorities around prevention choice, meaningful community engagement, equitable access and ensuring that communities have a voice as research progresses toward potential introduction. As the GCAG writes, “The test is now whether early planning can translate into faster, more equitable action. An access plan is valuable not because it is announced, but because it creates a pathway that can be tracked, challenged, and delivered.” 

Read the EXPrESSIVE-10 GCAG statement.

Putting Communities at the Center of EXPrESSIVE 

The EXPrESSIVE program includes two phase 3 efficacy trials studying AMI for HIV prevention—EXPrESSIVE-10 among cisgender women and EXPrESSIVE-11 among cisgender men who have sex with men, transgender men, transgender women and gender non-binary individuals. The trials are anticipated to have results in the latter half of 2027. With support from the Gates Foundation, AVAC is supporting strong, consistent community engagement across the program. As a part of this work, AVAC partnered with community-based organizations in Argentina, Brazil, Kenya, Peru, the Philippines, South Africa, Thailand and Vietnam to develop educational materials for EXPrESSIVE-11 through a participatory human-centered design (HCD) process. Luciana Kamel, the Community Education Team Lead for HIV studies at Fiocruz, AVAC’s partner in Brazil for this work, described how this approach changed what was possible: “The trust, openness and respect for our work with the community made it possible to move beyond simply producing recruitment materials and instead build something that reflected the people and contexts the study was intended to engage.”  

Learn more about community-led design in EXPrESSIVE-11.

Check out all the communications materials here.

Additional AMI Resources

Global Health Watch: NIH-DoD Deal & NIAID Restructuring, Ebola Vaccine Progress, Gavi Funding Resumes, New US Foreign Aid Leadership

Issue 85

The US National Institutes of Health (NIH) signs a 10-year agreement that could move significant NIAID research funding to the Department of Defense, as NIAID separately proposes a major restructuring of its clinical research infrastructure. CEPI advances efforts toward a Bundibugyo Ebola vaccine amid funding gaps, while US funding for Gavi resumes and medical groups step in on vaccine guidance. And new leadership at the Department of State brings further change to the US foreign assistance system.

NIAID Funding and Research Infrastructure Uncertain

The US National Institutes of Health (NIH) signed a 10-year agreement with the US Department of Defense (DoD) to allow the transfer of NIH funds to DoD for projects that would “support the advanced development of medical countermeasures against pandemic influenza, chemical, biological, radiological, and nuclear (CBRN) threats, and emerging infectious diseases.” Funding will come out of the NIH’s National Institute of Allergy and Infectious Diseases (NIAID) budget and has the potential to shift hundreds of millions of NIAID-funded research into the military biodefense program. According to an NIH spokesperson interviewed by Nature, “This partnership will only take place on a project-by-project basis, and all research will be within the scope of NIH’s mission. There is no blanket transfer of funds.” Nature reports that NIAID is identifying projects that could move under the arrangement, while congressional Democrats have raised concerns that the agreement could give DoD access to money Congress appropriated for biomedical research at NIH. The agreement was signed last month but went largely under the radar until this week, when Representative Rosa DeLauro (D-CT) – ranking chair of House Appropriations – raised the issue during a hearing.

The agreement comes as NIAID is also proposing a significant restructuring of its clinical research infrastructure. Under a reorganization announced in late August, NIAID would do away with its Division of Clinical Research (DCR), which helps facilitate and coordinate NIAID research programs in the US and internationally, and redistribute clinical operations and oversight across other parts of the Institute. The proposal follows months of delays in renewal notices for NIAID’s HIV clinical trial networks and Centers for AIDS Research (CFARs), raising concerns about the future of the research networks and infrastructure that has supported major advances in HIV, TB and other infectious diseases.

IMPLICATIONS: While the NIH-DoD agreement is supposedly designed to support biomedical countermeasure research, there is substantial discretion over which projects move and how the money is ultimately used. If this agreement shifts infectious-disease research away from NIAID, it risks fragmenting an infrastructure built around peer review, scientific expertise, clinical research networks and long-term public-health priorities. The fact that this agreement was unilaterally executed by the Administration a month ago, without public knowledge or Congressional notification, points to a strong need for policymaker oversight of this process to ensure that Congressionally-appropriated biomedical research funding for NIAID is used for its intended scientific purposes and that changes to the Institute do not undermine or diminish the research capacity and leadership that was built over decades through bipartisan support.

These concerns extend beyond individual grants and institutions. A March Health Affairs analysis highlights how decades of US investment in international HIV research have generated scientific advances and research capacity that also benefit Americans—underscoring that global HIV research infrastructure is not separate from US health and scientific leadership. And a recent Think Global Health analysis of the Administration’s proposed budget cuts at NIH highlights the threaten to essential HIV research.

IDSA and HIVMA have separately warned that NIAID’s research infrastructure is already being destabilized by delayed renewals and a proposed restructuring of its clinical research program. Beyond an initial chart posted to the NIAID’s website, very little detail has been shared on the proposed reorganization, as advocates are monitoring for additional insight to be revealed on the restructuring in an uncharacteristically short deadline for public comment from September 9-18.

READ:

Vaccines Depend on More than Science

Nearly 100 days into the Bundibugyo Ebola response, there is still no approved vaccine, and the Coalition for Epidemic Preparedness Innovations (CEPI) says another $128 million is needed to prevent delays in later-stage trials of vaccine candidates. But CEPI also points to the response as evidence of how investments made before an outbreak can accelerate vaccine development: six pre-positioned research and response networks were activated within three days; three vaccine developers received funding within two weeks; and two experimental vaccines entered Phase 1 trials within 11 weeks. (There are now at least five vaccine candidates in clinical trials.) The experience underscores that rapid vaccine development depends on scientific breakthroughs and on sustained investment in the research networks, financing, partnerships and infrastructure needed to move quickly when a crisis emerges. Meanwhile, the US Administration announced it will release $600 million in Congressionally-appropriated funding for Gavi after more than a year of uncertainty, saying Gavi had committed to transitioning away from vaccines containing the preservative thimerosal—even though Gavi was already moving toward newer vaccines for broader public health benefits.

And in the US, leading medical organizations issued their own recommendations for COVID-19, flu and RSV vaccines as litigation over federal vaccine policy has disrupted the usual Centers for Disease Control and Prevention (CDC) recommendation process.

IMPLICATIONS: The speed of the Bundibugyo response was possible because research networks, manufacturing partnerships, regulatory preparation and vaccine platforms were established before the outbreak, but financing gaps could still slow the next stage. At the same time, the Gavi funding dispute and US medical societies stepping in to provide independent vaccine guidance demonstrate how political interference and instability in public health institutions can affect financing, recommendations, trust and ultimately access. Rapid scientific progress requires sustained investment in the institutions, expertise, partnerships and infrastructure that make it possible long before a crisis begins.

READ:

New Leadership for US Foreign Assistance

This week, Dr. Becky Bunnell, Principal Deputy Assistant Secretary of State for PEPFAR – and a distinguished HIV research and program leader for decades – announced her intention to step down from PEPFAR leadership. No one individual – or organization or policy maker or politician – is responsible for PEPFAR’s tremendous success. But Becky epitomizes all that has made PEPFAR great and impactful – commitment to evidence, data and, most importantly, the individual staff, partners, participants and clients that matter. Her retirement leaves a huge void.

At the same time, Andrew Veprek is the new political appointee leading the US Department of State’s foreign assistance, humanitarian affairs and religious freedom bureau. He replaces Jeremy Lewin, who moved to lead the Department’s policy planning office. Veprek previously led the Bureau of Population, Refugees, and Migration working to align humanitarian programs with the Administration’s immigration priorities. He has criticized “forever aid” and argued that foreign assistance should have a “clear and direct connection” to US foreign policy goals.

IMPLICATIONS: These leadership changes are another important development in the ongoing restructuring of US foreign assistance, as the State Department assumes greater control over programs previously managed through USAID and global health remains one of its three principal foreign-assistance pillars. Veprek has advocated for limiting open-ended assistance, increasing contributions from other countries and more closely aligning funding with Administration priorities. For global health programs, including PEPFAR, this new leadership raises new questions about how much Congressionally-appropriated funding is ultimately released, where it flows and what conditions may be attached.

READ:

The Impact Report: Two Decades of Good Participatory Practice in HIV Research

AVAC’s new Impact Report illustrates how meaningful participation – driven by Good Participatory Practices (GPP) – strengthens both the research process and the global impact of HIV prevention innovations.

Read the Report

What We’re Reading

The Impact Report: Two Decades of Good Participatory Practice in HIV Research 

Volume 1, Issue 3

Scientific breakthroughs in HIV prevention depend on community engagement that drives successful research, development, acceptance and uptake of new products. In 2007, emerging from controversies that halted the first ever PrEP efficacy trials, AVAC and UNAIDS led a global partnership to develop the Good Participatory Practice (GPP) Guidelines, offering systematic guidance on how to engage stakeholders throughout HIV prevention trials. Almost twenty years later, GPP is the gold standard for engagement in HIV prevention research and beyond. This edition of the Impact Report celebrates two decades of GPP, and shares how AVAC and our research and civil society partners have effectively integrated GPP into HIV prevention research by:

These stories illustrate how meaningful engagement – driven by good participatory practices – strengthens both the research process and the global impact of HIV prevention innovations. 

Clinical Trial Design Academy: Equipping Advocates to Shape HIV Prevention Research Decisions and Move the Research Agenda Forward

As clinical trial research becomes increasingly complex, and as innovative HIV prevention products advance through the pipeline, advocates with dual skillsets – deep contextual knowledge of their community’s needs and scientific and technical knowledge – are increasingly sought after to provide critical community input in research that aligns with GPP and holds researchers accountable.

AVAC’s Clinical Trial Design Academy (CTDA), established in 2019, equips advocates with the scientific knowledge and skillset to influence research – from priority setting to trial design and conduct, to results dissemination. Today, the Academy’s 27 members are highly sought after experts who are directly influencing HIV prevention research.

Using a Transformative Human-Centered Design Approach to Co-Create Communication Materials for the Alimatravir Efficacy Trial, EXPrESSIVE-11

Merck’s EXPrESSIVE program is investigating the efficacy of alimatravir (AMI) for monthly oral PrEP. With support from the Gates Foundation, AVAC works to ensure there is strong, consistent engagement with community representatives to influence the design and implementation of the trials, with an eye toward future rollout and access planning for AMI.  

Leveraging expertise in community engagement and human-centered design (HCD), AVAC worked in partnership with community-based organizations on three continents to co-create communications materials for the EXPrESSIVE-11 trial – conducted among men who have sex with men (MSM), transgender, and non-binary people – that are driven by community perspectives and lived realities. The result is a series of tailored, localized materials designed to foster community interest, awareness, and engagement in the trials and in the novel concept of a monthly oral formulation. This work represents a transformative approach to community engagement in materials development for clinical trials. 

Embedding Good Participatory Practice in PURPOSE 1

AVAC collaborates with partners around the world to embed GPP principles in advocacy strategies and partnerships and cultivates a diverse network of advocates, civil society organizations, journalists, researchers, and implementers who champion GPP and are equipped to engage with and influence HIV clinical trial research.

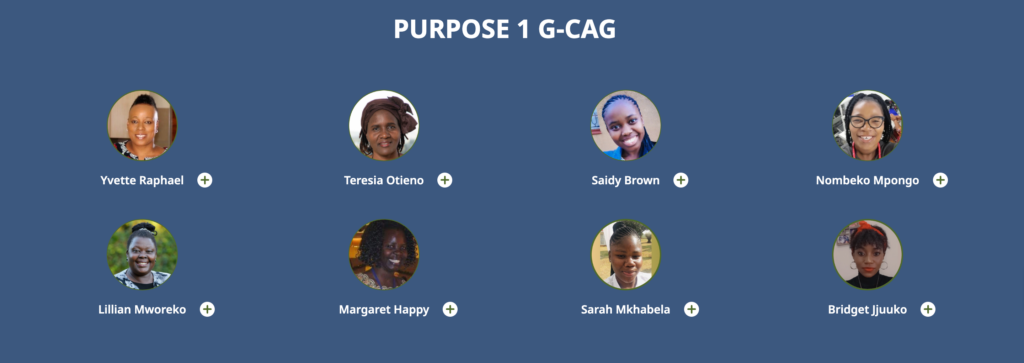
Gilead’s PURPOSE program investigates the efficacy of long-acting injectable lenacapavir (LEN) for PrEP among diverse populations. For PURPOSE 1 and PURPOSE 2, embedding GPP principles promoted accountability, transparency, and meaningful community engagement throughout trial design and conduct. AVAC staff and network of experienced advocacy partners participated as members of the Global Community Accountability Group (GCAG) helping to shape trial design and implementation, participant recruitment and retention, and discussions about product access.

Using a Transformative Human-Centered Design Approach to Co-Create Communication Materials for the Alimatravir Efficacy Trial, EXPrESSIVE-11

Merck’s EXPrESSIVE program is investigating the efficacy of alimatravir (AMI) for monthly oral PrEP. With support from the Gates Foundation, AVAC works to ensure there is strong, consistent engagement with community representatives to influence the design and implementation of the trials, with an eye toward future rollout and access planning for AMI.

Leveraging expertise in community engagement and human-centered design (HCD), AVAC worked in partnership with community-based organizations on three continents to co-create communications materials for the EXPrESSIVE-11 trial – conducted among men who have sex with men (MSM), transgender, and non-binary people – that are driven by community perspectives and lived realities. The result is a series of tailored, localized materials designed to foster community interest, awareness, and engagement in the trials and in the novel concept of a monthly oral formulation. This work represents a transformative approach to community engagement in materials development for clinical trials.

Starting with communities

HCD is a participatory, iterative process that centers communities in the development of research, materials, processes, or services to understand and incorporate their perspectives, preferences, and lived experiences into the final product. HCD uses creative participation techniques to fully explore and understand community perspectives, rather than traditional survey methods. The co-creation process to develop the EXPrESSIVE-11 communication materials started before the trial began.

“What was different about this process was the timing”, says AVAC’s Senior Program Manager Kate Segal, who led this work. “We were really thinking about community engagement and awareness raising early on. Normally it happens when the product starts to go to market, but we had community realities shape the materials from before the trial began. Because the insights centered on their holistic lives and lived experiences, they can be a starting point to think about future demand generation much sooner instead of waiting for product rollout.”

The project focused on eight trial countries in three regions: Argentina, Brazil, and Peru in Latin America; Kenya and South Africa in Africa; and the Philippines, Thailand, and Vietnam in Asia. In each region, AVAC partnered with local organizations – Fundación Huésped and Fiocruz in Latin America, Matchboxology and NENDO in Africa, and APCOM in Asia – to engage local facilitators directly from the community who were trained on the methodology and recruited fellow community members for the HCD sessions. This approach ensured that the right participants were reached, fostered trust among participants, and generated more candid and honest insights.

“We partnered with local community organizations so that this work was really rooted in the community in terms of who was facilitating these workshops and how participants were recruited,” says Segal. “Organizations were already working with the focus populations, so they were able to recruit from communities where they already had relationships and trust. Community was front and center throughout the process.”

Partnering with communities, and allowing them to define the process, concept, and design ensured that materials directly reflected the people the study intended to engage. Looking back on the partnership with AVAC, Luciana Kamel, who leads the Community Education Team for HIV studies at Fiocruz in Brazil, said:

“What stood out most to me was the trust in our work and the respect for the process we have developed with the community. That trust gave us the space to build the materials in a way that was grounded in local realities and in the perspectives of the people we were working with.”

Focus group discussion held with community members for co-creation of EXPrESSIVE-11 communication materials

Turning community perspectives into recruitment materials

The process began with small group HCD immersions, or in-depth focus group discussions. These discussions created space for participants to explore how HIV prevention fits within their lives across four domains – Home, Heart, Health, and Hustle – what might make a monthly prevention option relevant to them, and how they wanted their communities to be represented in engagement materials.

“One thing that stayed with me,” recalls Fundación Huésped’s Gastón Devisich, “was how consistently participants pushed us away from images that felt too aspirational, overly symbolic, or disconnected from their everyday lives. They wanted to see themselves — not an idealized version of the community. That meant thinking about much more than gender or sexuality. It was also about body diversity, age, ethnicity, socioeconomic background, and the places and situations in which people actually live, socialize, connect, and make decisions about their health. In Argentina and Peru, this led us to deliberately recreate everyday moments of intimacy and social connection rather than relying on conventional representations of HIV prevention or sexuality.”

Insights from the local immersions informed two global campaign concepts which were then shared with community participants for feedback. After synthesizing feedback from each country and multiple rounds of review, a single global campaign with unified messaging and imagery that resonated with a broad audience was finalized. Then, the global materials were adapted to fit the local contexts of each region and ensure cultural relevance. The adaptations included language translations, visual adaptations, refined messaging, and other design elements that reflected local communities. Given the diversity of the communities represented among the potential EXPrESSIVE-11 trial participants, this was a critical step in the process to ensure local resonance.

Numan Afifi, Senior Policy and Research Officer at APCOM in Thailand, reflected on the value of locally adapting the materials and what it looked like in practice:

“For me, that was the strongest part of the process. The materials felt more relevant because they were shaped by local communities, languages, cultures and experiences. We were able to talk about how people in our own contexts understand HIV risk, stigma, privacy, and what might make a monthly pill feel realistic and useful in their lives.”

The final materials were shared first with EXPrESSIVE-11 trial sites, some of which sought local IRB approval to use as trial recruitment materials, and at the International AIDS Conference in July 2026. With the trial almost fully enrolled, the materials will be used for continued engagement around the trial.

Representation in the final product

This process showcases a practical application of Good Participatory Practice – meaningfully engaging communities in clinical trial design and conduct from the start. Throughout this process meaningful community engagement meant establishing trust and ensuring local ownership of the process.

Kamel shared: “The biggest lesson from this experience was the possibility of developing materials based on our own realities and cultures, without a predefined vision imposed by the funder… Above all, I think the partnership that was established between us and AVAC was fundamental. The trust, openness, and respect for our work with the community made it possible to move beyond simply producing recruitment materials and instead build something that reflected the people and contexts the study was intended to engage.”

In an unexpected outcome, some participants chose to become the faces of the campaign themselves, embodying their call for images to truly look like them and their communities.

Community members who participated in the development of communication materials also posed as models.

As Segal reflected, “A lot of participants opted to be the models in these materials. We didn’t plan it that way, but we really heard that feedback, and they were really excited to participate in that way.”

For Kamel, what made that representation meaningful was when those same participants saw the printed posters at the Global Village during the AIDS 2026 conference: “They were very happy and excited to see themselves represented. For me, that was also an important part of the process: the people represented in the materials could recognize themselves in them and feel that they were part of something they had helped shape.”

The final EXPrESSIVE-11 communications materials

Inclusivity not just in trials, but for product access too

The insights surfaced through the process can serve as a starting point for understanding how communities perceive a once-monthly oral PrEP pill beyond the trial, and what messaging is most likely to support demand generation if AMI is found safe and effective.

At the same time, this experience highlights that meaningful engagement cannot end once community input has been gathered or when the trial is complete. Merck/MSD’s recent voluntary licensing announcement, made while the trials are ongoing, represents a terrific opportunity in preparing for accelerated access to generics, although it also excludes most Latin American and some Asian countries from the voluntary license, reflecting recent roadblocks to accessing other PrEP products.

“I think it is important to be honest about both sides of this experience – how meaningful and powerful the co-creation process was, and also the uncertainty and concern about whether the people and countries who helped build this work will actually have equitable access to what emerges from it,” said Kamel.

Numan adds: “This is why I think community engagement needs to continue beyond the development of the materials. People should not only help shape how a product is introduced; their experiences and demands should also influence decisions around price, access, eligibility, and implementation.”

Kamel and Numan’s concerns highlight what needs to happen next. Creating materials that reflect people’s lives and priorities is valuable, but real-life impact is only achieved if the prevention products actually reach the communities they are meant to serve. Continuing the practice of GPP, intentional access planning well in advance of efficacy results by product developers, funders, advocates, communities, and other stakeholders will be critical to ensuring that meaningful community engagement translates into tangible access and impact.

I think there is an important lesson in the timing of the process. This was the first time I have been involved in a process where communities were brought in this early to think about communications and demand generation for a product still in development, and that was a significant step forward. … So, while this represents progress compared with the usual timing of community engagement, it also shows how much earlier these processes need to begin if we genuinely want community input to shape implementation rather than simply prepare materials alongside an already-moving trial.” 

Gastón Devisich
Fundación Huésped, Argentina

Developing these materials was an incredible experience, particularly because we were able to build something that reflected the real face and experiences of the community. As we have discussed in presentations, stigma and where people can actually access prevention are central issues.

Luciana Kamel
Fiocruz, Brazil

Overall, I found the process valuable because it built both useful materials and stronger relationships between AVAC and us. It showed what is possible when there is trust, openness, and genuine respect for community knowledge. I hope we can carry that approach into future work… and continue pushing to ensure that the communities involved can actually benefit from the products they helped shape. 

Numan Afifi
APCOM, Thailand

⮐ Return to the the Impact Report

The Clinical Trial Design Academy: Equipping Advocates to Shape HIV Prevention Research Decisions and Move the Research Agenda Forward

HIV prevention research must be conducted in collaboration with the communities it intends to serve; decisions about study design, participant populations and locations, conduct, and future access need to reflect community input. This engagement creates transparency in the process, builds trust, and facilitates future acceptance of trial results. The AVAC and UNAIDS Good Participatory Practice (GPP) Guidelines are a proven framework for early and sustained partnership between advocates and researchers throughout the research process. As clinical trial research becomes increasingly complex, and as innovative HIV prevention products advance through the pipeline, advocates with dual skillsets – deep contextual knowledge of their community’s needs and scientific and technical knowledge – are increasingly sought after to provide critical community input in research that aligns with GPP and holds researchers accountable.

Building a Skilled Network of Advocates to Influence HIV Research

AVAC’s Clinical Trial Design Academy (CTDA), established in 2019, equips advocates with the scientific knowledge and skillset to influence research – from priority setting to trial design and conduct, to results dissemination. Today, the Academy’s 27 members are highly sought after experts who are directly influencing HIV prevention research. Through immersive learning, ongoing skills strengthening, and direct engagement with research teams, product developers and funders, the CTDA has nurtured this growing pool of technically prepared advocates and community representatives who critically review and inform complex trial designs, ask critical questions, and ensure community priorities are reflected in research decisions and protocols.

For Academy members, this continuing education has changed how they engage with both researchers and the communities they represent. Rather than choosing between scientific expertise and community knowledge, they bring the two together; translating complex science for communities while bringing community priorities into spaces where research decisions are made. As one member reflected:

“Personally, CTDA has helped me put my community first because, with every interaction I have with clinical trials and scientists, every question I ask and every contribution I make is based on community perspectives. I am now able to translate community needs into scientific priorities, ensuring that the voices of the communities we represent are reflected in research and product development.”

— Idah Mulala, Ascend Futures Foundation, Zambia

Academy members’ growing influence and technical knowledge is further reinforced through the strength of the CTDA network. The Academy connects advocates with each other as well as directly to the clinical trial researchers, product developers, regulators, and other experts who shape HIV prevention research. As a network of diverse stakeholders with varied experiences, CTDA members can come together to confront technical challenges, share lessons learned, and work together to advance community needs.

“Beyond the technical skills, the biggest impact has been the network we’ve built, a community that continues to learn from one another and ensure research remains responsive to community realities.”

— Simon Ondiek, Kenya

Translating Community Priorities into Research Decisions

CTDA members are using their technical knowledge, community expertise, and collective advocacy to not only engage on individual trials, but to define and advance community-centered research priorities for the field. Recently, CTDA members helped shape the development of the People’s Research Agenda (PRA), a community-led accountability framework that assesses the state of HIV prevention research across the pipeline and identifies community-driven priority actions for HIV prevention and vaccine research. CTDA members – and advocates in general – use the PRA to advocate for concrete recommendations, including the inclusion of transgender and non-binary people, people who inject drugs, and pregnant and lactating people; examining interactions with gender-affirming treatment and other medicines; improving adherence support; and building post-trial access, pricing and scale-up planning into research from the outset.

Together, the CTDA and PRA create an upstream engagement mechanism through which community priorities can influence research questions and agendas long before individual trials are designed and implemented. Those community priorities are then carried from the broader research agenda into the design and conduct of individual trials. Building on work pioneered during the PURPOSE trials of injectable lenacapavir, the CTDA participated in the very first consultation of any kind for what became Merck’s EXPrESSIVE program assessing the efficacy of a new monthly oral PrEP pill. Seven CTDA members then participated in follow-up protocol consultations. Because of this early engagement, community recommendations informed protocol development and major trial decisions. Merck has publicly recognized the role of community input, including the selection of daily oral TDF/FTC as the comparator in the EXPrESSIVE program. Their involvement is part of a broader approach to community engagement across the EXPrESSIVE program that has placed advocates at the center of trial planning, and six CTDA members serve on the trial’s Global Community Advisory Board, providing sustained community input as the trial moves forward.

The design and conduct of the EXPrESSIVE trials demonstrate what is possible when technically informed and empowered advocates are engaged early and consistently to inform decision-making. Academy members are also applying their knowledge to other research accountability structures, ensuring community engagement in defining upstream research priorities, informing trial designs, and sustained partnerships throughout trial implementation and product rollout planning. Currently, CTDA members are also represented in the Zambia Community Advisory Platform, the AIDS Clinical Trials Group Community Advisory Board (CAB), the Baylor College of Medicine CAB, FASTER Pediatric and Adolescent CAB, amongst others.

Preparing Advocates for What’s Ahead

Approaches like AVAC’s CTDA matters more than ever today: new and emerging HIV prevention technologies require increasingly complex trial designs, and communities are being asked to weigh in on scientific, ethical, and implementation questions, especially when there are no clear-cut answers. Without the CTDA and broader community engagement mechanisms, HIV prevention research risks becoming less connected to the people it is intended to serve. The field needs trusted mechanisms like the CTDA that prepare advocates to interrogate complex trial designs, identify ethical and implementation risks early, and ensure that scientific efficiency does not come at the expense of relevance, equity, acceptability, or future access. That preparation is ongoing with regular CTDA convenings where members are continuously supported to deepen their technical knowledge and engage with new developments in the field; the next CTDA convening will take place in October 2026. As resources shrink and trial designs become more complex, this combination of technical literacy, community accountability and sustained researcher–advocate partnership is more essential than ever.

⮐ Return to the the Impact Report

Embedding Good Participatory Practice in PURPOSE 1

Ethical conduct of HIV clinical trial research improves as product developers, researchers, and other stakeholders become increasingly intentional about community partnership and engagement. When AVAC and UNAIDS developed the Good Participatory Practice (GPP) guidelines, the goal was to create a framework for trial funders, sponsors and implementers to engage communities across the HIV prevention research continuum. From trial design and implementation to results dissemination and access planning, GPP provides a guide for ensuring prevention products are responsive to community priorities and accessible to the people they aim to serve. For almost 20 years of GPP implementation, AVAC has collaborated with partners around the world to embed the principles within advocacy strategies and partnerships and cultivating a diverse network of advocates, civil society organizations, journalists, researchers, and implementers who champion GPP and are equipped to engage with, question, and influence HIV clinical trial research.

The Good Participatory Practice Guidelines, developed by AVAC and UNAIDS

Promoting Transparency and Accountability in Gilead’s PURPOSE Program

Gilead’s PURPOSE program is comprised of six clinical trials investigating long-acting injectable lenacapavir (LEN) for PrEP among diverse populations. PURPOSE 1, one of the two efficacy trials in the program, was conducted among cisgender women in South Africa and Uganda, while PURPOSE 2 expanded the reach to include men who have sex with men (MSM), transgender men and women, and gender non-binary people. Both trials found LEN highly safe and effective among participants. Beyond the clinical findings, the trials also demonstrated that embedding GPP principles promotes accountability, transparency, and meaningful community engagement throughout trial design and conduct.

A case study of GPP implementation in PURPOSE 1 highlights how GPP strengthens ethical conduct and inclusion. AVAC staff and partners participated as members of the Global Community Accountability Group (GCAG), a formal mechanism for providing community perspectives on the trial. GCAG members provided community recommendations on trial design, including protocol considerations, participant recruitment and retention, and trial implementation to Gilead and researchers. Advocacy by the GCAG contributed to expansion of the inclusion criteria to enroll adolescents and to allow pregnant and breastfeeding people to remain in PURPOSE 1 after re-consent, reinforcing the principle that communities should help shape research that directly affects them and allowing the study to gather critical data on the safety and efficacy of LEN in populations often excluded from research.

Nombeko Mpongo of the Desmond Tutu Health Foundation and a member of the African Women’s Prevention Community Accountability Board served on the GCAG for PURPOSE 1 and describes how early involvement translated into influence and accountability:

“What was important was that communities were involved from the beginning. We received the protocol early, before the study began, and had the opportunity to scrutinize it and identify what we thought needed to change. One of the issues we raised was ensuring that women who became pregnant during the study would not automatically be excluded, so we could better understand prevention during pregnancy. We were not there as tokens—we took ownership of our role in the GCAG. We made sure Gilead was accountable to us, and we were also accountable to our communities. It was a flow of accountability in both directions.”

Through this structured forum and sustained engagement, community concerns were heard, researchers and the developer remained responsive, and the priorities of women and young girls remained central to decision making.

Members of the PURPOSE-1 GCAG

Championing Good Participatory Practice

Impactful community engagement in clinical trials requires sustained investment in community leadership, scientific literacy, and trusted partnerships. Years before PURPOSE 1, AVAC and partners established the Coalition to Accelerate and Support Prevention Research (CASPR), an Africa-led advocacy coalition of civil society organizations working to advance biomedical HIV prevention research and equitable access to proven HIV prevention products. CASPR supported a network of advocates with the knowledge and relationships to engage with emerging HIV prevention research. Many of these advocates went on to serve on the PURPOSE 1 GCAG while remaining connected to the broader communities and networks they worked with through CASPR. This helped extend engagement and understanding of the trial beyond the GCAG, and strengthened the pathway from engaging in research to product introduction and access planning.

As Navita Jain, Senior Program Manager and Team Lead for AVAC’s Partnership Network Team explains, “CASPR provided the connective tissue that made meaningful engagement possible. Advocates weren’t starting from scratch when they joined the GCAG—they were already informed, connected and prepared to engage, and could bring that knowledge back to their communities well before conversations about rollout began.”

Because AVAC, CASPR partners, AWPCAB and the broader network of informed advocates were already equipped with the expertise, partnerships, and communities’ trust, they helped bridge the transition from research implementation to disseminating trial results and planning for access. This continued engagement with Gilead, funders and decision makers supported community confidence in the results and accelerated momentum toward equitable LEN rollout in comparison to the delivery of previous PrEP products. This contribution was recognized when Yvette Raphael, Executive Director of APHA, accepted the American Association for the Advancement of Science’s (AAAS) Mani L. Bhaumik Breakthrough of the Year Award on behalf of CASPR, AWPCAB, and the GCAG, affirming the critical role of community advocacy in LEN’s development.

Yvette Raphael, the Executive Director of APHA and a PURPOSE-1 GCAG member accepted the AAAS Breakthrough of the Year Award.

From Research to Rollout

GPP guided community engagement in PURPOSE 1, creating meaningful opportunities for advocates to influence the trial. However, the GPP guidelines recommend continued engagement to shape access and rollout once a product has been proven safe and effective, achieves regulatory approval, and becomes available. After the PURPOSE 1 results were announced, Gilead discontinued the GCAG, even though many of the decisions that would determine equitable access, including licensing, pricing, manufacturing, and product introduction, were still ahead. For HIV activist Saidy Brown, a member of CASPR’s Young Women’s HIV Prevention Council (YWHPC) and GCAG member, continuing the GCAG through product introduction would have been a natural extension of the partnership that began during research:

“We were there from the beginning, supporting the research, and it would have made sense for that partnership to continue through rollout. As much as communities supported the trial, there was also an opportunity to bring that support back to communities as LEN became available. Keeping GCAG members engaged through introduction would have helped create that continuity from research to rollout.”

While the GCAG was discontinued, the networks and relationships built through CASPR have provided a platform for advocates to continue pushing for equitable access, with demands including: a role in access planning, speed and equity in rollout, price transparency, and accelerated access to generics. As a result, donors and ministries of health are engaging with and investing in civil society partners to secure community buy-in, inform rollout planning and generate demand. While LEN rollout across early adopter countries reflects this community leadership, advocates remain vigilant in identifying and addressing challenges around equitable access.

Even so, global access has been far from perfect. Advocates’ demand that all PURPOSE efficacy trial countries be included in voluntary licensing agreements has not been met, reflecting that strong incorporation of GPP during a trial does not automatically translate into access once the trial is over; the work of and commitment to engagement must carry through. Nevertheless, the positive lessons from PURPOSE 1 are informing AVAC’s recent work in Merck’s EXPrESSIVE program assessing the efficacy of a new monthly oral PrEP pill. As new HIV prevention products advance through the research pipeline, AVAC and partners will continue to call for developers, donors and other stakeholders to apply the lessons and practice of GPP – strengthening community engagement throughout research & development, policy, and product introduction so that scientific innovation translates into equitable access and real-world impact.

⮐ Return to the the Impact Report

Global Health Watch: Steinem’s Legacy, US Global Health Aid Cuts; OMB Grant Rule Delayed; Future of Global Health Reform

Issue 84

We’ve lost another champion for global health and reproductive rights this week: Gloria Steinem, the pioneering feminist and activist who spent decades fighting for gender equality, reproductive choice and the power of people to shape the decisions that affect their lives. This is a reminder to continue questioning who has a voice, who gets to decide, and why bodily autonomy is a fundamental right.

This week’s issue addresses those questions: a new analysis finds US bilateral health agreements could dramatically reduce global health funding by more than half; Congress has temporarily blocked the White House OMB’s effort to expand political control over federal grants; and, as global health architecture reform moves forward, civil society is demanding a role in shaping what comes next.

Bilateral Health Deals Could Cut US Health Aid by 59%

A new analysis from Public Citizen and Partners In Health finds that the US Administration’s bilateral (government-to-government) health agreements would drastically reduce US global health funding and foreign assistance to 18 recipient countries by 59 percent ($2 billion) by 2030 compared to pre-2025 funding. This is despite the US Congress maintaining relatively stable global health appropriations. The organizations analyzed 18 available memoranda of understanding (MoU) noting that the Administration “has kept the public in the dark about the full details of its plans for the future of US support for global health…” and “the MOUs warn of a disturbing potential underspend of congressionally appropriated global health dollars.” The agreements require countries to increase domestic health spending as US support declines. However, in 11 of the 18 countries, those domestic resource mobilization commitments would not fully replace the planned reductions in US funding.

IMPLICATIONS: The analysis raises significant questions about whether the Administration’s “America First” global health strategy toward “country ownership” and “self-reliance” is actually achievable. Instead, the analysis posits that the accelerated transition to sustainable domestic financing actually constitutes a rapid withdrawal of critical US support that these countries may not have the fiscal capacity to replace. The analysis further conveys that many of these deals contain worrisome conditionalities and performance metrics tied to funding, which may not be attainable as bilateral funding to support in-country programs are greatly diminished to begin with. The authors also exposed a disconnect between the global health funding Congress has appropriated and the substantially lower spending envisioned by the Administration under the bilateral agreements, with potential consequences for HIV, TB, malaria, Ebola and other health programs. The Department of State said it intends to spend all congressionally-appropriated global health funds, but where and how funding not included in the bilateral agreements will be spent is the outstanding question.

READ:

US Congress Votes to Delay White House Rule Politicizing Federal Grants

Members of the US House of Representatives on both sides of the political aisle voted to pass a continuing resolution (CR) for fiscal year 2027 (FY 27) appropriations. This CR was previously approved by the Senate in early August, which authorizes government spending until December 11, delays a government shutdown on September 30 (the end of the US fiscal year), and, at least for now, delays implementation of the White House Office of Management and Budget’s (OMB) controversial proposal to give political appointees greater authority over federal grantmaking. Last month, in a stopgap spending bill released by Senate appropriators, Democrats and Republicans joined in adding a provision that would prevent the OMB rule from taking effect until at least December 11, while Congress negotiates broader government funding measures. The proposal was originally slated to go into effect on October 1, but opposition from both Democratic and Republican appropriators slowed the path forward.

IMPLICATIONS: This temporary delay is important, allowing more time for advocacy and for potential litigation to formulate. However, if implemented in December (or any time), the rule would fundamentally reshape the US research enterprise by injecting political considerations into grantmaking, weakening peer review and undermining the international collaborations that drive progress against HIV, TB, emerging infectious diseases and other global health challenges. The Senate’s actions last month and the bipartisan agreement on the CR suggest that the months of public opposition and advocacy from the advocacy and scientific community may be beginning to influence policymakers. The Senate’s intervention is one of the first signs that resistance to the OMB proposal extends beyond the scientific community and into both parties in Congress. 

Evidence-based decision-making – not politics

The risk of having public health research and recommendations guided by politics as proposed by OMB is real, as evidenced by the ongoing politicization of US vaccine research and policies. To ensure Americans get credible, evidence-based recommendations that previously came from the CDC, the American Medical Association (AMA) and the Vaccine Integrity Project, which is based at the University of Minnesota’s Center for Infectious Disease Research and Policy (CIDRAP), initiated a collaborative effort to conduct a comprehensive review of evidence for vaccines of the 2026-2027 respiratory virus season. They published their findings this week in the Journal of the AMA (JAMA).

Read the Article

Future of Global Health Architecture 

As the WHO-hosted Joint Task Force on Global Health Architecture Reform meets in person for the first time this week, the Health Architecture Reimagined (HEAR) CSO Steering Committee issued a letter urging the Task Force to put equity and meaningful community and civil society leadership at the center of reform, while also strengthening regional platforms and protecting access as financing shifts. Meanwhile, a new Council on Foreign Relations analysis of 67 health architecture reform proposals finds consensus around shifting decision-making to countries and regions, aligning donor funding with country priorities, strengthening national health systems, expanding regional roles and diversifying financing.

IMPLICATIONS: While the analysis and civil society advocacy show agreement on the direction of global health architecture reform, the outstanding question of how to get there remains. The CFR analysis highlights the key challenges around who pays versus who decides, what is gained or lost by moving from disease-specific programs to integrated health systems, and which functions belong at global versus regional levels. As these decisions are made, HEAR CSO argues that reform must be judged not only by efficiency, but by whether it advances equity, protects access and gives affected communities meaningful power. Moreover, these processes are all unfolding in the midst of leadership transitions at WHO, the Global Fund, Unitaid and the Medicines Patent Pool, amongst others.

READ

What We’re Reading

Global Health Watch: Legacies of Parton & Goosby, expiring global health funds, Jeremy Lewin’s move, Ebola funding & vaccine R&D

Issue 83

This week, the global health community lost a powerful, if unlikely, champion in Dolly Parton. She used her singing celebrity to support science and public health, including a $1 million investment that supported early research connected to Moderna’s COVID-19 vaccine. She was a supporter of literacy, marginalized communities and HIV awareness and care. Her legacy is a reminder of what it looks like to use influence to build trust in science, which couldn’t be more important today as vaccines, public health and LGBTQI+ communities are continually undermined and politicized.

Speaking of leadership, longtime leader Eric Goosby officially retired this week. Eric served as the US Global AIDS Coordinator and led the President’s Emergency Plan for AIDS Relief (PEPFAR) from 2009 to 2013 under President Barack Obama. But before he led PEPFAR and since he returned to UCSF, Eric has been a compassionate doctor, a passionate advocate, and a tireless defender of science and human rights. His colleague and mentee, mike Reid, posted this video from Eric’s retirement celebration.

Also this week, members of the US Congress demanded that the Administration release billions in congressionally-appropriated global health funding before it expires; another leadership change is underway at the Department of State, which oversees the transformation of US foreign assistance; and in the DRC, the Ebola response is making progress even as inadequate funding threatens efforts.

Congress Raises Alarm Over Expiring Global Health Funds and PEPFAR Restructuring 

Democratic members of the US Congress are pressing Secretary of State Marco Rubio and OMB Director Russell Vought to release billions in congressionally-approved foreign assistance before it expires on September 30. In a new letter, they note that $7.5 billion remains unobligated, including more than $3 billion for Global Health Programs. They object to OMB’s reported decision to reserve approximately $1.35 billion in FY2025 global health funding for the closeout costs of USAID rather than health programs Congress funded. They also question plans for PEPFAR, citing the two-million decline in people reported as receiving PEPFAR-supported HIV treatment in 2025 and asking the Administration to explain how proposed reductions in CDC’s implementing role will affect treatment continuity, HIV prevention, surveillance, technical expertise and community-based programs. They are seeking answers by September 9.

IMPLICATIONS: If billions in congressionally-appropriated global health funding are allowed to expire, or used to dismantle USAID rather than support programs, the effects could exacerbate the disruptions already being documented across PEPFAR and other health programs. Additionally, reducing the CDC’s role would shift how PEPFAR is implemented, and also erode surveillance, laboratory, technical and data systems that help countries maintain HIV services and detect wider health threats.

READ:

Jeremy Lewin Leaves Foreign Assistance Role

Jeremy Lewin officially stepped down as head of the US Department of State’s foreign assistance bureau and is now serving as the Department’s Director of Policy Planning. He will advise Secretary of State Marco Rubio on key foreign policy matters. An original DOGE agent at the beginning of this Administration, Lewin was one of the architects of the Administration’s overhaul of US foreign assistance following the dismantling of USAID, including the shift toward bilateral government-to-government agreements and the development of the America First Global Health Strategy. Lewin will now oversee the Bureau of Economic, Energy and Business Affairs and continue representing the US in G7 and G20 development discussions. 

IMPLICATIONS: Lewin’s departure is yet another leadership transition for US foreign assistance. This happens as the State Department works to implement a redesigned aid and global health system, while being unable to obligate billions in congressionally- appropriated funding. The big question for global health now is who will lead implementation of the new foreign assistance architecture that Lewin helped design, including the bilateral agreements intended to reshape PEPFAR and other US global health programs. 

READ:

DRC Ebola Response Gains Ground as Funding Gaps Threaten Progress 

The Ebola Bundibugyo outbreak in the Democratic Republic of the Congo (DRC) continues to expand, with more than 560 new cases in the last week. WHO reports improvements in contact tracing and testing and issued interim guidance on prevention and control to help countries safely continue routine immunization activities during an outbreak. However, transmission remains high and funding gaps threaten the immediate response and the development of preventive vaccines. CEPI, which supports several potential Bundibugyo vaccine candidates, says it faces a shortfall of hundreds of millions of dollars for vaccine R&D, even as it launched trials this week of its fifth Bundibugyo-specific virus vaccine candidate in response to the escalating epidemic. In Uganda, the WHO officially declared its related outbreak over.  

IMPLICATIONS: Resources are needed now to prevent new infections, just as sustained investment in vaccine R&D is needed to ensure future outbreaks can be minimized. As we highlighted last week, cuts to foreign assistance and weakened surveillance and response infrastructure have compounded insecurity and other challenges confronting the DRC response. And while vaccines could help prevent Bundibugyo if proven safe and effective, they cannot replace surveillance, health workers, laboratories, community engagement and health systems needed to prepare and respond.  

READ:

New Issue of PxWire

AVAC’s latest issue covers PEPFAR funding cuts; generic licensing of alimatravir; and the latest developments for long-acting treatment and bNAbs for prevention.

Read Now

What We’re Reading

Webinar

Evolving Oral PrEP Guidance for Cis Women: What do we know, and what will it take?

Join The Choice Agenda for a conversation with Heather-Marie Anne Schmidt of UNAIDS, Simon Collins of HIV i-Base, Jenell Stewart of the University of Minnesota and Raphael Landovitz of UCLA on evolving PrEP science, discordant guidelines and what it will take to advance PrEP equity for cis women, trans and non-binary people.

Register

Global Health Watch: NIH reopens South Africa Research Funding; DRC Ebola Strains Outbreak Response; WHO + FDA Leadership Shifts

Issue 82

The US National Institutes of Health (NIH) lifted research funding restrictions on South Africa; the DRC’s Ebola outbreak grows, exposing the consequences of weakened outbreak-response systems; and leadership changes at the World Health Organization (WHO) and the US Food and Drug Administration (FDA) raise questions about the future of global health decision-making.

NIH Reopens Research Funding to South Africa

The US National Institutes of Health (NIH) lifted its ban on funding research in South Africa. This comes after 18 months of “holding all research awards” for NIH research partnerships with South African institutions as the country was designated a “country of concern” alongside China. As Science reports, an internal memo notes that the “[NIH] decided it was exempt from a February 2025 executive order…that halted ‘foreign aid or assistance’ to South Africa” because “the Foreign Assistance Act of 1961 does not govern NIH funding.” The lift of this order reopens the door to new grants. However, the NIH also announced that South African scientists will no longer be eligible to receive training grants from its Fogarty International Center, because the country is upper middle-income and part of the G20. This follows last month’s announcement from the Department of State that it will phase out PEPFAR support to South Africa.

IMPLICATIONS: South Africa is one of the world’s most important HIV, TB and infectious disease research centers – built through decades of diplomacy and partnership with the NIH and US State Department, with numerous South African scientific leaders of today partnering with the Fogarty International Center. This is part of a wider unraveling of this decades-long scientific partnership spanning HIV research, treatment and prevention, emanating from false accusations made by the White House against the South African government for “not doing enough” to address unfounded claims of discrimination purportedly against the country’s white Afrikaner community. While this week’s reversal of the ban restores an important piece of that scientific collaboration, the larger relationship remains strained, including the planned PEPFAR phase out. US investments in PEPFAR and NIH partnerships in South Africa have resulted in significant contributions and innovations in the treatment and prevention of HIV, TB and other infectious diseases for people around the world, including in the US. For the HIV field especially, this reversal shows the interconnectedness of the research partnerships and bilateral programs and why both research and programmatic funding matter. The simple restoration of scientific collaboration, while continuing to withdraw and erode programmatic infrastructure will stifle scientific progress when it relies on strong public health infrastructure and partnerships made possible through PEPFAR.

READ:

DRC Ebola Outbreak Illustrates Impact of Foreign Aid Restrictions 

The ongoing Ebola Bundibugyo outbreak in the Democratic Republic of the Congo (DRC) is now the country’s deadliest Ebola epidemic and the second deadliest ever recorded. At an emergency WHO meeting, Director-General Tedros Adhanom Ghebreyesus said, “We must be frank: The epidemic is far from being under control… It had a big head start, and we are still playing catch-up.” WHO says it could still be brought under control within approximately three months, but only if resources and response capacity are rapidly scaled up. WHO figures report that only 60 percent of the $115 million needed to finance the response has been raised. Currently, there is no licensed vaccine or treatment for the Bundibugyo strain. Many new cases are appearing outside known transmission chains, which indicate infections are continuing to spread undetected. 

READ:

Leadership Shifts at WHO and US Food and Drug Administration

The WHO and US Food and Drug Administration (FDA) are undergoing leadership changes. WHO’s chief scientist and Assistant Director-General for health promotion and disease prevention and control Jeremy Farrar will leave at the end of September. This latest departure comes amid WHO’s challenge to continue charting its future in the face of reduced donor funding, a smaller senior leadership structure, and the end of Director-General Dr. Tedros Ghebreyesus tenure later this year. Meanwhile, in the US, White House adviser on the Domestic Policy Council, Dr. Heidi Overton was nominated to lead the FDA as commissioner. She helped shape several of the Administration’s health initiatives, including its recent overhaul of childhood vaccine recommendations and is a proponent of the government’s anti-abortion policies. Her nomination comes after months of turmoil and a leadership vacuum at the FDA, which saw Marty Markary depart from the role in May after a short tenure of 13 months. Some Senators who are now debating her nomination are questioning her role in the recent vaccine order as they prepare for confirmation hearings.

IMPLICATIONS: As WHO is being forced to redefine its role and priorities amid shrinking resources, the US FDA is facing significant scrutiny and political pressure over vaccines and scientific decision-making. For global health and HIV, leadership stability and scientific independence at both agencies matter beyond the internal structure as WHO normative guidance and FDA regulatory decisions will determine which products move forward, how quickly they reach countries and communities who need them. Many national regulatory authorities around the world rely heavily on FDA’s rigorous regulatory review and approval processes to inform their decision-making in local approval, procurement, and implementation of new and emerging biomedical innovations. Similarly, countries without the capacity or expertise to independently develop treatment and prevention guidelines rely heavily on WHO’s normative guidance to ensure health policies are grounded in the latest evidence. The looming question at the FDA is whether its leadership and decisions will continue to be guided by evidence, as political pressure increasingly shapes the ideologues may potentially helm the world’s premier regulatory agency. as political pressure increasingly shapes the agency’s leadership and priorities.

READ:

What We’re Reading