Global Health Watch: Vaccine Science Blocked; Hantavirus Highlights System Strain; Zambia Rejects “Trade for Aid”

Issue 67

The US administration again blocks key vaccine safety and effectiveness data; a hantavirus incident underscores growing strain and fragmentation in the global health system; and Zambia rejects a “trade for aid” deal tying health assistance to geopolitical and economic interests—with implications for HIV programs and global health cooperation.

Continued Suppression of Vaccine Science

The US Administration continues to block publication of key vaccine safety and effectiveness data. This week, officials at the US Food and Drug Administration (FDA) stopped publication of studies on COVID-19 and shingles vaccines including the analyses of millions of US patient records that found no new major safety concerns associated with COVID-19 vaccines and confirmed the established safety profile of the shingles vaccine. Despite already being accepted by peer-reviewed journals and/or undergoing the standard scientific review, FDA officials reportedly ordered some studies withdrawn and refused to approve conference abstracts for others.

This follows last week’s decision by US Centers for Disease Control and Prevention (CDC) leadership to block publication of a Morbidity and Mortality Weekly Report (MMWR) showing that COVID-19 vaccines reduced hospitalizations and emergency visits by roughly 50% among healthy adults. Despite passing rigorous internal scientific reviews, the report was withheld over “methodological concerns”.

IMPLICATIONS: At a time of reduced vaccine confidence, suppressing findings on safety and effectiveness risks continues to fuel rising vaccine misinformation and hesitancy. And the continued politicization of vaccine science that prevents publication of validated research undermines trust and limits access to evidence that should be used to support vaccination strategies and policy. Taken together, communities that stand to benefit the most from vaccines may delay or forgo receiving vaccinations for themselves and/or their families.

READ:

Hantavirus Amid a Fragmenting Global Health System

News of hantavirus infections aboard a cruise ship this week comes amid broader concerns about weakening global health security. Reporting on the incident underscores how even localized health threats are unfolding in a fragmented coordination environment, while analysis in The Lancet warns that the role of key institutions like the World Health Organization (WHO) are increasingly contested, citing concerns about transparency, financing, and “institutional drift”. At the same time, broader global health commentary highlights fragmentation, declining funding, and shifting geopolitical priorities as pressures threatening multilateral cooperation. Together, these dynamics are raising urgent questions ahead of the World Health Assembly later this month about whether governments will pursue meaningful reform or continue operating within a system that is increasingly complex, underfunded and politically fragmented.

IMPLICATIONS: Pandemic preparedness and outbreak response require strong surveillance, transparent data sharing, and international coordination, which are core functions of multilateral institutions like the WHO. As confidence in and support for these institutions dissipates and as financing recedes and becomes more conditional, the ability to detect and respond to emerging health risks is limited. Without reforms to strengthen WHO’s core scientific and coordinating role, clarify mandates across institutions and secure more stable and independent financing, the global health system risks becoming less and less effective, leaving countries more vulnerable with more frequent disease outbreaks.

READ:

Trade for Aid: Zambia Rejects Deal with US

Zambian government officials rejected a proposed bilateral Memorandum of Understanding (MoU) with the US offering up to $2 billion over the next five years under certain terms, including access to sensitive health data and to the country’s critical minerals. The deal was rejected due to the “incorporation of terms that the Zambian government considers unacceptable.” Ghana and Zimbabwe are also reported to have rejected bilateral MoUs.

These decisions come alongside the broader shift in US global health policy, with new Global Health Security and Diplomacy (GHSD) implementation guidance outlining an “America First” transactional approach that prioritizes bilateral agreements, co-financing, and alignment with US strategic interests. Scripps News reports on this “trade for aid” theme, raising concerns that access to HIV treatment and prevention could hinge on geopolitical and/or commercial interests.

IMPLICATIONS: The Zambian bilateral MoU experience illustrates the dangers of the country-by-country, transactional model for global health and foreign assistance, which effectively will make it harder to see and measure the true scale of the HIV epidemic in the wake of funding cuts and politicization of health. Referring to the recent PEPFAR data that was released last month, AVAC’s Mitchell Warren notes that “we’re [already] seeing a decrease in people accessing prevention services, and we’re seeing a decrease in those accessing the community-based programs that were really critical because those programs have been taken offline.” This “thinning at the margins” described in HIV programs signals a deeper risk: even as treatment numbers hold, the erosion of prevention and community services could lead to increased infections over time and destabilize the effectiveness of the global HIV response.

READ:

What We’re Reading

Join AVAC and partners for the launch of STI Advocacy Hubs and the introduction of new country-led advocacy agendas from Kenya, South Africa, and Zimbabwe. This webinar will highlight the key challenges shaping STI prevention, diagnostics, and care in each country, and outline priority actions to strengthen national responses. 

Resources

Inside the Decisions that Changed Global Health

An AVAC Conversation with Nicholas Enrich

Join us Wednesday, May 20 at 10am ET for a conversation with Nicholas Enrich, author of Into the Wood Chipper and former global health lead at the US Agency for International Development (USAID). Inside the Decisions that Changed Global Health will provide Enrich’s inside perspective on the decisions that led to the dismantling of USAID and the foreign aid freeze and what they mean for global health today.

This important conversation comes 16 months after the US Presidential Administration issued a deeply cruel executive order freezing nearly all foreign assistance, halting billions of dollars in already-approved funding under the bad-faith claim of a “90-day review”. What followed – including AVAC’s lawsuit against the US Department of State challenging the legality of the aid freeze – has been a drawn-out, chaotic disruption that stopped life-saving work across the globe, shutting down USAID and other valuable organizations, and harming lives, health, and livelihoods.

Please join us for this important conversation.

Global Health Watch: PEPFAR Data, Latest in Health Deals, Lawmakers Oppose Redirected Global Health Funding, Pushback on Expanded Gag Rule

Issue 66

On the heels of the recent PEPFAR data release, a New York Times article by Stephanie Nolen, AIDS Creeps Back in Parts of Zambia, a Year After US Cuts to HIV Assistance, this week serves as an illustration of the consequences of the US policy decisions on lives. It shows what the policy shifts, funding disruptions, and data gaps covered in this issue, look like in Zambia: strained clinics, interrupted HIV services, and uncertainty for patients and providers relying on PEPFAR.

Recent PEPFAR Data Masks Deeper Disruptions

Continued analysis of PEPFAR data released by the US Department of State last week points to a much more nuanced and complicated narrative about the state of the HIV response. A Vox Future Perfect piece dissects the latest figures, covering July–September 2025, which the administration presents as a picture of continuity and efficiency: treatment numbers appear stable, and prevention among pregnant and breastfeeding women appear to make a targeted gain. But the article, alongside independent analyses by KFF, amfAR’s Brian Honerman and co-authors, Jirair Ratevosian, and AVAC, makes clear that this snapshot obscures deeper disruptions. Critical gaps in testing, prevention and workforce capacity are minimized, or left out entirely, to create a distorted picture of a resilient program.

The Vox analysis also calls out the absence of a full year of data. While the Department of State cited reporting and implementation challenges, previous datasets that were posted then subsequently removed in January 2026, tell a different story. Analyses by amfAR and the International AIDS Society of those unreleased figures reveal far sharper disruptions across testing, prevention and service delivery, particularly in the wake of the January 2025 foreign aid freeze. Taken together, the evidence suggests that the final quarter may represent the most stable period of an otherwise deeply destabilizing year—masking the scale and severity of the broader setbacks that may inevitably emerge farther down the road.

IMPLICATIONS: Incomplete or selectively framed data can shape policymaker perceptions, donor decisions and country-level planning, which could potentially justify further cuts or an urgent need to surge resources to counteract devastating actions stemming from the foreign aid freeze and stop work orders. And as Vox reports, “For years, one of PEPFAR’s strengths was its system that generated unusually granular public data about where the program was functioning well and where it wasn’t. That made it possible to spot problems and course-correct, part of what made PEPFAR so successful and helped save more than 25 million lives. Now that picture is much thinner… And it is unclear whether this kind of detailed HIV-specific reporting will continue at all under the terms of its America First Global Health Strategy.”

US Lawmakers Challenge President’s Plan to Redirect Global Health Funds to Cover Costs of Dismantling USAID

A group of 17 US senators issued a letter demanding that the US Presidential administration reverse its plan to withhold $19 billion in congressionally-appropriated foreign assistance and spend down the funding as Congress directed. Led by Sen. Brian Schatz, Democrat of Hawaii, Ranking Member of the Senate Appropriations Subcommittee on State and Foreign Operations, the group highlights the administration’s plan to redirect $3.2 billion of the $19 billion away from lifesaving programs, including programs to combat HIV/AIDS ($330 million), malaria ($250 million), maternal and child health ($320 million) and global health security ($650 million) to instead cover the costs associated with abruptly terminating USAID and foreign assistance awards.

IMPLICATIONS: The dispute signals a deepening constitutional and policy clash over Congress’s power of the purse and the future of US global health leadership. If Congressionally-appropriated funds continue to be withheld or redirected by the administration, critical programs face continued disruption. This undermines years of investment and erodes trust with country partners and implementing organizations. Beyond the human impact, this move risks normalizing the diversion of Congressionally-appropriated funds for purposes unauthorized by Congress and sets a precedent that could destabilize future domestic and global health funding. These questionable budgetary maneuvers being tested in the global space, could also justify being used to scale back funding on domestic issues, including HIV.

Countries Push Back on America First Health Agreements

Ghana has become the latest country to reject its bilateral memorandum of understanding (MoU) with the US as part of the America First Global Health Strategy. The West African nation, joins Zimbabwe which rejected its terms with the US, while Zambia continues to face pressure to open its mineral sector in exchange for foreign assistance. A new analysis in Think Global Health tracks the rollout of the MoUs, which transitions US support from traditional aid to cofinanced partnerships requiring greater domestic spending by national governments. The analysis finds wide variation in expectations and raises concerns about whether countries can meet these commitments or sustain essential health programs. The tracker also highlights limited transparency and uncertainty about the long-term impact on health outcomes.

IMPLICATIONS: The structure of the bilateral MOUs signals a fundamental reorientation of US global health engagement—from partnership-based public health investment to strengthen mutual global health security cooperation, to a paradigm of conditional, transactional, interest-driven agreements. Tying health assistance to resource extraction, data access or political alignment risks undermining trust built with impacted communities, weakening multilateral cooperation on global health and fragmenting long-standing health systems. Early consequences are already visible.

Lawmakers Push Back on Expanded Global Gag Rule

A group of Congresspeople in the US House of Representatives introduced the Protecting Human Rights and Public Health in Foreign Assistance Act, a bill designed to block the US administration’s expanded Global Gag Rule (formally known as the “Protecting Human Flourishing in Foreign Assistance Policy”). Historically, the Global Gag Rule prohibited foreign nongovernmental organizations which receive US family planning funds from providing, referring, counseling or advocating for abortion, even with their own non-US resources. In January 2026, the administration expanded the policy to cover additional funding streams, institutions and issue areas, extending beyond family planning to include gender-affirming care and Diversity, Equity, Inclusion (DEI) initiatives. More than 80 organizations have endorsed the legislation to block the expanded Global Gag Rule describing it as an unprecedented effort to impose ideologically-driven restrictions across global health and development partnerships.

IMPLICATIONS: Evidence from past iterations of the Global Gag Rule shows detrimental impact across health systems—reducing access to contraception, increasing unintended pregnancies and abortion rates, and weakening integrated services, including HIV prevention, maternal health and care for LGBTQI+ communities. Advocates note that this latest expansion risks amplifying those harms by restricting how countries and organizations use their own funds and fragmenting partnerships that underpin effective service delivery. These restrictions may in turn drive key populations further underground and fracture service delivery.

PrEP4All Sues for Release of Undisclosed Agreement

PrEP4All filed a federal lawsuit against the US Department of Health and Human Services (HHS), Department of Justice (DOJ), Centers for Disease Control and Prevention (CDC), and National Institutes of Health (NIH), seeking the release of a previously undisclosed agreement tied to HIV prevention research and policy.

Read More

What We’re Reading

Attending INTEREST 2026? Resources to Support Your Participation

The International Conference on HIV Treatment, Pathogenesis, and Prevention Research (INTEREST), will take place 12-15 May in Dar es Salaam, Tanzania, covering new advances in HIV prevention, treatment, cure, and vaccine research and development (R&D); implementation science; and how science is being translated into impact through an African-led HIV agenda.

AVAC has compiled resources and highlights to support participation and engagement.

AVAC Infographics

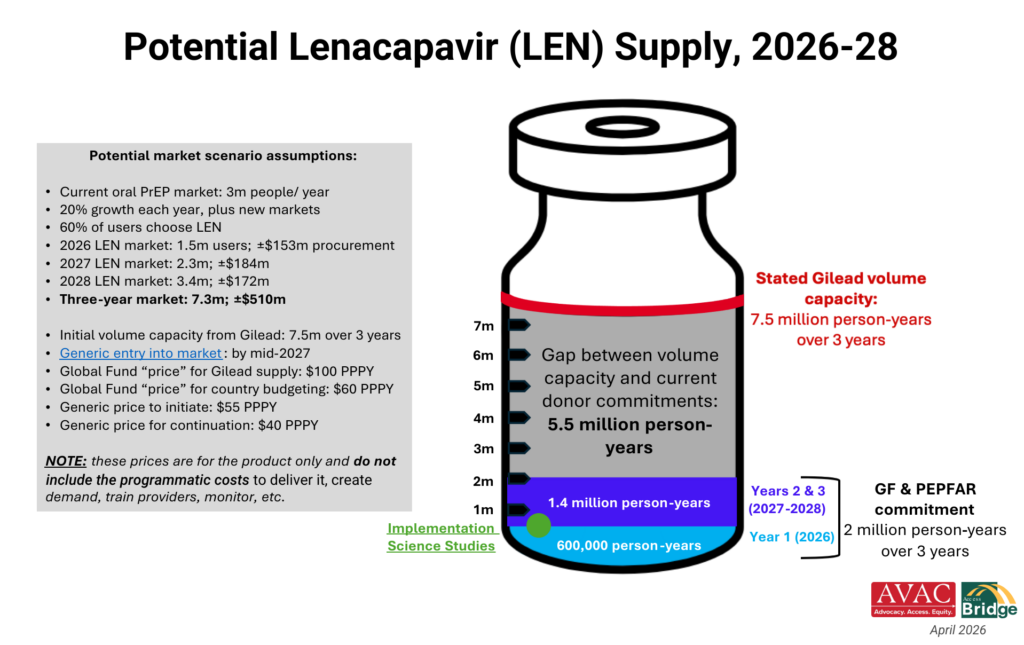
For those presenting at INTEREST (as well as anyone interested in tracking the field), AVAC’s latest infographics on the HIV R&D and delivery pipelines are available in an easy-to-use slide format – including lenacapavir for HIV PrEP (LEN) volume commitments, the current landscape of prevention options in development, and the impact of US funding cuts with new data from PEPFAR. We hope these are useful for presentations and discussions at the conference and beyond.

Join AVAC, Access Bridge and Partners at These Sessions of Interest

If you are in Dar es Salaam, be sure to join sessions in which AVAC, Access Bridge, and our partners are involved.

Posters (Wednesday, 13 May and Thursday, 14 May)

  • HIV Prevention Research and Development at a Tipping Point: Insights from the 2025 People’s Research Agenda Update by AVAC’s Grace Kumwenda

    Identifying key priorities for the HIV prevention research agenda moving forward and informing global advocacy and engagement in R&D in response to the evolving HIV prevention landscape, including recent scientific advances and growing threats posed by funding and political disruptions.
  • Community Led Research on HIV Treatment, Pathogenesis and Prevention among People who use Drugs in Tanzania by Kwame Juma of Tanzania Network of People Who Use Drugs (TaNPUD) and COMPASS

    Description forthcoming!

Mini-Oral Abstract (Friday, 15 May)

  • Global Forecast of Long-Acting PrEP Need for Key Populations (2025-2030), by Catherine Verde Hashim presented Wawira Nyagah; 12:00-12:24

    Understand the need for long-acting PrEP amongst key populations globally and explore which countries have the highest need.

What We’re Watching

The INTEREST 2026 program includes a full list of sessions, including the following, which AVAC is tracking closely (note: all times are local Tanzanian time):

Tuesday, 12 May

Wednesday, 13 May

If you are attending INTEREST 2026 and would like to connect, reach out to the AVAC and Access Bridge teams at [email protected] and [email protected]. And stay up to date on the latest news from AVAC via our newsletters or on LinkedIn.

What the Latest PEPFAR Data Reveal and Why It Matters


Newly released data from the President’s Emergency Plan for AIDS Relief (PEPFAR) were meant to reassure, but a deeper look tells a more concerning story. AVAC’s latest blog post and graphics provide a more nuanced analysis: “Reduced prevention today means higher HIV incidence in the future. That effect is not yet visible in the current data, but it is a well-understood dynamic in public health.”

Independent reviews and analyses of the data show consistent declines across testing, diagnoses and prevention, including steep drops in PrEP, the DREAMS program for adolescent girls and young women and key population programs. Notably, KFF’s analysis provides comparisons across five years of data, providing critical context on PEPFAR performance over time.

See the AVAC resources below that put this all into context.

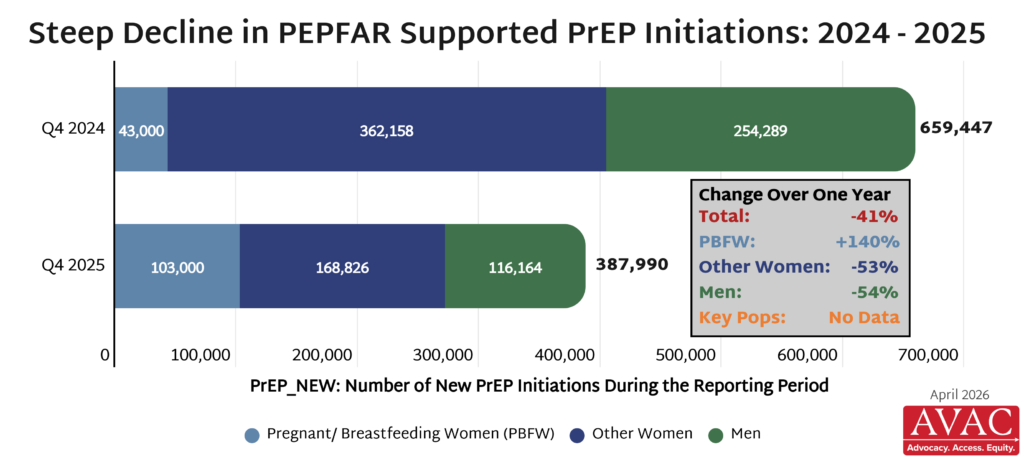
Steep Decline in PEPFAR PrEP Initiations

PEPFAR-supported PrEP initiations are down by 41% in one year, with men and non-pregnant or breastfeeding women seeing drops exceeding 50% — and key populations absent from the data altogether. These trends reflect broader disruptions across the prevention cascade: fewer people are being tested, diagnosed and connected to prevention.


A Warning, Not Reassurance

AVAC Policy Director Suraj Madoori and Executive Director Mitchell Warren unpack what the new PEPFAR data mean for the future of HIV prevention. “PEPFAR’s success has long depended on a continuous flow: people are tested for HIV, diagnosed and then linked to treatment if they are living with HIV or offered prevention if not,” they write. “When testing declines, as it is under PEPFAR right now, the entire cascade is disrupted.” None of this diminishes PEPFAR’s extraordinary achievements. On the contrary, it underscores what is at stake. The path forward requires a more balanced reading of the evidence.


What this Means for the Rollout of New HIV Prevention Innovations

The data come at an especially heartbreaking moment of scientific promise: highly effective long-acting prevention options like injectable lenacapavir for HIV PrEP (LEN) are finally available and offer the potential to transform how HIV is prevented. But innovations depend on strong delivery systems—robust testing, community engagement, and functioning prevention programs, along with strong data systems, to ensure innovation has impact.

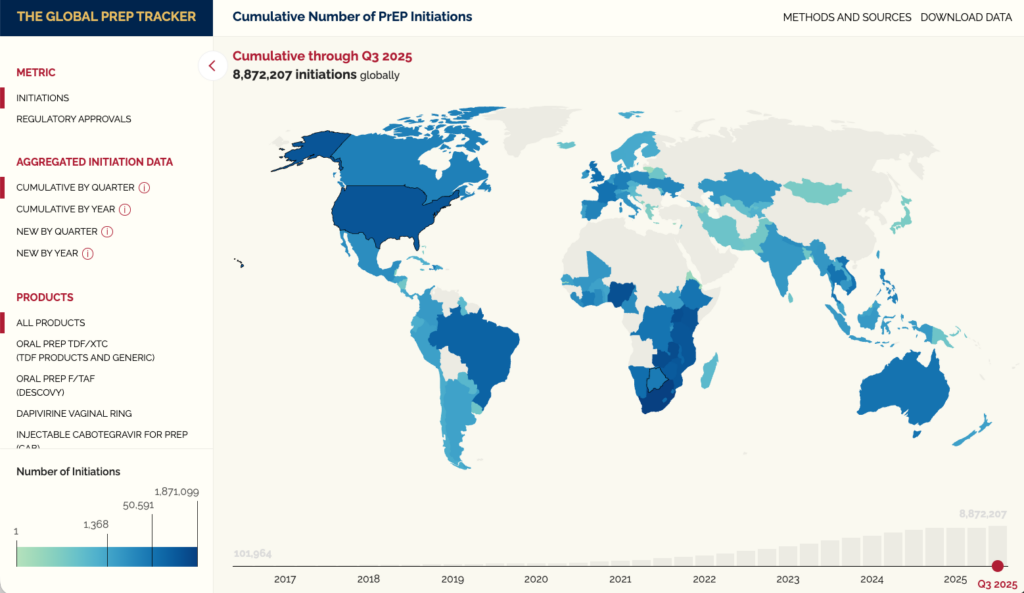
For the latest on PrEP use and initiations, explore AVAC’s PrEPWatch Global PrEP Tracker. And for in-depth look at the situation in South Africa, check out this article from Bhekisisa: Our anti-HIV jab will be rolled out in 6 weeks. But funding cuts hollowed out the system needed to deliver it.


Prevention Disrupted: The Impact of the PEPFAR Stop-Work Orders on PrEP

Since January 2025, AVAC has tracked the severe impact of the PEPFAR stop-work orders on PrEP, with many countries suspending or significantly reducing their ability to provide PrEP services.

View the latest from AVAC’s Impact Tracker, now updated with the recent PEPFAR data release.


These resources point to a clear conclusion: the current moment is not one of stability—it is one of risk. PEPFAR’s extraordinary legacy shows what is possible when prevention, treatment, data, and community leadership work together. But the front end is weakening. Without urgent action to restore prevention, ensure transparency in data, and prioritize key populations, the global HIV response risks backsliding—just as new tools are poised to make progress possible.

Data Don’t Lie, But the Story is Distorted

By Mitchell Warren and Suraj Madoori

For more than two decades, the President’s Emergency Plan for AIDS Relief (PEPFAR) has been widely recognized as one of the most effective global health programs in history—saving lives, strengthening health systems, and building a durable HIV response that, with consistent bipartisan support, has weathered global disruptions and crises from Ebola to COVID-19. Today, PEPFAR’s legacy is facing a different kind of test: not a biological threat, but a political one.

Buried late on a Friday afternoon, the US Administration released PEPFAR data after a long delay, and secured only after sustained pressure from civil society. What should have provided clarity and clear answers about the state of PEPFAR programming has only sparked more concern about the state of the global HIV response.

The administration argued that the data they released show continuity and efficiency: treatment numbers remain steady, and prevention among pregnant and breastfeeding women appeared to make a targeted gain. With those two short-sighted and time-limited data points, they argue that the program continues delivering results with fewer resources.

But a fuller, more detailed analysis suggests a more complicated and concerning picture—and argues that the framing by administration officials misleadingly distorts the picture.

In independent assessments, a broader trend emerges: a pre-print by amfAR’s Brian Honerman and co-authors, an analysis by Jirair Ratevosian, a new review from KFF, and AVAC’s own analysis of the data, all sound the alarm that the front end of the HIV response is weakening.

Across multiple indicators, declines are evident. HIV testing is down. Diagnoses are down. And prevention is under perhaps the greatest threat: the initiation of pre-exposure prophylaxis (PrEP) has dropped sharply overall—by nearly half, including an alarming 40% drop in PrEP initiations among adolescent girls and young women (AGYW) aged 15-24. And key population programming has been gutted and is not even tracked in the data.

These trends matter because ending HIV as a global health threat relies on interconnected systems. PEPFAR’s success has long depended on a continuous flow: people are tested for HIV, diagnosed and then linked to treatment if they are living with HIV or offered prevention if not. When testing declines, as it is under PEPFAR right now, the entire cascade is disrupted. Fewer tests mean fewer diagnoses mean fewer people entering care. Fewer people identified as at-risk means fewer people start PrEP, and fewer future HIV infections are averted.

Community-based programs, especially those reaching key populations and AGYW, have been disproportionately affected by the administration’s funding disruptions and policy shifts to date, and represent an especially crucial link in these systems. Programs reaching those most at risk are often the hardest to sustain, but they are among the most essential.

Both in the data release and as we move forward, there is growing concern about transparency. Some worry that this could be the last PEPFAR data that is released without significant pressure from advocates and Congress. The Administration has signalled a shift away from centralized PEPFAR data reporting and toward country-level systems under bilateral agreements. While country ownership is essential, this raises questions about consistency, comparability, and accountability.

Without standardized, publicly accessible and disaggregated data, it becomes far more difficult for accountability watchers—from civil society to researchers to policymakers—to assess progress, identify gaps, and advocate effectively. Variations in reporting, like the absence of key indicators such as age, sex, or population group—especially the dearth of data on men who have sex with men, transgender people and sex workers—leave critical questions unanswered and key populations increasingly invisible.

These data are a warning, not reassurance as the administration distortedly claims. HIV treatment may look stable but testing and prevention show declines. What began with the foreign aid stop-work orders in January 2025 and has continued through further funding disruptions are cracking the foundation of the HIV response.

These cracks in the foundation are becoming visible at an especially heartbreaking moment of scientific promise: long-acting prevention options like lenacapavir (LEN) are finally available and offer the potential to transform how HIV is prevented. But these innovations depend on strong delivery systems—robust testing, community engagement, and functioning prevention programs, along with strong data systems to monitor the effectiveness of these programs.

PEPFAR-supported PrEP programs should be the solid foundation on which to introduce LEN (a clear Administration priority), but, instead, they are now introducing LEN when almost half the PrEP initiations are gone, and community-based and patient-centred prevention programs are diminished.

The implications are clear. Reduced prevention today means higher HIV incidence in the future. That effect is not yet be visible in current data, but it is a well-understood dynamic in public health.

None of this diminishes PEPFAR’s extraordinary achievements. On the contrary, it underscores what is at stake. The program’s success has always rested on a comprehensive approach that combines treatment, prevention, data, and community leadership. When one part weakens, the entire system is at risk.

The path forward requires a more balanced reading of the evidence.

First, prevention must be restored as a central pillar of the response. Testing, PrEP, and community-based services are not optional—they are essential.

Second, key populations must remain visible and prioritized. Data that fail to capture their experiences cannot guide effective policy.

Third, transparency must be preserved. Reliable, consistent data are the foundation of accountability and trust.

Finally, investment must match ambition. Ending the HIV epidemic will require sustained resources, not less.

For more than two decades, PEPFAR has shown the world what is possible when data drive action. The challenge now is to ensure that the data are shared in full, understood in context, and used to strengthen the global HIV response.

Global Health Watch: PEPFAR Data Reveal Prevention Crisis, Impact of HIV Cuts on South Africa, CDC Blocks COVID-19 Vaccine Report

Issue 65

Newly released PEPFAR data reveals declines in HIV testing and prevention; a new report details the impact of US funding cuts on HIV programs in South Africa; and the US Centers for Disease Control and Prevention (CDC) blocks publication showing the benefits of COVID-19 vaccination adding to further turmoil around US vaccine policy and scientific transparency.

New PEPFAR Data Reveal a Prevention Crisis Beneath the Surface

The US Department of State released long-delayed, partial 2025 data from the President’s Emergency Plan for AIDS Relief (PEPFAR) Friday. The administration is framing these data as proof that the HIV response is “doing very good”, despite multiple analyses indicating otherwise. A narrow reading of the data show stable treatment numbers and selective gains, such as reported increases in PrEP use among pregnant and breastfeeding women. But independent analyses from KFF, amfAR, Emily Bass, Jirair Ratevosian and AVAC show steep declines across the prevention cascade following the foreign aid freeze and stop-work orders in testing, diagnoses and PrEP initiations. Even where gains are highlighted, they are outweighed by overall losses, sharp declines in spending and disproportionate impact on key populations, young women and infants. AVAC’s review of available PEPFAR data show a 41 percent decline in overall PrEP initiations when comparing July-September 2024 to the same period in 2025. Among women who are not pregnant or breastfeeding, 53 percent fewer initiated PrEP in the last year and 54 percent fewer men. And no disaggregated data is publicly available on key populations, groups historically dependent on PEPFAR-supported prevention efforts, and who are essential to reach for epidemic control.

Days prior to the release of these data, Mike Reid, PEPFAR’s Chief Science Officer resigned out of principle.

IMPLICATIONS: These data point to a response that is “thinning at the margins”, Jirair Ratevosian wrote, where testing, prevention and early engagement in care occur. Stable treatment numbers reflect the resilience of existing systems, not the health of the full HIV response, and declines in prevention today are likely to translate into increased infections down the line. This is especially concerning as countries begin rolling out lenacapavir for HIV PrEP (LEN). Last week, US officials described their ability to scale LEN as a result of their “creative destruction” of the past year. PEPFAR, Global Fund and national PrEP programs should be introducing LEN on top of a solid foundation of robust PrEP programs. Instead, LEN is being introduced when almost half the PrEP initiations are gone, and PrEP programs are decimated. Without urgent action to restore testing and prevention programs, ensure transparency and accountability in data and prioritize key populations, the global HIV response risks backsliding at precisely the moment when it should be accelerating.

New Report Reveals Impact of US Funding Cuts on HIV Response in South Africa

Physicians for Human Rights released a new report which shows the severity of the devastation to HIV programs in South Africa as a result of the cuts to US global health programs. The report – developed with longtime AVAC partners in South Africa, APHA and Emthonjeni Counseling & Training – documents widespread interruptions to community outreach, peer education, and clinic-based services, particularly those serving key populations, while also noting that the full scale of the damage is difficult to quantify due to simultaneous cuts to data systems. Reporting from Bhekisisa reinforces these findings, highlighting that South Africa is preparing to introduce a highly effective new HIV prevention option into a system that has been hollowed out, with critical gaps in the programs needed to deliver it effectively.

IMPLICATIONS: LEN has the potential to transform HIV prevention, but without strong, functioning systems that include testing, outreach, community engagement, surveillance and supply chains, it cannot reach those who need it most. The erosion of HIV prevention programs, especially those serving key populations (along with the erasure of data on these populations) risks wasting investments and puts the entire system tasked with delivering new innovations at risk. Overall, the findings underscore how abrupt funding cuts do not simply pause programs; they dismantle the infrastructure that underpins impact, making recovery slower, more costly, and less equitable.

CDC Blocks Publication of COVID-19 Vaccine Report

A planned CDC report showing that COVID-19 vaccines reduced hospitalizations and emergency visits by roughly 50% among healthy adults was blocked from publication. Despite going through an internal scientific review and using traditional and validated scientific methods, CDC leadership refused to publish the issue of the highly regarded Morbidity and Mortality Week Report (MMWR), citing “methodological concerns” and prompting alarm among public health experts. At the same time, the Department of Defense announced it would end the long-standing requirement for annual flu vaccination among US military personnel. This has been a requirement for decades to protect troop readiness and is now being framed around personal choice.

IMPLICATIONS: These actions continue the broader shift away from evidence-based vaccine policy toward politicization of public health decisions. Suppressing or delaying dissemination of scientific findings risks undermining confidence in public health institutions and weakens the data needed to guide policy and practice. Meanwhile, rolling back vaccine mandates for major populations or groups of individuals could increase illness, disrupt operations, and contribute to declining vaccination norms.

What We’re Reading

Resources

Global Health Watch: LEN for PrEP commitments, US budget cuts shift from basic research, “trade over aid” raises global health concerns

Issue 64

This week, a new commitment to expand the reach of lenacapavir for HIV PrEP is a step forward but not enough to deliver impact, detail on the proposed US budget cuts reflects a shift away from basic research, and a broader shift toward “trade over aid” raises new concerns for global health financing and impact.

Lenacapavir for HIV PrEP Target Expands to 3 Million, But Falls Short of Need

The US Department of State, Global Fund and Gilead Sciences announced a new volume commitment for lenacapavir for HIV PrEP (LEN), increasing their three-year target of reaching two million people with LEN to three million people. This builds on prior commitments from the Global Fund, with strong support from the Children’s Investment Fund (CIFF), and PEPFAR, and investments from the Gates Foundation and Unitaid to accelerate development and access to generic LEN at lower prices. However, the global PrEP data that AVAC tracks shows that this is not yet in line with what the market can bear and what is needed for impact. Ultimately, LEN must reach more than five million people per year to have real impact, build a sustainable market, and drive prices down even further,” AVAC’s Mitchell Warren said in a statement. “This week’s announcement is progress, but it does not go far enough or fast enough, and the entire field must act faster and think bigger to achieve meaningful progress.”

According to the Global Fund, early program data suggest strong uptake of LEN among “priority populations”, including adolescent girls and young women and people accessing PrEP for the first time. However, it remains unclear how “priority populations” are being defined and who exactly is included among those accessing PrEP for the first time. Without explicitly naming these groups, there is a significant risk that key populations will be overlooked and effectively erased from early introduction efforts. A GBGMC and AVAC report released in September shows that the annual global need for PrEP among key populations will be 11.5 million by 2030. By the end of next week, eight of the nine countries identified by the Global Fund for early LEN introduction, with the exception of South Africa, will have begun to rollout LEN.

IMPLICATIONS: The announcement highlights the progress and what is possible: rapid early rollout, aligned partnerships, and market-shaping efforts, including generic licensing. But without ambitious targets and bigger volume commitments for at least four million people in the next two years, clear pricing and financing, reliable supply chains, well-supported service delivery, and robust monitoring to ensure equitable access, LEN risks following the same rollout as earlier innovations like oral PrEP, which reached too few, too slowly. As LEN rollout expands, impact will depend on clearly defining and reaching all priority populations, tracking uptake across groups, and avoiding patterns of inequity in access where new prevention tools reach some communities while leaving others behind.

RESOURCES:

Proposed Office of AIDS Research (OAR) Budget Cuts and Shift to Implementation Science

The US President’s Fiscal Year 2027 budget request to Congress proposes a $5–6 billion budget cut for the National Institutes of Health (NIH). This includes a 28% budget cut to the National Institute of Allergy and Infectious Diseases (NIAID) and a nearly $600 million reduction to the Office of AIDS Research (OAR), which coordinates HIV research across the NIH. The accompanying Congressional Budget Justification (CBJ) issued by the NIH reiterates that NIAID is transitioning away from its “historic triad” of HIV, biodefense and pandemic preparedness and other infectious and immunologic disease to two new pillars: infectious disease research and immunological, allergy and autoimmune research. The CBJ also offers no explicit mention of HIV cure or vaccine research, instead placing a strong emphasis on implementation science. As reported in August, this reflects a potential dramatic shift of the NIH’s budget and priorities: away from basic science toward implementation science, with an emphasis on how best to use existing tools (including lenacapavir for PrEP) to end the epidemic in the US.

IMPLICATIONS: The President’s FY27 budget is a proposal that Congress will consider through the annual appropriations process. Lawmakers will recommend funding allocations for Labor, Health, and Human Services programs, including the Department of Health & Human Services (HHS) and the NIH. Historically, NIH funding has enjoyed bipartisan support, with Congress often rejecting proposed cuts or structural changes from Administrations. However, the scale of the proposed reduction in the OAR budget and NIH overall (see last week’s Global Health Watch), and vocal shift toward implementation research, raises serious concerns about the potential ripple effects across the HIV research and development portfolio. LEN for PrEP could have a critical role to play in ending the epidemic in the US and around the world, and implementation science is needed to optimize its potential impact. But LEN is not the only intervention needed, and it will be critically important to embed any implementation science agenda into a comprehensive “R&D and delivery” research agenda that shows the appropriate balance of the overall HIV/AIDS research portfolio.

US Administration Pushes “Trade Over Aid” Agreements

Ahead of an anticipated announcement at the United Nations later this month, the US Secretary of State called on national governments to support a new “trade over aid” initiative that would scale back traditional humanitarian assistance in favor of trade and investment partnerships. The move signals further intention to distance the US from its long-standing role as a leading provider of humanitarian aid and move toward a model grounded in economic exchange.

IMPLICATIONS: This shift raises significant concerns for global health, particularly for HIV and other disease responses that rely on sustained, predictable public financing. While trade and investment can play an important role in long-term development, it is not a substitute for life-saving humanitarian and health programs. Concerns are emerging that a shift towards a trade first model, would favor large private sector companies and risk exploitation of countries that are dependent on critical foreign assistance and aid to support public health systems and infrastructure. The bilateral agreements as part of the America First Global Health Strategy for example, also model this shift with provisions appearing in these agreements on US access to a country’s minerals in exchange for foreign assistance. At a moment when new tools like long-acting PrEP are emerging, the success of the global HIV response will depend not only on innovation, but on maintaining the public funding and partnerships needed to deliver these advances at scale.

What We’re Reading

Three Million is a Step Forward, But Not Enough

AVAC and Access Bridge Call for Accelerated Ambition and Action to Expand Access to Lenacapavir for PrEP

In response to today’s announcement of the increased volume commitments for lenacapavir (LEN) for HIV prevention, AVAC and Access Bridge call for global leaders to do even more to ensure meaningful, expanded access. Unveiled at an event hosted by the Center for Strategic and International Studies, the U.S. Department of State, the Global Fund and Gilead announced a catalytic increase in their commitment to reach people with LEN for PrEP: from 2 million to 3 million people over the next three years, signaling some progress in efforts to scale access to LEN for PrEP.
 
“This is an overdue step forward, but it is just that — a step in the right direction,” said Mitchell Warren, Executive Director of AVAC. “It is good to go from 2 million to 3 million over three years, but this is not yet in line with what the market can bear and what is needed for impact. A meaningful volume commitment of at least four million LEN users in two years is both possible and has the potential to unlock faster access, strengthen market confidence, and accelerate access to prevention for communities that need it most. Volume guarantees must be seen as a floor, not a ceiling. Ultimately, LEN must reach more than five million people per year to have real impact, build a sustainable market, and drive prices down even further. Today’s announcement is progress, but it does not go far enough or fast enough, and the entire field must act faster and think bigger to achieve meaningful progress.”
 
In July 2025, AVAC published a market assessment that the world could go much faster than the original Global Fund/PEPFAR/Gilead partnership announced in December 2024 and reach at least 1.5 million people with LEN in just one year in low- and middle-income countries if resources were made available. Today’s announcement still falls short of that target.
 
LEN has been widely recognized as a transformative HIV prevention option, with the every-six-month injection providing highly effective protection. However, translating the scientific breakthrough of LEN into population-level access and impact requires coordinated action across many sectors, including financing, manufacturing, pricing, regulatory, and delivery.
 
“This could be a pivotal moment, but we cannot bend the epidemic curve with only 3 million doses”, said Wawira Nyagah, Executive Director of Access Bridge. “LEN for PrEP has achieved critical milestones in record time compared to oral PrEP, DVR, and CAB, but speed, scale and equity are still needed to deliver impact. It’s great to see global support lining up behind the science, but much stronger commitments from global actors and national governments are needed. To see LEN truly succeed, we must ensure that programs are designed with communities at the center and that commitments translate into real access for the people who need it. Access Bridge is working across countries in Eastern and Southern Africa to ensure countries are equipped to meet this moment.”
 
AVAC and Access Bridge call on stakeholders to meet the current moment of scientific opportunity and public health need with bolder ambition. The past decade of PrEP programs have highlighted numerous lessons on how to get LEN rollout right as part of comprehensive HIV prevention programs so that today’s announcement translates into real-world impact. Key considerations include:

Today’s announcement builds on prior commitments from the Global Fund and PEPFAR to reach two million people with LEN over three years, as well as investments from the Gates Foundation and Unitaid to accelerate development and access to generic LEN at lower prices. With generic LEN likely entering the market in the first half of 2027, now is the time to strengthen and grow the market with Gilead’s supply: the faster the market grows, the more infections that can be averted at lower cost.
 
“Commitments are important, but orders are essential. In Gilead’s own words, they can produce far more if orders are made,” said Warren. “Especially for 2027, clear timelines and ambitious orders for both originator and generic supply will be critical to avoid gaps in care of current LEN users and to expand the reach of this innovation.”

Roundup: The latest resources powering HIV & STI advocacy


Advocates are driving progress in HIV and STI prevention—guiding research, expanding access, holding powerful actors accountable and elevating community priorities. This roundup highlights advocacy in action, from new resources and policy frameworks to updates on the rollout of the latest prevention tools.

Lenacapavir Access—What’s the Latest?

Efforts are ramping up to roll out injectable LEN for PrEP amid new questions about pricing, volumes and supply timelines. LEN delivery is underway in Eswatini, Kenya, Lesotho, Nigeria, Zambia and Zimbabwe, and initial supply has entered Mozambique, South Africa and Uganda. AVAC, Access Bridge and the Coalition to Accelerate Access to Long-Acting PrEP are tracking the progress and facilitating a coordinated introduction.

At the same time, Médecins Sans Frontières (MSF) issued an open letter to Gilead Sciences, criticizing its refusal to sell LEN directly for use in MSF’s programs. The issue comes amid limited public information, as concerns mount that constraining LEN access to limited procurement channels and timelines risks slowing its uptake and excluding populations outside of government-led programs.

AVAC developed this summary of key information related to LEN to help drive transparency from all stakeholders and, hopefully, to accelerate the speed, scale and equity in its introduction.

Close watchers expect a further update today — April 14 at 9:00AM EDT — when leaders from the US Department of State, Gilead Sciences and the Global Fund participate in a discussion on “the LEN partnership and the evolution of US foreign assistance” at the Center for Strategic and International Studies (CSIS). Register here to watch the live webcast.


AVAC and partners launched three new national advocacy agendas on sexually transmitted infections (STIs) for Kenya, South Africa and Zimbabwe, to elevate STIs as national health priorities and accelerate actions on R&D and delivery of STI vaccines, diagnostics, prevention and care. “Each agenda reflects country-specific priorities, but, collectively, they elevate community voices, strengthen policy engagement and build regional momentum to ensure STI prevention, diagnosis and care receive the sustained attention they deserve,” said Alison Footman, PhD, senior program manager of STIs at AVAC. Join us for a webinar May 12 to learn more.


Closing the Evidence Gap for Pregnant and Lactating People

Pregnant and lactating people (PLP) have historically been excluded from biomedical research, leaving critical gaps in evidence and access to prevention tools. Building on global efforts, AVAC, the Pregnancy and HIV/AIDS: Seeking Equitable Study (PHASES) Project and a diverse group of stakeholders developed a clear action plan to help close this gap. Advancing Ethical Biomedical HIV Prevention Research for Pregnant and Lactating People, an article published in the journal AIDS, describes this effort and the essential role of communities in driving progress.


Global Prevention Coalition Releases New Global Access Framework for Country-Led Responses

The Global HIV Prevention Coalition (GPC) launched a new 2030 Global Access Framework outlining how, by 2030, countries can ensure that 90% of people in need of HIV prevention services have access and that 90% of people living with HIV are virally suppressed. This, in combination, would lead to a 90% reduction in new HIV infections globally. “Innovations, especially lenacapavir, have added to the array of prevention choices. History will judge us harshly if we as a global community fail to meet this scientific moment,” said Mitchell Warren, GPC Co-Chair on a recent webinar.


The Choice Agenda Webinar: The Injectors of Tomorrow are Here Today

Expanding PrEP access means meeting people where they are. The latest Choice Agenda webinar explored how community health workers and pharmacists are taking injectable PrEP beyond clinics and into homes, streets and communities. The Choice Agenda offers monthly webinars and a moderated listserv for advocacy on the latest in HIV prevention research – join the conversation here.