Global Health Watch: NIH-DoD Deal & NIAID Restructuring, Ebola Vaccine Progress, Gavi Funding Resumes, New US Foreign Aid Leadership

Issue 85

The US National Institutes of Health (NIH) signs a 10-year agreement that could move significant NIAID research funding to the Department of Defense, as NIAID separately proposes a major restructuring of its clinical research infrastructure. CEPI advances efforts toward a Bundibugyo Ebola vaccine amid funding gaps, while US funding for Gavi resumes and medical groups step in on vaccine guidance. And new leadership at the Department of State brings further change to the US foreign assistance system.

NIAID Funding and Research Infrastructure Uncertain

The US National Institutes of Health (NIH) signed a 10-year agreement with the US Department of Defense (DoD) to allow the transfer of NIH funds to DoD for projects that would “support the advanced development of medical countermeasures against pandemic influenza, chemical, biological, radiological, and nuclear (CBRN) threats, and emerging infectious diseases.” Funding will come out of the NIH’s National Institute of Allergy and Infectious Diseases (NIAID) budget and has the potential to shift hundreds of millions of NIAID-funded research into the military biodefense program. According to an NIH spokesperson interviewed by Nature, “This partnership will only take place on a project-by-project basis, and all research will be within the scope of NIH’s mission. There is no blanket transfer of funds.” Nature reports that NIAID is identifying projects that could move under the arrangement, while congressional Democrats have raised concerns that the agreement could give DoD access to money Congress appropriated for biomedical research at NIH. The agreement was signed last month but went largely under the radar until this week, when Representative Rosa DeLauro (D-CT) – ranking chair of House Appropriations – raised the issue during a hearing.

The agreement comes as NIAID is also proposing a significant restructuring of its clinical research infrastructure. Under a reorganization announced in late August, NIAID would do away with its Division of Clinical Research (DCR), which helps facilitate and coordinate NIAID research programs in the US and internationally, and redistribute clinical operations and oversight across other parts of the Institute. The proposal follows months of delays in renewal notices for NIAID’s HIV clinical trial networks and Centers for AIDS Research (CFARs), raising concerns about the future of the research networks and infrastructure that has supported major advances in HIV, TB and other infectious diseases.

IMPLICATIONS: While the NIH-DoD agreement is supposedly designed to support biomedical countermeasure research, there is substantial discretion over which projects move and how the money is ultimately used. If this agreement shifts infectious-disease research away from NIAID, it risks fragmenting an infrastructure built around peer review, scientific expertise, clinical research networks and long-term public-health priorities. The fact that this agreement was unilaterally executed by the Administration a month ago, without public knowledge or Congressional notification, points to a strong need for policymaker oversight of this process to ensure that Congressionally-appropriated biomedical research funding for NIAID is used for its intended scientific purposes and that changes to the Institute do not undermine or diminish the research capacity and leadership that was built over decades through bipartisan support.

These concerns extend beyond individual grants and institutions. A March Health Affairs analysis highlights how decades of US investment in international HIV research have generated scientific advances and research capacity that also benefit Americans—underscoring that global HIV research infrastructure is not separate from US health and scientific leadership. And a recent Think Global Health analysis of the Administration’s proposed budget cuts at NIH highlights the threaten to essential HIV research.

IDSA and HIVMA have separately warned that NIAID’s research infrastructure is already being destabilized by delayed renewals and a proposed restructuring of its clinical research program. Beyond an initial chart posted to the NIAID’s website, very little detail has been shared on the proposed reorganization, as advocates are monitoring for additional insight to be revealed on the restructuring in an uncharacteristically short deadline for public comment from September 9-18.

READ:

Vaccines Depend on More than Science

Nearly 100 days into the Bundibugyo Ebola response, there is still no approved vaccine, and the Coalition for Epidemic Preparedness Innovations (CEPI) says another $128 million is needed to prevent delays in later-stage trials of vaccine candidates. But CEPI also points to the response as evidence of how investments made before an outbreak can accelerate vaccine development: six pre-positioned research and response networks were activated within three days; three vaccine developers received funding within two weeks; and two experimental vaccines entered Phase 1 trials within 11 weeks. (There are now at least five vaccine candidates in clinical trials.) The experience underscores that rapid vaccine development depends on scientific breakthroughs and on sustained investment in the research networks, financing, partnerships and infrastructure needed to move quickly when a crisis emerges. Meanwhile, the US Administration announced it will release $600 million in Congressionally-appropriated funding for Gavi after more than a year of uncertainty, saying Gavi had committed to transitioning away from vaccines containing the preservative thimerosal—even though Gavi was already moving toward newer vaccines for broader public health benefits.

And in the US, leading medical organizations issued their own recommendations for COVID-19, flu and RSV vaccines as litigation over federal vaccine policy has disrupted the usual Centers for Disease Control and Prevention (CDC) recommendation process.

IMPLICATIONS: The speed of the Bundibugyo response was possible because research networks, manufacturing partnerships, regulatory preparation and vaccine platforms were established before the outbreak, but financing gaps could still slow the next stage. At the same time, the Gavi funding dispute and US medical societies stepping in to provide independent vaccine guidance demonstrate how political interference and instability in public health institutions can affect financing, recommendations, trust and ultimately access. Rapid scientific progress requires sustained investment in the institutions, expertise, partnerships and infrastructure that make it possible long before a crisis begins.

READ:

New Leadership for US Foreign Assistance

This week, Dr. Becky Bunnell, Principal Deputy Assistant Secretary of State for PEPFAR – and a distinguished HIV research and program leader for decades – announced her intention to step down from PEPFAR leadership. No one individual – or organization or policy maker or politician – is responsible for PEPFAR’s tremendous success. But Becky epitomizes all that has made PEPFAR great and impactful – commitment to evidence, data and, most importantly, the individual staff, partners, participants and clients that matter. Her retirement leaves a huge void.

At the same time, Andrew Veprek is the new political appointee leading the US Department of State’s foreign assistance, humanitarian affairs and religious freedom bureau. He replaces Jeremy Lewin, who moved to lead the Department’s policy planning office. Veprek previously led the Bureau of Population, Refugees, and Migration working to align humanitarian programs with the Administration’s immigration priorities. He has criticized “forever aid” and argued that foreign assistance should have a “clear and direct connection” to US foreign policy goals.

IMPLICATIONS: These leadership changes are another important development in the ongoing restructuring of US foreign assistance, as the State Department assumes greater control over programs previously managed through USAID and global health remains one of its three principal foreign-assistance pillars. Veprek has advocated for limiting open-ended assistance, increasing contributions from other countries and more closely aligning funding with Administration priorities. For global health programs, including PEPFAR, this new leadership raises new questions about how much Congressionally-appropriated funding is ultimately released, where it flows and what conditions may be attached.

READ:

The Impact Report: Two Decades of Good Participatory Practice in HIV Research

AVAC’s new Impact Report illustrates how meaningful participation – driven by Good Participatory Practices (GPP) – strengthens both the research process and the global impact of HIV prevention innovations.

Read the Report

What We’re Reading

Embedding Good Participatory Practice in PURPOSE 1

Ethical conduct of HIV clinical trial research improves as product developers, researchers, and other stakeholders become increasingly intentional about community partnership and engagement. When AVAC and UNAIDS developed the Good Participatory Practice (GPP) guidelines, the goal was to create a framework for trial funders, sponsors and implementers to engage communities across the HIV prevention research continuum. From trial design and implementation to results dissemination and access planning, GPP provides a guide for ensuring prevention products are responsive to community priorities and accessible to the people they aim to serve. For almost 20 years of GPP implementation, AVAC has collaborated with partners around the world to embed the principles within advocacy strategies and partnerships and cultivating a diverse network of advocates, civil society organizations, journalists, researchers, and implementers who champion GPP and are equipped to engage with, question, and influence HIV clinical trial research.

The Good Participatory Practice Guidelines, developed by AVAC and UNAIDS

Promoting Transparency and Accountability in Gilead’s PURPOSE Program

Gilead’s PURPOSE program is comprised of six clinical trials investigating long-acting injectable lenacapavir (LEN) for PrEP among diverse populations. PURPOSE 1, one of the two efficacy trials in the program, was conducted among cisgender women in South Africa and Uganda, while PURPOSE 2 expanded the reach to include men who have sex with men (MSM), transgender men and women, and gender non-binary people. Both trials found LEN highly safe and effective among participants. Beyond the clinical findings, the trials also demonstrated that embedding GPP principles promotes accountability, transparency, and meaningful community engagement throughout trial design and conduct.

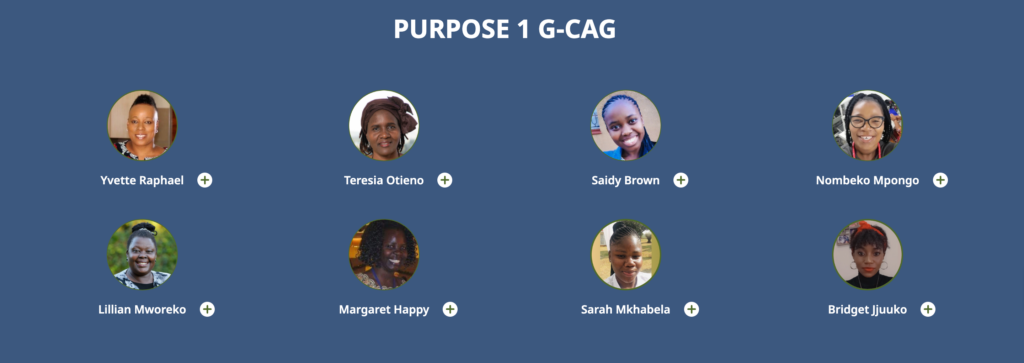
A case study of GPP implementation in PURPOSE 1 highlights how GPP strengthens ethical conduct and inclusion. AVAC staff and partners participated as members of the Global Community Accountability Group (GCAG), a formal mechanism for providing community perspectives on the trial. GCAG members provided community recommendations on trial design, including protocol considerations, participant recruitment and retention, and trial implementation to Gilead and researchers. Advocacy by the GCAG contributed to expansion of the inclusion criteria to enroll adolescents and to allow pregnant and breastfeeding people to remain in PURPOSE 1 after re-consent, reinforcing the principle that communities should help shape research that directly affects them and allowing the study to gather critical data on the safety and efficacy of LEN in populations often excluded from research.

Nombeko Mpongo of the Desmond Tutu Health Foundation and a member of the African Women’s Prevention Community Accountability Board served on the GCAG for PURPOSE 1 and describes how early involvement translated into influence and accountability:

“What was important was that communities were involved from the beginning. We received the protocol early, before the study began, and had the opportunity to scrutinize it and identify what we thought needed to change. One of the issues we raised was ensuring that women who became pregnant during the study would not automatically be excluded, so we could better understand prevention during pregnancy. We were not there as tokens—we took ownership of our role in the GCAG. We made sure Gilead was accountable to us, and we were also accountable to our communities. It was a flow of accountability in both directions.”

Through this structured forum and sustained engagement, community concerns were heard, researchers and the developer remained responsive, and the priorities of women and young girls remained central to decision making.

Members of the PURPOSE-1 GCAG

Championing Good Participatory Practice

Impactful community engagement in clinical trials requires sustained investment in community leadership, scientific literacy, and trusted partnerships. Years before PURPOSE 1, AVAC and partners established the Coalition to Accelerate and Support Prevention Research (CASPR), an Africa-led advocacy coalition of civil society organizations working to advance biomedical HIV prevention research and equitable access to proven HIV prevention products. CASPR supported a network of advocates with the knowledge and relationships to engage with emerging HIV prevention research. Many of these advocates went on to serve on the PURPOSE 1 GCAG while remaining connected to the broader communities and networks they worked with through CASPR. This helped extend engagement and understanding of the trial beyond the GCAG, and strengthened the pathway from engaging in research to product introduction and access planning.

As Navita Jain, Senior Program Manager and Team Lead for AVAC’s Partnership Network Team explains, “CASPR provided the connective tissue that made meaningful engagement possible. Advocates weren’t starting from scratch when they joined the GCAG—they were already informed, connected and prepared to engage, and could bring that knowledge back to their communities well before conversations about rollout began.”

Because AVAC, CASPR partners, AWPCAB and the broader network of informed advocates were already equipped with the expertise, partnerships, and communities’ trust, they helped bridge the transition from research implementation to disseminating trial results and planning for access. This continued engagement with Gilead, funders and decision makers supported community confidence in the results and accelerated momentum toward equitable LEN rollout in comparison to the delivery of previous PrEP products. This contribution was recognized when Yvette Raphael, Executive Director of APHA, accepted the American Association for the Advancement of Science’s (AAAS) Mani L. Bhaumik Breakthrough of the Year Award on behalf of CASPR, AWPCAB, and the GCAG, affirming the critical role of community advocacy in LEN’s development.

Yvette Raphael, the Executive Director of APHA and a PURPOSE-1 GCAG member accepted the AAAS Breakthrough of the Year Award.

From Research to Rollout

GPP guided community engagement in PURPOSE 1, creating meaningful opportunities for advocates to influence the trial. However, the GPP guidelines recommend continued engagement to shape access and rollout once a product has been proven safe and effective, achieves regulatory approval, and becomes available. After the PURPOSE 1 results were announced, Gilead discontinued the GCAG, even though many of the decisions that would determine equitable access, including licensing, pricing, manufacturing, and product introduction, were still ahead. For HIV activist Saidy Brown, a member of CASPR’s Young Women’s HIV Prevention Council (YWHPC) and GCAG member, continuing the GCAG through product introduction would have been a natural extension of the partnership that began during research:

“We were there from the beginning, supporting the research, and it would have made sense for that partnership to continue through rollout. As much as communities supported the trial, there was also an opportunity to bring that support back to communities as LEN became available. Keeping GCAG members engaged through introduction would have helped create that continuity from research to rollout.”

While the GCAG was discontinued, the networks and relationships built through CASPR have provided a platform for advocates to continue pushing for equitable access, with demands including: a role in access planning, speed and equity in rollout, price transparency, and accelerated access to generics. As a result, donors and ministries of health are engaging with and investing in civil society partners to secure community buy-in, inform rollout planning and generate demand. While LEN rollout across early adopter countries reflects this community leadership, advocates remain vigilant in identifying and addressing challenges around equitable access.

Even so, global access has been far from perfect. Advocates’ demand that all PURPOSE efficacy trial countries be included in voluntary licensing agreements has not been met, reflecting that strong incorporation of GPP during a trial does not automatically translate into access once the trial is over; the work of and commitment to engagement must carry through. Nevertheless, the positive lessons from PURPOSE 1 are informing AVAC’s recent work in Merck’s EXPrESSIVE program assessing the efficacy of a new monthly oral PrEP pill. As new HIV prevention products advance through the research pipeline, AVAC and partners will continue to call for developers, donors and other stakeholders to apply the lessons and practice of GPP – strengthening community engagement throughout research & development, policy, and product introduction so that scientific innovation translates into equitable access and real-world impact.

⮐ Return to the the Impact Report

Harnessing Artificial Intelligence for HIV: Breakthrough or Buzzword?

This presentation by Izukanji Sikazwe, Head of HIV at The Global Fund, during AIDS 2026 explores how the field might harness artificial intelligence in response to HIV. Izukanji Sikazwe unpacks what AI must be, what we must build, and the promise of AI in HIV programming.

Global Health Watch: Steinem’s Legacy, US Global Health Aid Cuts; OMB Grant Rule Delayed; Future of Global Health Reform

Issue 84

We’ve lost another champion for global health and reproductive rights this week: Gloria Steinem, the pioneering feminist and activist who spent decades fighting for gender equality, reproductive choice and the power of people to shape the decisions that affect their lives. This is a reminder to continue questioning who has a voice, who gets to decide, and why bodily autonomy is a fundamental right.

This week’s issue addresses those questions: a new analysis finds US bilateral health agreements could dramatically reduce global health funding by more than half; Congress has temporarily blocked the White House OMB’s effort to expand political control over federal grants; and, as global health architecture reform moves forward, civil society is demanding a role in shaping what comes next.

Bilateral Health Deals Could Cut US Health Aid by 59%

A new analysis from Public Citizen and Partners In Health finds that the US Administration’s bilateral (government-to-government) health agreements would drastically reduce US global health funding and foreign assistance to 18 recipient countries by 59 percent ($2 billion) by 2030 compared to pre-2025 funding. This is despite the US Congress maintaining relatively stable global health appropriations. The organizations analyzed 18 available memoranda of understanding (MoU) noting that the Administration “has kept the public in the dark about the full details of its plans for the future of US support for global health…” and “the MOUs warn of a disturbing potential underspend of congressionally appropriated global health dollars.” The agreements require countries to increase domestic health spending as US support declines. However, in 11 of the 18 countries, those domestic resource mobilization commitments would not fully replace the planned reductions in US funding.

IMPLICATIONS: The analysis raises significant questions about whether the Administration’s “America First” global health strategy toward “country ownership” and “self-reliance” is actually achievable. Instead, the analysis posits that the accelerated transition to sustainable domestic financing actually constitutes a rapid withdrawal of critical US support that these countries may not have the fiscal capacity to replace. The analysis further conveys that many of these deals contain worrisome conditionalities and performance metrics tied to funding, which may not be attainable as bilateral funding to support in-country programs are greatly diminished to begin with. The authors also exposed a disconnect between the global health funding Congress has appropriated and the substantially lower spending envisioned by the Administration under the bilateral agreements, with potential consequences for HIV, TB, malaria, Ebola and other health programs. The Department of State said it intends to spend all congressionally-appropriated global health funds, but where and how funding not included in the bilateral agreements will be spent is the outstanding question.

READ:

US Congress Votes to Delay White House Rule Politicizing Federal Grants

Members of the US House of Representatives on both sides of the political aisle voted to pass a continuing resolution (CR) for fiscal year 2027 (FY 27) appropriations. This CR was previously approved by the Senate in early August, which authorizes government spending until December 11, delays a government shutdown on September 30 (the end of the US fiscal year), and, at least for now, delays implementation of the White House Office of Management and Budget’s (OMB) controversial proposal to give political appointees greater authority over federal grantmaking. Last month, in a stopgap spending bill released by Senate appropriators, Democrats and Republicans joined in adding a provision that would prevent the OMB rule from taking effect until at least December 11, while Congress negotiates broader government funding measures. The proposal was originally slated to go into effect on October 1, but opposition from both Democratic and Republican appropriators slowed the path forward.

IMPLICATIONS: This temporary delay is important, allowing more time for advocacy and for potential litigation to formulate. However, if implemented in December (or any time), the rule would fundamentally reshape the US research enterprise by injecting political considerations into grantmaking, weakening peer review and undermining the international collaborations that drive progress against HIV, TB, emerging infectious diseases and other global health challenges. The Senate’s actions last month and the bipartisan agreement on the CR suggest that the months of public opposition and advocacy from the advocacy and scientific community may be beginning to influence policymakers. The Senate’s intervention is one of the first signs that resistance to the OMB proposal extends beyond the scientific community and into both parties in Congress. 

Evidence-based decision-making – not politics

The risk of having public health research and recommendations guided by politics as proposed by OMB is real, as evidenced by the ongoing politicization of US vaccine research and policies. To ensure Americans get credible, evidence-based recommendations that previously came from the CDC, the American Medical Association (AMA) and the Vaccine Integrity Project, which is based at the University of Minnesota’s Center for Infectious Disease Research and Policy (CIDRAP), initiated a collaborative effort to conduct a comprehensive review of evidence for vaccines of the 2026-2027 respiratory virus season. They published their findings this week in the Journal of the AMA (JAMA).

Read the Article

Future of Global Health Architecture 

As the WHO-hosted Joint Task Force on Global Health Architecture Reform meets in person for the first time this week, the Health Architecture Reimagined (HEAR) CSO Steering Committee issued a letter urging the Task Force to put equity and meaningful community and civil society leadership at the center of reform, while also strengthening regional platforms and protecting access as financing shifts. Meanwhile, a new Council on Foreign Relations analysis of 67 health architecture reform proposals finds consensus around shifting decision-making to countries and regions, aligning donor funding with country priorities, strengthening national health systems, expanding regional roles and diversifying financing.

IMPLICATIONS: While the analysis and civil society advocacy show agreement on the direction of global health architecture reform, the outstanding question of how to get there remains. The CFR analysis highlights the key challenges around who pays versus who decides, what is gained or lost by moving from disease-specific programs to integrated health systems, and which functions belong at global versus regional levels. As these decisions are made, HEAR CSO argues that reform must be judged not only by efficiency, but by whether it advances equity, protects access and gives affected communities meaningful power. Moreover, these processes are all unfolding in the midst of leadership transitions at WHO, the Global Fund, Unitaid and the Medicines Patent Pool, amongst others.

READ: 

What We’re Reading

Global Health Watch: Legacies of Parton & Goosby, expiring global health funds, Jeremy Lewin’s move, Ebola funding & vaccine R&D

Issue 83

This week, the global health community lost a powerful, if unlikely, champion in Dolly Parton. She used her singing celebrity to support science and public health, including a $1 million investment that supported early research connected to Moderna’s COVID-19 vaccine. She was a supporter of literacy, marginalized communities and HIV awareness and care. Her legacy is a reminder of what it looks like to use influence to build trust in science, which couldn’t be more important today as vaccines, public health and LGBTQI+ communities are continually undermined and politicized.

Speaking of leadership, longtime leader Eric Goosby officially retired this week. Eric served as the US Global AIDS Coordinator and led the President’s Emergency Plan for AIDS Relief (PEPFAR) from 2009 to 2013 under President Barack Obama. But before he led PEPFAR and since he returned to UCSF, Eric has been a compassionate doctor, a passionate advocate, and a tireless defender of science and human rights. His colleague and mentee, mike Reid, posted this video from Eric’s retirement celebration.

Also this week, members of the US Congress demanded that the Administration release billions in congressionally-appropriated global health funding before it expires; another leadership change is underway at the Department of State, which oversees the transformation of US foreign assistance; and in the DRC, the Ebola response is making progress even as inadequate funding threatens efforts.

Congress Raises Alarm Over Expiring Global Health Funds and PEPFAR Restructuring 

Democratic members of the US Congress are pressing Secretary of State Marco Rubio and OMB Director Russell Vought to release billions in congressionally-approved foreign assistance before it expires on September 30. In a new letter, they note that $7.5 billion remains unobligated, including more than $3 billion for Global Health Programs. They object to OMB’s reported decision to reserve approximately $1.35 billion in FY2025 global health funding for the closeout costs of USAID rather than health programs Congress funded. They also question plans for PEPFAR, citing the two-million decline in people reported as receiving PEPFAR-supported HIV treatment in 2025 and asking the Administration to explain how proposed reductions in CDC’s implementing role will affect treatment continuity, HIV prevention, surveillance, technical expertise and community-based programs. They are seeking answers by September 9.

IMPLICATIONS: If billions in congressionally-appropriated global health funding are allowed to expire, or used to dismantle USAID rather than support programs, the effects could exacerbate the disruptions already being documented across PEPFAR and other health programs. Additionally, reducing the CDC’s role would shift how PEPFAR is implemented, and also erode surveillance, laboratory, technical and data systems that help countries maintain HIV services and detect wider health threats.

READ:

Jeremy Lewin Leaves Foreign Assistance Role

Jeremy Lewin officially stepped down as head of the US Department of State’s foreign assistance bureau and is now serving as the Department’s Director of Policy Planning. He will advise Secretary of State Marco Rubio on key foreign policy matters. An original DOGE agent at the beginning of this Administration, Lewin was one of the architects of the Administration’s overhaul of US foreign assistance following the dismantling of USAID, including the shift toward bilateral government-to-government agreements and the development of the America First Global Health Strategy. Lewin will now oversee the Bureau of Economic, Energy and Business Affairs and continue representing the US in G7 and G20 development discussions. 

IMPLICATIONS: Lewin’s departure is yet another leadership transition for US foreign assistance. This happens as the State Department works to implement a redesigned aid and global health system, while being unable to obligate billions in congressionally- appropriated funding. The big question for global health now is who will lead implementation of the new foreign assistance architecture that Lewin helped design, including the bilateral agreements intended to reshape PEPFAR and other US global health programs. 

READ:

DRC Ebola Response Gains Ground as Funding Gaps Threaten Progress 

The Ebola Bundibugyo outbreak in the Democratic Republic of the Congo (DRC) continues to expand, with more than 560 new cases in the last week. WHO reports improvements in contact tracing and testing and issued interim guidance on prevention and control to help countries safely continue routine immunization activities during an outbreak. However, transmission remains high and funding gaps threaten the immediate response and the development of preventive vaccines. CEPI, which supports several potential Bundibugyo vaccine candidates, says it faces a shortfall of hundreds of millions of dollars for vaccine R&D, even as it launched trials this week of its fifth Bundibugyo-specific virus vaccine candidate in response to the escalating epidemic. In Uganda, the WHO officially declared its related outbreak over.  

IMPLICATIONS: Resources are needed now to prevent new infections, just as sustained investment in vaccine R&D is needed to ensure future outbreaks can be minimized. As we highlighted last week, cuts to foreign assistance and weakened surveillance and response infrastructure have compounded insecurity and other challenges confronting the DRC response. And while vaccines could help prevent Bundibugyo if proven safe and effective, they cannot replace surveillance, health workers, laboratories, community engagement and health systems needed to prepare and respond.  

READ:

New Issue of PxWire

AVAC’s latest issue covers PEPFAR funding cuts; generic licensing of alimatravir; and the latest developments for long-acting treatment and bNAbs for prevention.

Read Now

What We’re Reading

Webinar

Evolving Oral PrEP Guidance for Cis Women: What do we know, and what will it take?

Join The Choice Agenda for a conversation with Heather-Marie Anne Schmidt of UNAIDS, Simon Collins of HIV i-Base, Jenell Stewart of the University of Minnesota and Raphael Landovitz of UCLA on evolving PrEP science, discordant guidelines and what it will take to advance PrEP equity for cis women, trans and non-binary people.

Register

PxWire Volume 16, Issue 3

This issue showcases updates presented at the AIDS 2026 conference in Rio de Janeiro, Brazil. As the field continues to grapple with the impact of PEPFAR funding cuts on HIV services, amfAR shared their latest analysis from the PEPFAR Pulse Study. AVAC’s latest infographic unpacks the current status of generic licensing agreements for long-acting PrEP products, including alimatravir (AMI), reflecting significant progress in speeding up access as new products enter the market, while also highlighting persistent and worrying gaps in these agreements. Recent trials on long-acting treatment and broadly neutralizing antibodies (bNAbs) for prevention were also shared at the conference. A new weekly pill for HIV treatment demonstrated non-inferiority, while a combination of two bNAbs did not provide protection from HIV. Both results provided important insights and implications for the current status of the HIV prevention and treatment pipelines.

Read below or download a PDF version of this issue.

Progress in PrEP Uptake

Source: PEPFAR Pulse Study

  • Significant challenges persist in the wake of cuts to PEPFAR programs, as the ripple effects continue to be felt across the field and organizations grapple with how to maintain services with fewer resources.
  • At the start of the conference, amfAR released a report detailing the results from their recent PEPFAR Pulse study. The study provides the first concrete evidence and key details on the impact of PEPFAR cuts: surveying 166 organizations in 46 countries, they found that nearly 2,000 service sites had been forced to shutter. 
  • The results from the study were significant: almost no organizations were able to fill the funding gap with other donors. Services for key populations (KPs) were “decimated”: 73% of implementing partners stopped at least one KP service and 67% stopped outreach services. 
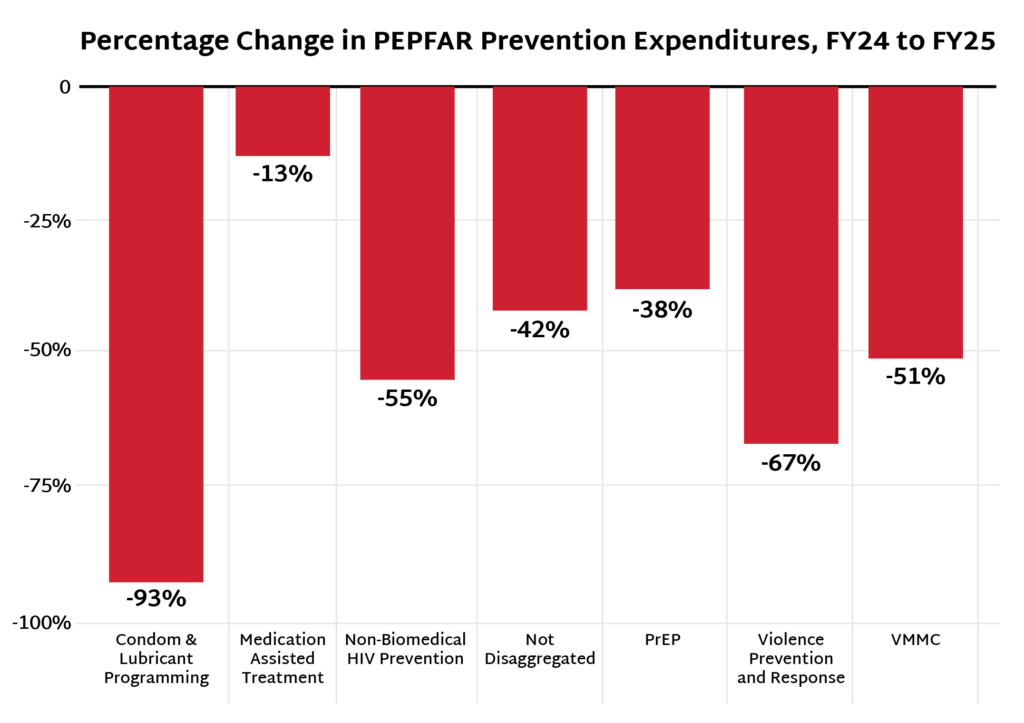
  • HIV prevention services overall took a huge hit: PEPFAR expenditures for condoms and lubricants were almost completely cut, while non-biomedical HIV prevention and VMMC expenditures were cut in half and PrEP expenditures were reduced by 38%. Expenditures for associated services such as violence prevention and response were also cut by two-thirds. 
  • As a result, almost half of respondents reporting that they had halted key prevention activities such as condom or PrEP distribution. Two-thirds reported interruption of PMTCT and nearly one in four stopped providing prevention of mother-to-child transmission services entirely. As outlined in amfAR’s accompanying JIAS article analyzing service delivery data from PEPFAR-supported facilities, these cuts have resulted in drastic reductions in the number of people served.
  • Additionally, the release of UNAIDS’ United to End AIDS special report and a companion KFF-UNAIDS analysis shared results on the global picture of the AIDS epidemic and donor funding landscape.   
  • The report shows HIV financing entering one of its most precarious periods in decades, with international assistance declining 18% between 2024 and 2025. Donor government funding fell by $2.1 billion in 2025—the largest annual decline since global HIV funding began scaling up—and epidemiological progress has stalled, with new HIV infections remaining essentially unchanged for the third consecutive year. 
  • Taken together, these findings underscore the broader challenges facing the field in effectively translating scientific progress into the impact needed to end AIDS as a public health threat by 2030. 

PrEParing for New Products

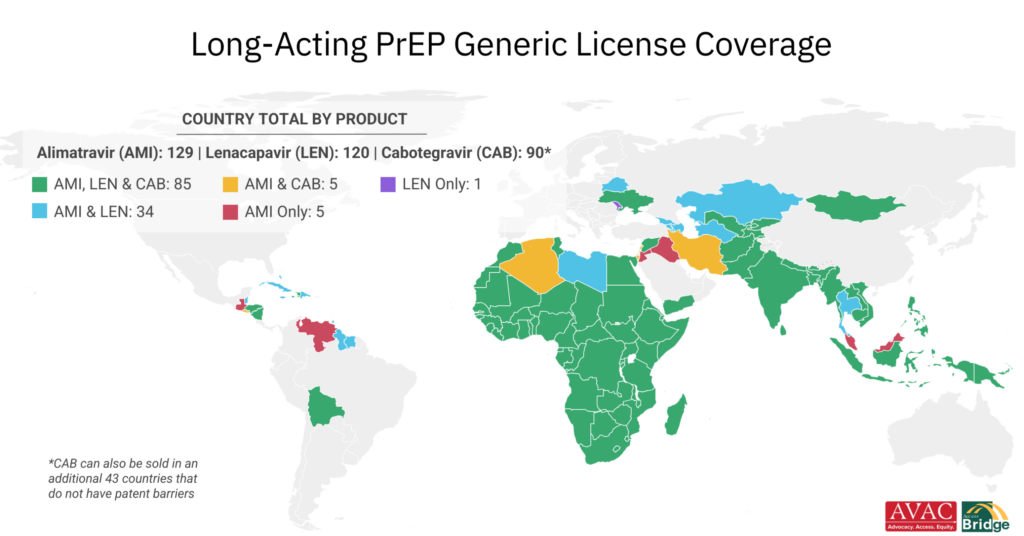
  • Just before the AIDS 2026 conference, Merck/MSD announced that it had signed bilateral voluntary licenses for their investigational monthly PrEP pill, known as alimatravir (AMI, or MK-8527) with seven generic manufacturers to supply 129 low- and middle-income countries.  
  • Notably, the seven generic manufacturers for AMI include three based in Africa (Kenya, South Africa, and Uganda). This is an important step forward to secure local continuity of supply in high-burden countries. 
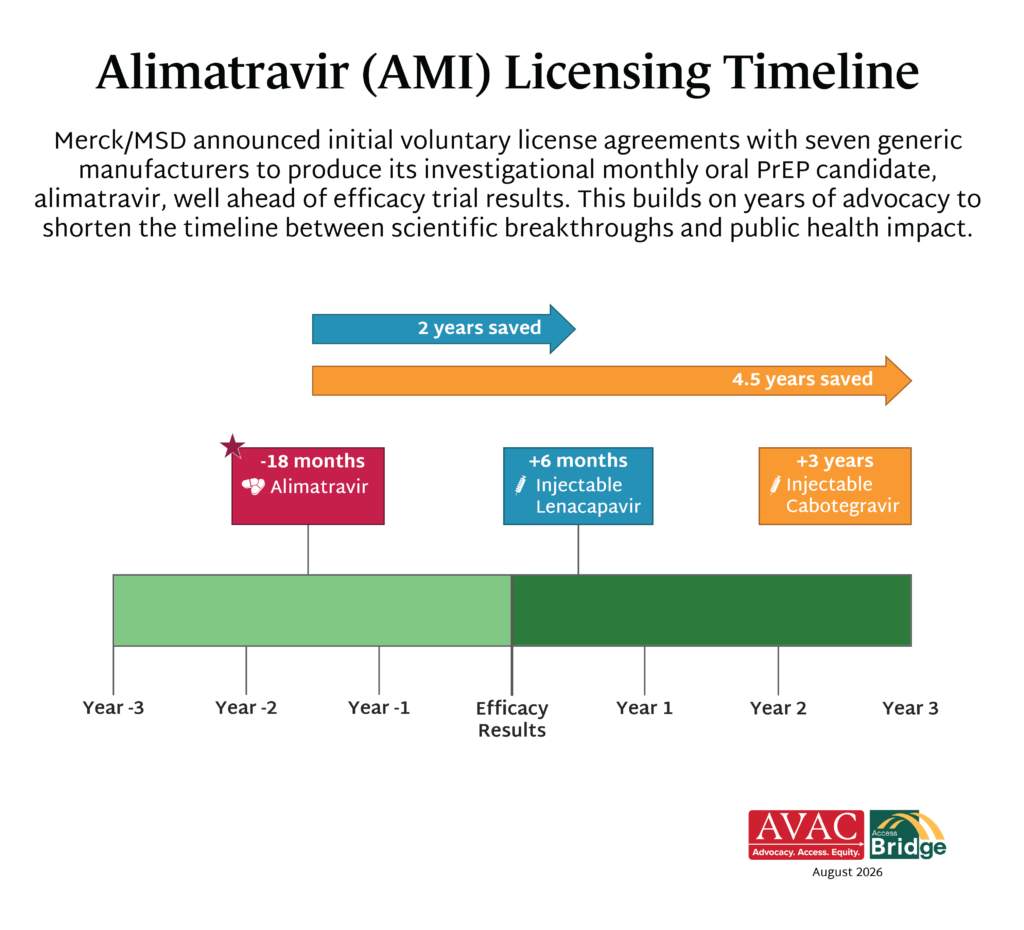
  • Merck/MSD’s decision to provide generic manufacturing agreements more than a year out from efficacy trial results is unprecedented. The move reflects the impact of deep engagement with advocates throughout the planning and implementation of the EXPrESSIVE clinical trial program and responsiveness to longstanding calls to accelerate the research to rollout process. 
  • But not all advocacy demands were met. A number of countries – including Brazil, the host country for AIDS 2026 and a site for clinical trials of AMI (and CAB and LEN, previously) – was again left out of the voluntary license territory. (Merck/MSD did subsequently announce they signed a memorandum of understanding with Fiocruz, a Brazilian manufacturer, to supply AMI for Brazil and the region, but the terms, timing and next steps remain unclear.) 
  • As the map above demonstrates, this reflects a broader trend of excluding Latin American countries, as well as some Asian countries, from voluntary licenses despite their participation in clinical trials for the same products, largely due to their World Bank economic categorization, and not their epidemiologic reality.  
  • Furthermore, these agreements do not address the access disparities in high-income countries that disproportionately impact key populations – men who have sex with men, people who use drugs, sex workers, transgender people, and others – especially in the United States where access to prevention products hinges on health insurance coverage. 
  • The World Trade Organization’s TRIPS Agreement does explicitly allow governments compulsory licensing under specific public health crises or anti-competitive practices. This could potentially authorize the production and use of a patented drug without the consent of Merck/MSD, but it can be a lengthy process that further delays access. An extended voluntary license to all low- and middle-income countries would allow for the quickest rollout and maximum impact. 

What is Generic Licensing?

  • Generic drugs are bioequivalent to originator products and are produced by a generic manufacturer. They are sold at much lower prices than the originator drug, usually because they are not manufactured in high-income countries and can make use of economies of scale.
  • Generics manufacturers are allowed to sell their version of the product once the product’s patent and terms of exclusivity expire—usually after 10-20 years. However, a developer can choose to grant a voluntary license before patent expiration, allowing generics to be manufactured and marketed earlier. Original drug developers can either grant this license directly to manufacturers or via the Medicines Patent Pool.
  • The developer decides which countries the license covers; normally high-income countries are excluded, as the developer will continue to sell the brand product in these markets at higher prices for a profit.
  • Countries without a voluntary license to use generic versions of an originator drug may declare the drug to be in the public interest and issue a compulsory license enabling the purchase of the less expensive drug from generic manufacturers.

Time Saved on AMI Generics Licensing

  • The successive introduction of each new PrEP product has gone faster than the previous one, including notable reductions in the amount of time to establish licensing agreements with generic manufacturers. 
  • Granting voluntary licenses while clinical trials for AMI are still enrolling, before it is known if the product is effective, sets a new benchmark for the field, potentially eliminating years of delay between evidence, licensing and generic production.  
  • This accelerated timeline gives the field ample opportunity to plan for broad and rapid access to AMI and should help preempt the supply constraints currently facing LEN and CAB. 
  • Local manufacturing in the three African countries included in the generic licensing agreement should also facilitate faster access in the region with fewer supply constraints. 

The Latest R&D in the Prevention Pipeline

The latest development for long-acting treatment research

  • The HIV treatment pipeline continues to evolve, especially around long-acting options. Over the past year, AVAC has added long-acting treatment (LA-ART) to our pipeline tracking efforts, reflecting the evolving continuum across ARV product development and the need for a comprehensive agenda for the development of novel and longer-acting products that includes PrEP, PEP, and treatment. 
  • At AIDS 2026, Merck and Gilead presented detailed results from the Phase 3 ISLEND trials, showing that an investigational weekly oral single-tablet treatment regimen combining islatravir (ISL) from Merck/MSD and lenacapavir (LEN) from Gilead sustained viral suppression as effectively as daily oral antiretroviral therapy (ART) at week 48; the studies will continue to week 96. 
  • Importantly, trial participants in ISLEND-2 reported strong satisfaction with the ISL/LEN treatment option and felt that it was easier to manage compared to standard HIV treatment options.
  • Given the mechanisms of action of ISL and LEN, which target HIV at multiple stages of the viral life cycle, the combination regimen could offer an important, novel option for people with virologically suppressed HIV. The companies plan to file ISLEND data with regulatory authorities globally, with a potential launch in 2027.  
  • These Phase 3 data are an exciting indication of the evolving HIV treatment landscape, with additional long-acting options in the pipeline and oral options for people who may not prefer an injection. 

Combo bNAbs get even more complicated

  • Broadly neutralizing antibodies (bNAbs) remain at the center of research toward immune-based prevention. In particular, researchers are advancing the concept of “combo AMP,” i.e., passive delivery of a combination of bNAbs targeting multiple sites on the viral envelope, achieving broader and stronger protection than with a single bNAb.   
  • At the conference, the CAPRISA team from Durban, South Africa, announced results from the CAPRISA 012c Phase 2 trial examining a combination of two bNAbs as prevention.
  • The trial, conducted with approximately 1,100 young women in South Africa and Zambia, found that a six-monthly combination of the CAP256 and VRC07 bNAbs was safe, but there was no statistically significant difference in HIV incidence rates between the bNAb and placebo arms, meaning it did not provide protection against HIV acquisition.
  • One reason for the lack of efficacy was the high rate of viruses detected amongst the women who acquired HIV that were resistant to one or both of the bNAbs. This was unexpected, and one conclusion from this trial is that the evolving sensitivity of circulating viruses to the bNAbs manufactured for trials should be carefully considered.
  • Antibody research has always been about more than product development. The CAPRISA 012c study continues to deepen understanding of HIV and the immune system, and will continue to inform vaccine design, cure research and the next generation of prevention strategies. But it is still not clear if bNAbs can be a prevention option on their own.  

Prevention Playlist

AVAC develops a wide range of resources to inform decision making and action. Check out the latest:

Join

Use

Watch/Listen

Read

Percentage Change in PEPFAR Prevention Expenditures, FY24 to FY25

This infographic, with data featured in amfAR’s PEPFAR Pulse study, examines the percentage change in PEPFAR prevention expenditures from FY24 to FY25. Significant challenges persist in the wake of cuts to PEPFAR programs, as the ripple effects continue to be felt across the field and organizations grapple with how to maintain services with fewer resources. 

Global Health Watch: NIH reopens South Africa Research Funding; DRC Ebola Strains Outbreak Response; WHO + FDA Leadership Shifts

Issue 82

The US National Institutes of Health (NIH) lifted research funding restrictions on South Africa; the DRC’s Ebola outbreak grows, exposing the consequences of weakened outbreak-response systems; and leadership changes at the World Health Organization (WHO) and the US Food and Drug Administration (FDA) raise questions about the future of global health decision-making.

NIH Reopens Research Funding to South Africa

The US National Institutes of Health (NIH) lifted its ban on funding research in South Africa. This comes after 18 months of “holding all research awards” for NIH research partnerships with South African institutions as the country was designated a “country of concern” alongside China. As Science reports, an internal memo notes that the “[NIH] decided it was exempt from a February 2025 executive order…that halted ‘foreign aid or assistance’ to South Africa” because “the Foreign Assistance Act of 1961 does not govern NIH funding.” The lift of this order reopens the door to new grants. However, the NIH also announced that South African scientists will no longer be eligible to receive training grants from its Fogarty International Center, because the country is upper middle-income and part of the G20. This follows last month’s announcement from the Department of State that it will phase out PEPFAR support to South Africa.

IMPLICATIONS: South Africa is one of the world’s most important HIV, TB and infectious disease research centers – built through decades of diplomacy and partnership with the NIH and US State Department, with numerous South African scientific leaders of today partnering with the Fogarty International Center. This is part of a wider unraveling of this decades-long scientific partnership spanning HIV research, treatment and prevention, emanating from false accusations made by the White House against the South African government for “not doing enough” to address unfounded claims of discrimination purportedly against the country’s white Afrikaner community. While this week’s reversal of the ban restores an important piece of that scientific collaboration, the larger relationship remains strained, including the planned PEPFAR phase out. US investments in PEPFAR and NIH partnerships in South Africa have resulted in significant contributions and innovations in the treatment and prevention of HIV, TB and other infectious diseases for people around the world, including in the US. For the HIV field especially, this reversal shows the interconnectedness of the research partnerships and bilateral programs and why both research and programmatic funding matter. The simple restoration of scientific collaboration, while continuing to withdraw and erode programmatic infrastructure will stifle scientific progress when it relies on strong public health infrastructure and partnerships made possible through PEPFAR.

READ:

DRC Ebola Outbreak Illustrates Impact of Foreign Aid Restrictions 

The ongoing Ebola Bundibugyo outbreak in the Democratic Republic of the Congo (DRC) is now the country’s deadliest Ebola epidemic and the second deadliest ever recorded. At an emergency WHO meeting, Director-General Tedros Adhanom Ghebreyesus said, “We must be frank: The epidemic is far from being under control… It had a big head start, and we are still playing catch-up.” WHO says it could still be brought under control within approximately three months, but only if resources and response capacity are rapidly scaled up. WHO figures report that only 60 percent of the $115 million needed to finance the response has been raised. Currently, there is no licensed vaccine or treatment for the Bundibugyo strain. Many new cases are appearing outside known transmission chains, which indicate infections are continuing to spread undetected. 

READ:

Leadership Shifts at WHO and US Food and Drug Administration

The WHO and US Food and Drug Administration (FDA) are undergoing leadership changes. WHO’s chief scientist and Assistant Director-General for health promotion and disease prevention and control Jeremy Farrar will leave at the end of September. This latest departure comes amid WHO’s challenge to continue charting its future in the face of reduced donor funding, a smaller senior leadership structure, and the end of Director-General Dr. Tedros Ghebreyesus tenure later this year. Meanwhile, in the US, White House adviser on the Domestic Policy Council, Dr. Heidi Overton was nominated to lead the FDA as commissioner. She helped shape several of the Administration’s health initiatives, including its recent overhaul of childhood vaccine recommendations and is a proponent of the government’s anti-abortion policies. Her nomination comes after months of turmoil and a leadership vacuum at the FDA, which saw Marty Markary depart from the role in May after a short tenure of 13 months. Some Senators who are now debating her nomination are questioning her role in the recent vaccine order as they prepare for confirmation hearings.

IMPLICATIONS: As WHO is being forced to redefine its role and priorities amid shrinking resources, the US FDA is facing significant scrutiny and political pressure over vaccines and scientific decision-making. For global health and HIV, leadership stability and scientific independence at both agencies matter beyond the internal structure as WHO normative guidance and FDA regulatory decisions will determine which products move forward, how quickly they reach countries and communities who need them. Many national regulatory authorities around the world rely heavily on FDA’s rigorous regulatory review and approval processes to inform their decision-making in local approval, procurement, and implementation of new and emerging biomedical innovations. Similarly, countries without the capacity or expertise to independently develop treatment and prevention guidelines rely heavily on WHO’s normative guidance to ensure health policies are grounded in the latest evidence. The looming question at the FDA is whether its leadership and decisions will continue to be guided by evidence, as political pressure increasingly shapes the ideologues may potentially helm the world’s premier regulatory agency. as political pressure increasingly shapes the agency’s leadership and priorities.

READ:

What We’re Reading

The Latest Resources from AVAC: Advancing Science, Expanding Access

Scientific breakthroughs accelerate HIV prevention—but only when they are matched with bold advocacy, sustained investment and equitable access. This month’s roundup highlights key prevention news, developments and takeaways from AVAC and explores what’s needed and what’s next to ensure the latest innovations move beyond headlines and into the hands of the communities that need them most.

Science Creates the Possibilities, Communities Create the Future

AIDS 2026, the 26th International AIDS Conference, took place 26-31 July 2026. AVAC and partners were there, convening critical conversations, bringing timely analysis and advancing advocacy to turn scientific breakthroughs into public health impact. From the mainstage to the hallways, the importance of moving from innovation to impact rang clear. As AVAC Program Manager Grace Kumwenda shares in her reflections on the conference, “we need to move from products to programs at scale; from clinics to community-centered delivery platforms; from product-focused interventions to choice-based prevention; and from scientific breakthroughs to political courage, financing, solidarity and accountability.”

AVAC’s coverage highlights what it will take to act on evidence with equity and speed. Explore conference highlights, key takeaways and resources from Rio here.


Prevention Access News 

High Demand for LEN Faces Real-World Supply Challenges 

AVAC’s Mitchell Warren recently spent a week in Zambia with AVAC partner Ascend Futures Foundation, which is playing a leading role in the introduction of injectable lenacapavir (LEN) for PrEP.  Mitchell was joined by Science’s Jon Cohen, who was reporting on the rollout of LEN and the real-world challenges being faced on the ground, including lack of supply. While LEN has met critical milestones with record speed, AVAC, Access Bridge and partners continue to advocate to ensure the science is matched with political will, financing and community leadership to get LEN to the people who need it most. “Science alone doesn’t change the world – people do,” said Mitchell in the article.

Merck Announces Global Access Plans for Monthly Oral Alimatravir (AMI)

On July 24, Merck announced that it granted seven direct licenses to generic manufacturers – including three in Africa – to produce and market their investigational monthly pill for HIV prevention, known as alimatravir (MK-8527, or AMI), in 129 countries while Phase 3 clinical trials are still enrolling. Since 2012, each successive PrEP introduction has gone faster than the previous one, yet the time to market and to public health impact remains too slow. AVAC is committed to changing that, and has worked to influence trial design and implementation, and to ensure strong engagement with community representatives in the research program. These efforts coincide with broader AVAC efforts to engage stakeholders in preparation for results from the trials, and, in the case of efficacy, building the foundation for a swift path to wide-scale uptake and access.

AVAC partner Kenneth Mwehonge of HEPS Uganda told the New York Times: “Our engagement with pharma has always been fights, but it is amazing to sit with them and have them say, ‘We are learning from the other products’. It all sounds good for now, but we will wait to see how it’s put to action.”

Learn how AVAC and partners have shaped alimatravir trials.

Accelerating policy approval and uptake of the dual prevention pill in Zambia through early stakeholder engagement

The Dual Prevention Pill (DPP), a combination of daily oral PrEP and combined oral contraception, offers a novel, female-controlled option for HIV and unintended pregnancy prevention. However, promising technologies like the DPP often face delays in regulatory approval and uptake due to limited stakeholder involvement early in the introduction process. This new article in AIDS Care, authored by AVAC Fellow alum Rhoda Msiska, AVAC Senior Program Managers Kate Segal and Cindra Feuer, and Dr. Newton Donkola of Copper Rose Zambia, illustrates how early, multisectoral stakeholder engagement could accelerate DPP approval and adoption in Zambia.


Threats to Science in the U.S.

NIH Budget Cuts Threaten HIV Research 

In this commentary for Think Global Health, AVAC’s Stacey Hannah and Mitchell Warren argue that ending the HIV epidemic will require sustained investment in the basic science that makes future breakthroughs possible. They warn that attacks on science and growing anti-vaccine sentiment threaten progress toward an HIV vaccine and could undermine advances across global health. “At a moment when scientific progress is advancing,” they write, “advocates, researchers, policymakers and communities should push back against politically motivated, fringe, anti-vaccine sentiments that threaten decades of investment to develop the tool that would finally break the back of the epidemic.”

AVAC Says Stop the Waste, Fraud and Abuse in the Persecution of Tony Fauci  

Former NIAID Director and longtime champion for HIV and AIDS research Dr. Anthony Fauci is facing renewed attacks from Congress, after a Senate committee voted to hold him in contempt following a hearing about the COVID-19 response. The attacks on Dr. Fauci raise alarm bells about the current state of congressional oversight, constitutional protections and attacks on science and scientists. In a letter of support for Dr. Fauci, AVAC urged the committee to recognize the deep history of partnership that Dr. Fauci has forged with the HIV/AIDS community; one that has resulted in numerous biomedical innovations and programs that have ultimately saved millions of lives.


Podcasts

Let’s Talk About PrEP: The Future of HIV Prevention with Mitchell Warren 

In this new podcast, Mitchell Warren joined Global Black Gay Men Connect (GBGMC) to talk about the future of HIV prevention and what it takes to turn scientific innovation into impact. As Mitchell puts it, “the future of HIV prevention isn’t just about groundbreaking science; it’s about making sure that science reaches the communities who need it most.”

The Future of PrEP: LEN and the Fight for Access 

Mitchell also joined ITPC’s Make Medicines Affordable podcast to discuss the future of PrEP. While LEN is a transformative option for HIV prevention that is being rolled out with unprecedented speed, Warren discusses why scientific progress means nothing without fierce political will, stronger, resilient health systems and true equity for low- and middle-income countries.

The State of HIV Prevention: Big News, Big Moves: Reflections from AIDS 2026 in Rio de Janeiro, Brazil 

By Grace Kumwenda, AVAC Regional Program Manager: Research Engagement 

AIDS 2026 in Rio was extraordinary.

Big science across HIV prevention, treatment and cure headlined from podiums; in side rooms, we had difficult conversations around greater access to available products; and throughout, ongoing tensions played out over the future of the AIDS response and the role of the US Government. And—if you are like me—there was also a lot of trying to understand some very complicated vaccine and broadly neutralizing antibody (bNAb) science and immediately asking: What does this actually mean for people and the People’s Research Agenda? What does it mean for the field and the future? Simply put, Rio did not disappoint.

Big treatment news

A first-in-class once-weekly oral combination of islatravir plus lenacapavir achieved viral suppression as effectively as daily oral antiretroviral therapy (ART) at week 48 in the ISLEND trial, another exciting indication of where longer-acting and less frequent HIV treatment is headed. We also heard important data on long-acting treatment for adolescents. In the LATA study, injectable cabotegravir (CAB) and rilpivirine administered every eight weeks performed better than daily oral tenofovir disoproxil, lamivudine, dolutegravir (TLD) at 96 weeks, and the overwhelming majority of adolescents said they found injections easier than daily oral pills. That matters because long-acting treatment cannot only be designed for adults who already navigate health systems better than youth; adolescents and others who struggle with daily adherence also need to be part of this innovation story.

Then came the bNAbs 

The CAPRISA 012C results readout was a powerful reminder that science does not always move in a straight line. A prevention trial evaluating two bNAbs together—CAP256-V2LS plus VRC07-523LS— administered subcutaneously every six months was reported to be safe but did not reduce overall HIV incidence. Unexpectedly high levels of viral resistance seen in the trial population raised important questions for the field, including whether it is time to pivot away from research on bNAbs for prevention.

It was disappointing that two bNAbs together did do any better than a single bNAb in Antibody-Mediated Prevention (AMP) studies a couple of years. These findings raise important questions about whether and how a combination bNAb approach can work for HIV prevention, as well as the implications for vaccine, treatment and cure research. In treatment and cure research, the bNAb story is more nuanced and, frankly, fascinating. Studies including RIO and FRESH are suggesting that bNAbs may be able to do something ART does not: in a small proportion of participants, immune control may persist even after the antibodies themselves have washed out of the body. There were also promising signals in children. In Botswana, two bNAbs kept 44 percent of children in the Tatelo study undetectable at six months after stopping ART, while early results from the ongoing Tatelo+ study using three bNAbs showed all participants remaining undetectable at week 24. But this is also where we have to manage expectations. The science is exciting, but effects are still seen in relatively small subsets of people, while resistance and incomplete HIV strain coverage remain challenges, strain sensitivity testing is complex and costly, and we still need much more evidence about who benefits and why. That is exactly why continued research matters.

Vaccine science is getting more precise 

HIV vaccine science continues to make important—if sometimes complicated—progress. The challenge has not changed: HIV is extraordinarily diverse, it mutates rapidly and it has evolved sophisticated ways of escaping the immune system. But what has changed is the precision with which scientists are now trying to solve that problem. Instead of simply asking whether a vaccine candidate produces an immune response, researchers are increasingly asking: Can we deliberately guide the immune system, step-by-step, toward producing the exact bNAbs needed to recognize many different HIV strains? Several studies presented in Rio focused on doing exactly that.

Researchers are refining sequential vaccination, where one vaccine primes very rare B cells and subsequent vaccinations guide those cells through stages of maturation toward bNAbs. Work presented on coaxing the creation of V3 glycan-targeting antibodies showed that carefully designed vaccine sequences can steer antibody responses away from non-neutralizing pathways and toward potentially protective ones. Other approaches are trying to generate antibodies against several vulnerable sites on the HIV envelope at once. That may ultimately be critical because an effective vaccine is unlikely to rely on one antibody class alone. Scientists are increasingly exploring how to induce bNAbs targeting two or three different vulnerable sites, potentially making it harder for HIV to escape.

Grace advocates for the pursuit of a preventive HIV vaccine at the AVAC HIV Cure and Prevention Research Networking Zone

New vaccine platforms are also opening possibilities. An mRNA approach designed to express HIV envelope trimers produced neutralizing antibody responses in rhesus macaques and protected a proportion of animals from SHIV challenge. None of this means an HIV vaccine is around the corner. But it does mean that vaccine development is becoming increasingly deliberate. Scientists are not simply hoping the immune system will produce the right antibodies. They are learning how to engineer and guide the immune response toward them. And despite highly effective PrEP, the case for a vaccine remains strong. PrEP only works when people can access it, choose it and use it.

A vaccine could eventually reach people who face barriers to ongoing PrEP use, people who do not perceive themselves to be at risk and communities where sustaining repeated prevention visits remains difficult and/or expensive.

So yes—we still need a vaccine.

And the MPT pipeline is getting interesting 

The multipurpose prevention technology (MPT) pipeline is another space that caught my attention at the HIV Prevention pre-conference in Rio. A removable injectable depot combining CAB with the contraceptive medroxyprogesterone acetate studied for three- and six-month durations in macaques provided complete suppression of ovulation through six months, with return to fertility shortly after depot removal and a relatively short CAB tail. And in another study, a 3D-printed, 90-day intravaginal ring containing islatravir, ethinyl estradiol and etonogestrel provided protection across 12 weekly HIV exposures in macaques. If we can develop products that respond to several needs at once—and importantly, products people actually want to use—that could be transformative. But again, the key phrase is want to use. A scientifically brilliant product that does not fit into people’s lives will struggle to achieve population-level impact.

Innovation in ARV-based prevention is moving 

Grace advocates for the pursuit of a preventive HIV vaccine at the AVAC HIV Cure and Prevention Research Networking Zone

We are all watching closely the efficacy program for the once-monthly oral PrEP candidate now named alimatravir (AMI). What caught my attention was not only the science, but also how Merck/MSD, the developers, are thinking about the product in people’s lives: a small, discreet tablet that could potentially be delivered beyond traditional clinics, including through pharmacies, community settings and other entry points.

Access is already part of the conversation even as alimatravir is still more than a year out from phase 3 study results. MSD announced an initial access plan that includes voluntary licensing arrangements intended to support future generic production. That matters. Access cannot be a conversation we begin after approval; it needs to sit alongside product development from the beginning. And, to be fair, the access conversations around both LEN and AMI were some of the biggest—and at times hardest—conversations in Rio. Questions around pricing, licensing, manufacturing, financing speed to scale, and equity in access were not answered. But they are exactly the conversations we need to be having now, not later. Science is moving quickly, and access planning has to move one step ahead.

Rio also provided encouraging implementation data on existing long-acting prevention options. In the PURPOSE 1 open-label extension, 95% of eligible participants chose twice-yearly lenacapavir (LEN) for PrEP, with no HIV acquisitions during follow-up and 96% injection adherence. PURPOSE 2 also reported very low HIV incidence, while real-world CAB studies continued to show strong effectiveness even as questions around late injections, testing and delivery remain important. The pipeline continues to widen, with early data on 90-day dapivirine-levonorgestrel vaginal rings adding to the range of longer-acting and MPT options under development. All this data adds another dimension to an increasingly diverse prevention pipeline—one that is more responsive to people’s different prevention and reproductive health needs.

PEP also needs its own innovation moment 

And if we are talking about innovation in PrEP, then we also have to talk about post-exposure prophylaxis—PEP. PEP is one of our oldest biomedical HIV prevention interventions, yet it can still feel like the mis-placed or forgotten tool in the prevention box. We heard several times in Rio that PEP is a race against time: it needs to be started as quickly as possible after a potential exposure. But accessing it can still mean travelling to a facility, explaining what happened, navigating stigma, finding a provider who understands PEP and then completing a 28-day regimen. That hardly sounds like an intervention designed for success.

Amidst the ongoing normalization of long-acting PrEP, AIDS 2026 addressed the implications of long-acting ARVs for PEP. But how do we generate strong evidence for new and potentially better PEP products when traditional efficacy trials may be extremely difficult—or even unethical—to conduct? Researchers are now exploring innovative approaches, including zero-event trial designs, that could help us build credible evidence without relying on HIV incidence as an endpoint or traditional trial models.

But just as with PrEP, product innovation alone will not be enough. Policy and delivery have to move to address the gaps we have today. During an AVAC side meeting, we discussed the need to simplify national PEP guidelines, address gaps across different types of exposure, support differentiated service delivery, strengthen provider information and rethink how we communicate about PEP. One point from that discussion stayed with me: we celebrate someone choosing PrEP as responsible self-care, yet someone seeking PEP can still be met with judgement—as though needing PEP means they did something wrong.

That has to change.

Seeking PEP is also an act of responsibility and self-care. If we want people to use it quickly, we need to make PEP easier to find, easier to understand and easier to use—and we need the next generation of PEP products and delivery models to reflect the urgency of the moment in which people need them.

And then there is community 

Grace provides a community perspective at the session “From Community to Innovation to Scale”

If the Global Village was the heart of AIDS 2026, then community remains the heartbeat of the HIV response and the “why” behind the HIV prevention pipeline. I had the opportunity to share community perspectives during a symposium on moving from community to innovation to scale, and one thing stayed with me: we still too often imagine innovation as a straight line from basic science to clinical trials, regulatory approval, implementation and then community.

Trials such as EXPrESSIVE and PURPOSE have reshaped that line, and we need to keep pushing. Community should be there from the moment we define the unmet need, through research priorities and trial design, to access, affordability, implementation and the final question that matters most: is this intervention actually working in people’s lives? And as prevention science becomes more complex, community engagement cannot simply mean inviting advocates into technical rooms; it also means investing in the knowledge and tools that allow communities to ask difficult questions and influence decisions. That is one reason I remain so passionate about initiatives like AVAC’s Clinical Trial Design Academy.

I left Rio thinking that perhaps the biggest shift is not only in the big news about what products are being developed and evaluated in the HIV prevention pipeline. The questions need to change.

For years, the biggest question in HIV prevention was: Can we develop highly effective tools to prevent HIV? Today, we increasingly know that we can. We have daily oral PrEP, two injectable PrEP products, the dapivirine ring, condoms, circumcision, and, hopefully, in the near future a monthly oral pill, with even longer-acting products anticipated in the near future. The harder questions now are: Can people get them? Can they actually choose between them – when and where and from whom they want them? Can countries afford them? Can health systems deliver them? And are we building the systems today that will be ready for the products coming tomorrow? That is where the big moves become important.

The big move we need NOW is from innovation to impact. That means moving from products to programs at scale; clinics to community-centered delivery platforms; product-focused interventions to choice-based prevention; and scientific breakthroughs to political courage, financing, solidarity and accountability.

The science is moving. “The science delivered beyond our wildest dreams,” said Dr. Raphy Landovitz in a moving plenary session.

Now everything around the science needs to move just as boldly. We need resources, moral compass, political will and government-owned prevention programs to move the science to people.

From Rio to the People’s Research Agenda: What next? 

So where does all of this leave us? For me, Rio reinforced that the People’s Research Agenda has to keep pushing the field on whether the science will actually matter in people’s lives. 

  • HIV vaccines: keep investing—but design for the real world now. We still need an HIV vaccine, and we need to stay the course. But as scientists refine sequential immunization and increasingly precise vaccine approaches, the field must also ask early what a future vaccine regimen would look like in people’s lives: how many doses, over what period, for whom, at what cost and how it could realistically be delivered at scale. 
  • MPTs: start with people’s lives, not just what science can combine. We need to develop MPTs around the lives and priorities of the people who will use them. The research question cannot only be: what products can we technically combine? It must also be: what combinations, durations and delivery forms do people actually want—and what gives them meaningful choice and control? 
  • ARV-based prevention: match the speed of innovation with the speed of access. Affordability, licensing, manufacturing, financing, country readiness and delivery must be planned alongside product development, not after approval. At the same time, implementation research must tell us how long-acting products work in the real world, including persistence, late injections, switching and what it truly takes to deliver genuine choice. 
  • PEP: give PEP the innovation and urgency it deserves. PEP needs a new research, product and delivery agenda. We need shorter, simpler and more forgiving regimens; innovative trial designs that can generate credible evidence; and delivery models that get PEP to people within hours, not after they have navigated multiple barriers in the health system. And perhaps just as importantly, we need to reposition PEP as what it is: an act of self-care and responsibility.