Following Aspen Pharmacare’s announcement that it will not be manufacturing the lenacapavir HIV prevention injection and will instead focus on producing alimatravir, Spotlight explores the reasoning behind Aspen’s decision and assesses what it all means for local pharmaceutical production. The article features infographics produced by AVAC, tracking PrEP price comparisons and alimatravir clinical trials.
Is Aspen betting on the right HIV prevention product?
Avac Event
Combo bNAbs for HIV Prevention – Latest Developments

Broadly neutralizing antibodies (bNAbs) remain at the center of research toward an HIV vaccine and immune-based HIV prevention. In particular, researchers are advancing the concept of “combo AMP” – passive delivery of a combination of bNAbs targeting multiple sites on the viral envelope – achieving broader and stronger protection than with a single bNAb, as in the original AMP trial.
At AIDS 2026, the CAPRISA team from Durban, South Africa announced results from the CAP 012c Phase 2 trial examining a combination of two bNAbs, which unfortunately showed no statistically significant difference in HIV incidence rates between the combo bNAb and placebo arms.
The HIV Vaccine Trials Network (HVTN) is currently designing a three bNAb combination study. Additional bNAb research is tracked as part of AVAC’s People’s Research Agenda.
In this webinar, we shared the latest updates on the bNAb pipeline and discussed what the future holds.
All things alimatravir (AMI)
Alimatravir (AMI, known as MK-8527) is an investigational monthly pill being studied for PrEP in the EXPrESSIVE program. The addition of a monthly PrEP pill, if proven safe and effective in the EXPrESSIVE trials, will expand the number of prevention options and open the door to new and innovative delivery models.
AVAC and partners have been engaging with Merck/MSD since the very start of the Alimatravir product development program and helped conceptualize the EXPrESSIVE efficacy trial design. Building on this foundation of community-centricity, advocates can now push for AMI to be rolled out with speed, scale and equity. Since 2012, each successive PrEP introduction has gone faster than the previous one, yet the time to market and to public health impact for PrEP remains too slow. Read on for AVAC’s insights on AMI, from accelerated licensing and affordability to community priorities and meaningful engagement.
The Latest on AMI
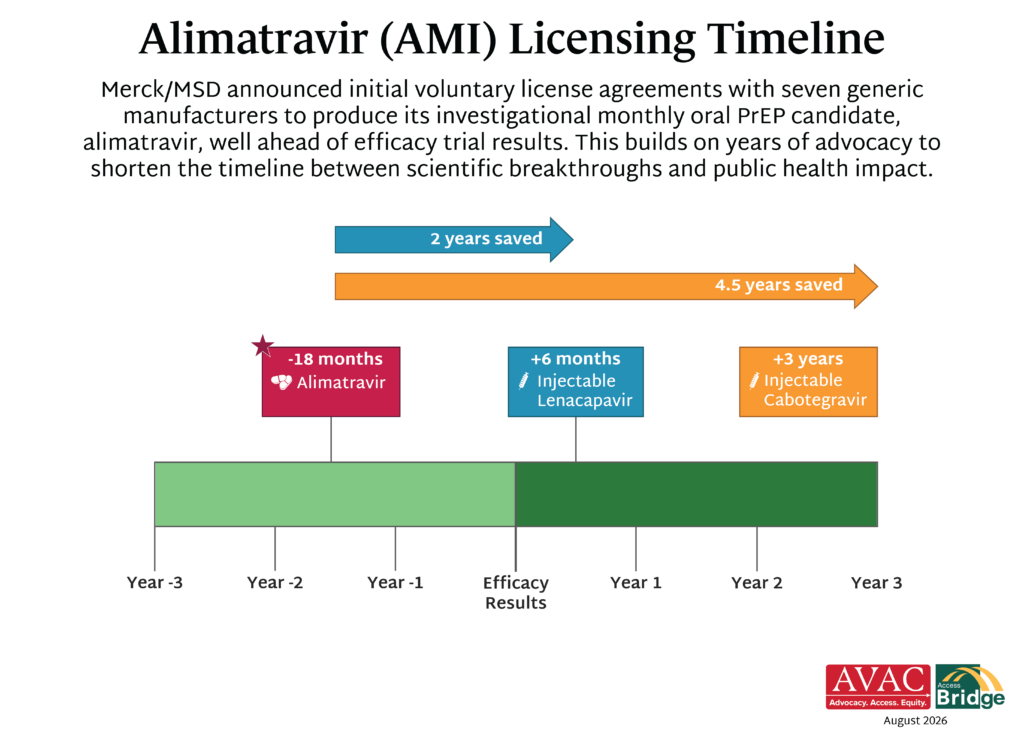
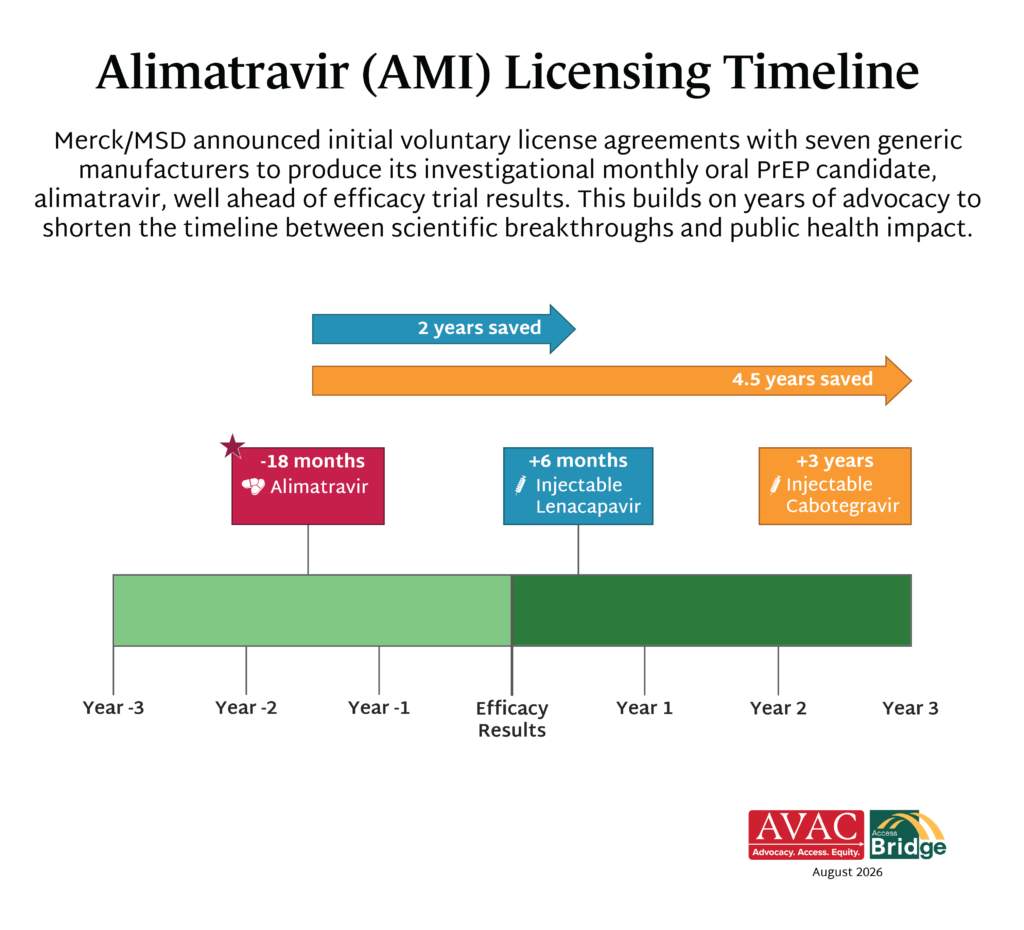
Just before the AIDS 2026 conference in July, AMI developer Merck/MSD granted seven direct licenses to generic manufacturers to produce and market the drug in 129 low- and middle-income countries, including all of Africa and much of Asia, while the trials are still enrolling. These agreements are in place 18 months before a possible efficacy result, and substantially earlier than for lenacapavir or cabotegravir. If AMI is found safe and effective, these agreements could greatly accelerate the introduction process. AVAC and Access Bridge welcomed the announcement, highlighting the challenges that remain to ensure future access is equitable and widespread among the populations that need it most.
While overall good news, several countries that are hosting the EXPrESSIVE 11 trial are left out of the voluntary license territory, reflecting a broader trend of ;excluding Latin American countries and some Asian countries from voluntary licenses. Merck/MSD did subsequently sign a memorandum of understanding with Fiocruz, a Brazilian manufacturer, to supply AMI for Brazil and the region, but the terms, timing and next steps remain unclear. Furthermore, key populations in high-income countries also face access disparities.
Find all the latest updates on AVAC’s alimatravir page.
PxWire Explores AMI Generic Licensing Agreements
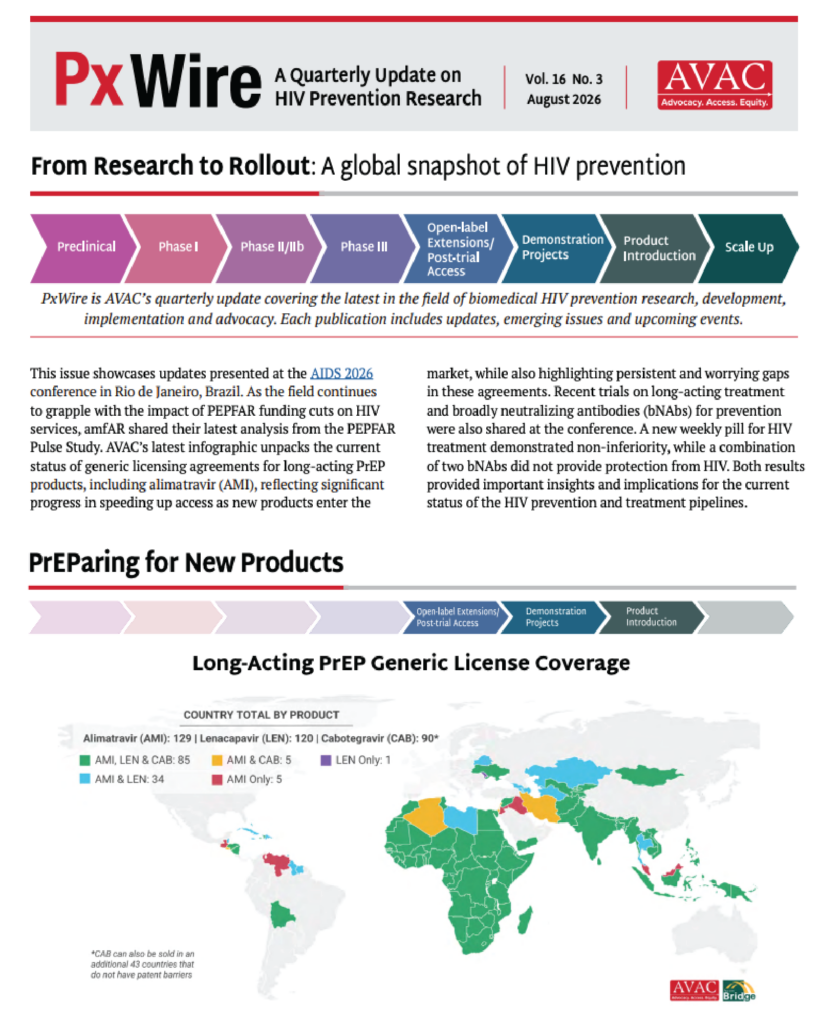
AVAC’s latest edition of PxWire features an analysis of generic licensing for AMI and what it means for the field, and an explainer on generic licensing agreements and current coverage across long-acting prevention products. The explainer examines the promise of generics for advancing affordable, equitable access and raises questions about the persistent and worrying gaps in these agreements.
Read the latest edition of PxWire.
AMI Could Be the Cheapest HIV Prevention Option Yet, But Does Affordable Mean Accessible?

Photo credit: aidsmap
A new academic analysis presented at AIDS 2026 suggests that AMI could be manufactured at large scale by generic companies and sold for as low as $3 per person per year, and a separate New York Times report highlighted estimates that generic AMI could be sold to national health systems for as little as $5 per person per year. But an affordable product is only impactful if people can access it. As the Gates Foundation’s Max Lataillade said in an AVAC satellite session at AIDS 2026, “Innovation without global access or implementation does not create the impact that we want. Science creates the possibility, collaboration creates the impact, but communities create the future.”
Read AVAC’s coverage of the AMI modeling data presented at AIDS2026.
From Research to Access: Community Statement from the Global Community Advisory Group (GCAG) on the Future of Alimatravir for HIV Prevention

Following Merck/MSD’s generic licensing announcement for AMI, the EXPrESSIVE-10 Global Community Advisory Group (GCAG) released a statement on community perspectives and priorities around prevention choice, meaningful community engagement, equitable access and ensuring that communities have a voice as research progresses toward potential introduction. As the GCAG writes, “The test is now whether early planning can translate into faster, more equitable action. An access plan is valuable not because it is announced, but because it creates a pathway that can be tracked, challenged, and delivered.”
Read the EXPrESSIVE-10 GCAG statement.
Putting Communities at the Center of EXPrESSIVE

The EXPrESSIVE program includes two phase 3 efficacy trials studying AMI for HIV prevention—EXPrESSIVE-10 among cisgender women and EXPrESSIVE-11 among cisgender men who have sex with men, transgender men, transgender women and gender non-binary individuals. The trials are anticipated to have results in the latter half of 2027. With support from the Gates Foundation, AVAC is supporting strong, consistent community engagement across the program. As a part of this work, AVAC partnered with community-based organizations in Argentina, Brazil, Kenya, Peru, the Philippines, South Africa, Thailand and Vietnam to develop educational materials for EXPrESSIVE-11 through a participatory human-centered design (HCD) process. Luciana Kamel, the Community Education Team Lead for HIV studies at Fiocruz, AVAC’s partner in Brazil for this work, described how this approach changed what was possible: “The trust, openness and respect for our work with the community made it possible to move beyond simply producing recruitment materials and instead build something that reflected the people and contexts the study was intended to engage.”
Learn more about community-led design in EXPrESSIVE-11.
Check out all the communications materials here.
Additional AMI Resources
- Video: AVAC’s Recap of AMI from AIDS 2026
- Blog: Grace Kumwenda’s AIDS 2026 Reflections, including on AMI
- Press Release: AVAC and Access Bridge Applaud Monthly PrEP Pill Access Announcement; Call for Speed, Scale and Equity in Future Monthly Oral Alimatravir Introduction
- Podcast: PxPulse – Next Up: A monthly pill for PrEP?
- Article: Merck’s alimatravir licensing deal receives mixed response
- Past analyses of real-time lessons learned about PrEP introductions: Getting PrEP Rollout Right This Time and Getting Rollout Right: Lessons from Oral PrEP.
Global Health Watch: NIH-DoD Deal & NIAID Restructuring, Ebola Vaccine Progress, Gavi Funding Resumes, New US Foreign Aid Leadership
Issue 85
The US National Institutes of Health (NIH) signs a 10-year agreement that could move significant NIAID research funding to the Department of Defense, as NIAID separately proposes a major restructuring of its clinical research infrastructure. CEPI advances efforts toward a Bundibugyo Ebola vaccine amid funding gaps, while US funding for Gavi resumes and medical groups step in on vaccine guidance. And new leadership at the Department of State brings further change to the US foreign assistance system.
NIAID Funding and Research Infrastructure Uncertain
The US National Institutes of Health (NIH) signed a 10-year agreement with the US Department of Defense (DoD) to allow the transfer of NIH funds to DoD for projects that would “support the advanced development of medical countermeasures against pandemic influenza, chemical, biological, radiological, and nuclear (CBRN) threats, and emerging infectious diseases.” Funding will come out of the NIH’s National Institute of Allergy and Infectious Diseases (NIAID) budget and has the potential to shift hundreds of millions of NIAID-funded research into the military biodefense program. According to an NIH spokesperson interviewed by Nature, “This partnership will only take place on a project-by-project basis, and all research will be within the scope of NIH’s mission. There is no blanket transfer of funds.” Nature reports that NIAID is identifying projects that could move under the arrangement, while congressional Democrats have raised concerns that the agreement could give DoD access to money Congress appropriated for biomedical research at NIH. The agreement was signed last month but went largely under the radar until this week, when Representative Rosa DeLauro (D-CT) – ranking chair of House Appropriations – raised the issue during a hearing.
The agreement comes as NIAID is also proposing a significant restructuring of its clinical research infrastructure. Under a reorganization announced in late August, NIAID would do away with its Division of Clinical Research (DCR), which helps facilitate and coordinate NIAID research programs in the US and internationally, and redistribute clinical operations and oversight across other parts of the Institute. The proposal follows months of delays in renewal notices for NIAID’s HIV clinical trial networks and Centers for AIDS Research (CFARs), raising concerns about the future of the research networks and infrastructure that has supported major advances in HIV, TB and other infectious diseases.
IMPLICATIONS: While the NIH-DoD agreement is supposedly designed to support biomedical countermeasure research, there is substantial discretion over which projects move and how the money is ultimately used. If this agreement shifts infectious-disease research away from NIAID, it risks fragmenting an infrastructure built around peer review, scientific expertise, clinical research networks and long-term public-health priorities. The fact that this agreement was unilaterally executed by the Administration a month ago, without public knowledge or Congressional notification, points to a strong need for policymaker oversight of this process to ensure that Congressionally-appropriated biomedical research funding for NIAID is used for its intended scientific purposes and that changes to the Institute do not undermine or diminish the research capacity and leadership that was built over decades through bipartisan support.
These concerns extend beyond individual grants and institutions. A March Health Affairs analysis highlights how decades of US investment in international HIV research have generated scientific advances and research capacity that also benefit Americans—underscoring that global HIV research infrastructure is not separate from US health and scientific leadership. And a recent Think Global Health analysis of the Administration’s proposed budget cuts at NIH highlights the threaten to essential HIV research.
IDSA and HIVMA have separately warned that NIAID’s research infrastructure is already being destabilized by delayed renewals and a proposed restructuring of its clinical research program. Beyond an initial chart posted to the NIAID’s website, very little detail has been shared on the proposed reorganization, as advocates are monitoring for additional insight to be revealed on the restructuring in an uncharacteristically short deadline for public comment from September 9-18.
READ:
- Revealed: inside the US military’s plan to tap huge sums from the NIH—Nature
- Why International Research Is Vital To The NIH’s Scientific Mission—Health Affairs
- The Benefits To Americans Of US-Supported International HIV Research—Health Affairs
- NIH Budget Cuts Threaten HIV Research—Think Global Health
- Stand Up for Science Demands Congress Stop Transfer of National Institutes of Health Research Funds to Department of War—Stand Up for Science
- Threats to infectious diseases research leave our country at significant risk—IDSA
- Lawmakers criticize deal that would send NIH funds to Department of Defense—CIDRAP
- Docs Alarmed by NIH Plan to Redirect Medical Research $$ to Pentagon—MedPage Today
- Democrats Condemn NIH-DOD Research Agreement—Inside Higher Ed
- Outrage greets NIH pact that could funnel biodefense research funds to Pentagon—Science
- Defense Officials Attempt to Raid NIH Funds to Cover Department of Defense Activities—Appropriations Committee Democrats
Vaccines Depend on More than Science
Nearly 100 days into the Bundibugyo Ebola response, there is still no approved vaccine, and the Coalition for Epidemic Preparedness Innovations (CEPI) says another $128 million is needed to prevent delays in later-stage trials of vaccine candidates. But CEPI also points to the response as evidence of how investments made before an outbreak can accelerate vaccine development: six pre-positioned research and response networks were activated within three days; three vaccine developers received funding within two weeks; and two experimental vaccines entered Phase 1 trials within 11 weeks. (There are now at least five vaccine candidates in clinical trials.) The experience underscores that rapid vaccine development depends on scientific breakthroughs and on sustained investment in the research networks, financing, partnerships and infrastructure needed to move quickly when a crisis emerges. Meanwhile, the US Administration announced it will release $600 million in Congressionally-appropriated funding for Gavi after more than a year of uncertainty, saying Gavi had committed to transitioning away from vaccines containing the preservative thimerosal—even though Gavi was already moving toward newer vaccines for broader public health benefits.
And in the US, leading medical organizations issued their own recommendations for COVID-19, flu and RSV vaccines as litigation over federal vaccine policy has disrupted the usual Centers for Disease Control and Prevention (CDC) recommendation process.
IMPLICATIONS: The speed of the Bundibugyo response was possible because research networks, manufacturing partnerships, regulatory preparation and vaccine platforms were established before the outbreak, but financing gaps could still slow the next stage. At the same time, the Gavi funding dispute and US medical societies stepping in to provide independent vaccine guidance demonstrate how political interference and instability in public health institutions can affect financing, recommendations, trust and ultimately access. Rapid scientific progress requires sustained investment in the institutions, expertise, partnerships and infrastructure that make it possible long before a crisis begins.
READ:
- Medical Groups Issue Guidance on Covid, Flu and R.S.V. Shots—New York Times
- Gavi’s vaccine transition was never about RFK’s fixation on mercury—Devex
- Can the world really develop a vaccine in 100 days?—Devex
New Leadership for US Foreign Assistance
This week, Dr. Becky Bunnell, Principal Deputy Assistant Secretary of State for PEPFAR – and a distinguished HIV research and program leader for decades – announced her intention to step down from PEPFAR leadership. No one individual – or organization or policy maker or politician – is responsible for PEPFAR’s tremendous success. But Becky epitomizes all that has made PEPFAR great and impactful – commitment to evidence, data and, most importantly, the individual staff, partners, participants and clients that matter. Her retirement leaves a huge void.
At the same time, Andrew Veprek is the new political appointee leading the US Department of State’s foreign assistance, humanitarian affairs and religious freedom bureau. He replaces Jeremy Lewin, who moved to lead the Department’s policy planning office. Veprek previously led the Bureau of Population, Refugees, and Migration working to align humanitarian programs with the Administration’s immigration priorities. He has criticized “forever aid” and argued that foreign assistance should have a “clear and direct connection” to US foreign policy goals.
IMPLICATIONS: These leadership changes are another important development in the ongoing restructuring of US foreign assistance, as the State Department assumes greater control over programs previously managed through USAID and global health remains one of its three principal foreign-assistance pillars. Veprek has advocated for limiting open-ended assistance, increasing contributions from other countries and more closely aligning funding with Administration priorities. For global health programs, including PEPFAR, this new leadership raises new questions about how much Congressionally-appropriated funding is ultimately released, where it flows and what conditions may be attached.
READ:
- Can the Last Person in U.S. Global Health Please Turn Off the Lights?—With & For Substack
- Cryptic Congressional Notification is Short on Details about Government-to-Government Health Grants—To End a Plague… Again Substack
- Andrew Veprek takes the helm of State Department’s foreign aid bureau—Devex
The Impact Report: Two Decades of Good Participatory Practice in HIV Research
AVAC’s new Impact Report illustrates how meaningful participation – driven by Good Participatory Practices (GPP) – strengthens both the research process and the global impact of HIV prevention innovations.
What We’re Reading
- US to Phase Out HIV Support for Namibia After Data-Sharing Impasse—Health Policy Watch
- Meet 4 people who got the HIV prevention jab—Bhekisisa
- Aspen opts not to make HIV prevention jab lenacapavir—Business Day
- ZCLDN Challenges Lenacapavir Rollout Over Exclusion of People Who Inject Drugs—Health Times
- Gilead’s price blocks UK access to groundbreaking HIV prevention tool—Just Treatment
- Once-Monthly Investigational PrEP Drug Could Be Manufactured for $3 a Year—Medscape
- “PEPFAR Is Ending.” What I Heard in South Africa.—Lights. Camera. Equity! Substack
- The Public Health Cost of Eliminating Race and Ethnicity Data—Federation of American Scientists
- Mapping the Global Health Landscape: Analysis of Fourteen International Organizations—KFF
- How Are We Doing? It’s Complicated—Global Development Interrupted Substack
- Global Order: Inside the Systems that Govern Life and Death—Center for Global Health Policy & Politics
- Gilead Sciences Just Won Its Third FDA Approval in Less Than 4 Months. Is the Stock Still Underrating This Turnaround Play?—Yahoo Finance
- UNAIDS, SADC and China, partner to advance local pharmaceutical manufacturing and health security in Southern Africa—UNAIDS
- A reflection on Rio: In search of a theme among promises for prevention—EATG
- 2026 Pipeline Report—TAG
Harnessing Artificial Intelligence for HIV: Breakthrough or Buzzword?
This presentation by Izukanji Sikazwe, Head of HIV at The Global Fund, during AIDS 2026 explores how the field might harness artificial intelligence in response to HIV. Izukanji Sikazwe unpacks what AI must be, what we must build, and the promise of AI in HIV programming.
Global Health Watch: Steinem’s Legacy, US Global Health Aid Cuts; OMB Grant Rule Delayed; Future of Global Health Reform
Issue 84
We’ve lost another champion for global health and reproductive rights this week: Gloria Steinem, the pioneering feminist and activist who spent decades fighting for gender equality, reproductive choice and the power of people to shape the decisions that affect their lives. This is a reminder to continue questioning who has a voice, who gets to decide, and why bodily autonomy is a fundamental right.
This week’s issue addresses those questions: a new analysis finds US bilateral health agreements could dramatically reduce global health funding by more than half; Congress has temporarily blocked the White House OMB’s effort to expand political control over federal grants; and, as global health architecture reform moves forward, civil society is demanding a role in shaping what comes next.
Bilateral Health Deals Could Cut US Health Aid by 59%
A new analysis from Public Citizen and Partners In Health finds that the US Administration’s bilateral (government-to-government) health agreements would drastically reduce US global health funding and foreign assistance to 18 recipient countries by 59 percent ($2 billion) by 2030 compared to pre-2025 funding. This is despite the US Congress maintaining relatively stable global health appropriations. The organizations analyzed 18 available memoranda of understanding (MoU) noting that the Administration “has kept the public in the dark about the full details of its plans for the future of US support for global health…” and “the MOUs warn of a disturbing potential underspend of congressionally appropriated global health dollars.” The agreements require countries to increase domestic health spending as US support declines. However, in 11 of the 18 countries, those domestic resource mobilization commitments would not fully replace the planned reductions in US funding.
IMPLICATIONS: The analysis raises significant questions about whether the Administration’s “America First” global health strategy toward “country ownership” and “self-reliance” is actually achievable. Instead, the analysis posits that the accelerated transition to sustainable domestic financing actually constitutes a rapid withdrawal of critical US support that these countries may not have the fiscal capacity to replace. The analysis further conveys that many of these deals contain worrisome conditionalities and performance metrics tied to funding, which may not be attainable as bilateral funding to support in-country programs are greatly diminished to begin with. The authors also exposed a disconnect between the global health funding Congress has appropriated and the substantially lower spending envisioned by the Administration under the bilateral agreements, with potential consequences for HIV, TB, malaria, Ebola and other health programs. The Department of State said it intends to spend all congressionally-appropriated global health funds, but where and how funding not included in the bilateral agreements will be spent is the outstanding question.
READ:
- Secretive deals may cut billions from U.S. global health spending, analysis shows—Washington Post
- Defunding Freedom – Impacts of U.S. Foreign Aid Cuts on LGBTIQ People Worldwide—Outright International
- Namibia Rejects US Demands For Data And Pathogen-Sharing—Health Policy Watch
- Trump’s Bilateral Agreements Reshape Global Health Funding—Public Citizen
- Trump Administration Agreements Reshape Global Health Funding—Public Citizen
US Congress Votes to Delay White House Rule Politicizing Federal Grants
Members of the US House of Representatives on both sides of the political aisle voted to pass a continuing resolution (CR) for fiscal year 2027 (FY 27) appropriations. This CR was previously approved by the Senate in early August, which authorizes government spending until December 11, delays a government shutdown on September 30 (the end of the US fiscal year), and, at least for now, delays implementation of the White House Office of Management and Budget’s (OMB) controversial proposal to give political appointees greater authority over federal grantmaking. Last month, in a stopgap spending bill released by Senate appropriators, Democrats and Republicans joined in adding a provision that would prevent the OMB rule from taking effect until at least December 11, while Congress negotiates broader government funding measures. The proposal was originally slated to go into effect on October 1, but opposition from both Democratic and Republican appropriators slowed the path forward.
IMPLICATIONS: This temporary delay is important, allowing more time for advocacy and for potential litigation to formulate. However, if implemented in December (or any time), the rule would fundamentally reshape the US research enterprise by injecting political considerations into grantmaking, weakening peer review and undermining the international collaborations that drive progress against HIV, TB, emerging infectious diseases and other global health challenges. The Senate’s actions last month and the bipartisan agreement on the CR suggest that the months of public opposition and advocacy from the advocacy and scientific community may be beginning to influence policymakers. The Senate’s intervention is one of the first signs that resistance to the OMB proposal extends beyond the scientific community and into both parties in Congress.
Evidence-based decision-making – not politics
The risk of having public health research and recommendations guided by politics as proposed by OMB is real, as evidenced by the ongoing politicization of US vaccine research and policies. To ensure Americans get credible, evidence-based recommendations that previously came from the CDC, the American Medical Association (AMA) and the Vaccine Integrity Project, which is based at the University of Minnesota’s Center for Infectious Disease Research and Policy (CIDRAP), initiated a collaborative effort to conduct a comprehensive review of evidence for vaccines of the 2026-2027 respiratory virus season. They published their findings this week in the Journal of the AMA (JAMA).
Future of Global Health Architecture
As the WHO-hosted Joint Task Force on Global Health Architecture Reform meets in person for the first time this week, the Health Architecture Reimagined (HEAR) CSO Steering Committee issued a letter urging the Task Force to put equity and meaningful community and civil society leadership at the center of reform, while also strengthening regional platforms and protecting access as financing shifts. Meanwhile, a new Council on Foreign Relations analysis of 67 health architecture reform proposals finds consensus around shifting decision-making to countries and regions, aligning donor funding with country priorities, strengthening national health systems, expanding regional roles and diversifying financing.
IMPLICATIONS: While the analysis and civil society advocacy show agreement on the direction of global health architecture reform, the outstanding question of how to get there remains. The CFR analysis highlights the key challenges around who pays versus who decides, what is gained or lost by moving from disease-specific programs to integrated health systems, and which functions belong at global versus regional levels. As these decisions are made, HEAR CSO argues that reform must be judged not only by efficiency, but by whether it advances equity, protects access and gives affected communities meaningful power. Moreover, these processes are all unfolding in the midst of leadership transitions at WHO, the Global Fund, Unitaid and the Medicines Patent Pool, amongst others.
READ:
- The Future of Global Health: Themes and Thorny Questions—Think Global Health
- Who Should Lead the Global Fund? Let the Candidates Make Their Case—Health Policy Watch
- The Future of Global Health: Themes and Thorny Questions—Think Global Health
- Kenya offers a blueprint for civil society in the ‘America First’ era—Devex
- Stand with Communities: Endorse the NGO Delegation’s Position on the Future of UNAIDS—NGO Delegation to the UNAIDS PCB
What We’re Reading
- Fauci speaks out about the pandemic, global health—and his own record—Science
- A Top Virus Scientist Stared Down Covid Lab-Leak Proponents. Now His Life’s Work Is at Stake—Bloomberg
- South Africa Grapples with the Promise and Price of Injectable Lenacapavir to Prevent HIV—Health Policy Watch
- We gave our competitors our HIV sources. Here’s why—Bhekisisa
- With over 3 600 Western Cape users, lenacapavir is “cool”—Spotlight (SA)
- Lenacapavir shot offers hope, but access is constrained—Business Day (SA)
- Threats to infectious diseases research leave our country at significant risk—IDSA
- Why I think of measles as a mini HIV—Underlying Conditions Substack
- Exclusive: Kennedy asked to remove Pennsylvania measles death from CDC tally, sources say—Reuters
- 5 years in, Ebola puts WHO’s pandemic hub to the test—Devex
- Kenya offers a blueprint for civil society in the ‘America First’ era—Devex
- Bictegravir-Lenacapavir Combo Pill Earns FDA Approval in Suppressed HIV—MedPage Today
- Defunding Freedom – Impacts of U.S. Foreign Aid Cuts on LGBTIQ People Worldwide—Outright International
- How misconceptions and woeful PR allowed Musk to shred USAID so easily—The Guardian
- The turbulent AI era is here. The choices we make now are critical.—Gates Notes
Global Health Watch: Legacies of Parton & Goosby, expiring global health funds, Jeremy Lewin’s move, Ebola funding & vaccine R&D
Issue 83
This week, the global health community lost a powerful, if unlikely, champion in Dolly Parton. She used her singing celebrity to support science and public health, including a $1 million investment that supported early research connected to Moderna’s COVID-19 vaccine. She was a supporter of literacy, marginalized communities and HIV awareness and care. Her legacy is a reminder of what it looks like to use influence to build trust in science, which couldn’t be more important today as vaccines, public health and LGBTQI+ communities are continually undermined and politicized.
Speaking of leadership, longtime leader Eric Goosby officially retired this week. Eric served as the US Global AIDS Coordinator and led the President’s Emergency Plan for AIDS Relief (PEPFAR) from 2009 to 2013 under President Barack Obama. But before he led PEPFAR and since he returned to UCSF, Eric has been a compassionate doctor, a passionate advocate, and a tireless defender of science and human rights. His colleague and mentee, mike Reid, posted this video from Eric’s retirement celebration.
Also this week, members of the US Congress demanded that the Administration release billions in congressionally-appropriated global health funding before it expires; another leadership change is underway at the Department of State, which oversees the transformation of US foreign assistance; and in the DRC, the Ebola response is making progress even as inadequate funding threatens efforts.
Congress Raises Alarm Over Expiring Global Health Funds and PEPFAR Restructuring
Democratic members of the US Congress are pressing Secretary of State Marco Rubio and OMB Director Russell Vought to release billions in congressionally-approved foreign assistance before it expires on September 30. In a new letter, they note that $7.5 billion remains unobligated, including more than $3 billion for Global Health Programs. They object to OMB’s reported decision to reserve approximately $1.35 billion in FY2025 global health funding for the closeout costs of USAID rather than health programs Congress funded. They also question plans for PEPFAR, citing the two-million decline in people reported as receiving PEPFAR-supported HIV treatment in 2025 and asking the Administration to explain how proposed reductions in CDC’s implementing role will affect treatment continuity, HIV prevention, surveillance, technical expertise and community-based programs. They are seeking answers by September 9.
IMPLICATIONS: If billions in congressionally-appropriated global health funding are allowed to expire, or used to dismantle USAID rather than support programs, the effects could exacerbate the disruptions already being documented across PEPFAR and other health programs. Additionally, reducing the CDC’s role would shift how PEPFAR is implemented, and also erode surveillance, laboratory, technical and data systems that help countries maintain HIV services and detect wider health threats.
READ:
- Scoop: $7.5B in US funding for international affairs at risk of expiring—Devex
- “A Huge Grab of Power”: Trump Is Defying Congress on Foreign Aid—ProPublica
- The Trump Administration’s Foreign Aid Review: Status of PEPFAR—KFF
- Walkinshaw, Amo, Kelly, Markey Lead 134 Colleagues in Demanding Release of More Than $3 Billion in Lifesaving Global Health Funding—Congressman James Walkinshaw
Jeremy Lewin Leaves Foreign Assistance Role
Jeremy Lewin officially stepped down as head of the US Department of State’s foreign assistance bureau and is now serving as the Department’s Director of Policy Planning. He will advise Secretary of State Marco Rubio on key foreign policy matters. An original DOGE agent at the beginning of this Administration, Lewin was one of the architects of the Administration’s overhaul of US foreign assistance following the dismantling of USAID, including the shift toward bilateral government-to-government agreements and the development of the America First Global Health Strategy. Lewin will now oversee the Bureau of Economic, Energy and Business Affairs and continue representing the US in G7 and G20 development discussions.
IMPLICATIONS: Lewin’s departure is yet another leadership transition for US foreign assistance. This happens as the State Department works to implement a redesigned aid and global health system, while being unable to obligate billions in congressionally- appropriated funding. The big question for global health now is who will lead implementation of the new foreign assistance architecture that Lewin helped design, including the bilateral agreements intended to reshape PEPFAR and other US global health programs.
READ:
DRC Ebola Response Gains Ground as Funding Gaps Threaten Progress
The Ebola Bundibugyo outbreak in the Democratic Republic of the Congo (DRC) continues to expand, with more than 560 new cases in the last week. WHO reports improvements in contact tracing and testing and issued interim guidance on prevention and control to help countries safely continue routine immunization activities during an outbreak. However, transmission remains high and funding gaps threaten the immediate response and the development of preventive vaccines. CEPI, which supports several potential Bundibugyo vaccine candidates, says it faces a shortfall of hundreds of millions of dollars for vaccine R&D, even as it launched trials this week of its fifth Bundibugyo-specific virus vaccine candidate in response to the escalating epidemic. In Uganda, the WHO officially declared its related outbreak over.
IMPLICATIONS: Resources are needed now to prevent new infections, just as sustained investment in vaccine R&D is needed to ensure future outbreaks can be minimized. As we highlighted last week, cuts to foreign assistance and weakened surveillance and response infrastructure have compounded insecurity and other challenges confronting the DRC response. And while vaccines could help prevent Bundibugyo if proven safe and effective, they cannot replace surveillance, health workers, laboratories, community engagement and health systems needed to prepare and respond.
READ:
- CEPI faces huge Ebola vaccine funding shortfall—Devex
- Ebola Outbreak May Be Three Times The Officially Reported Size—Health Policy Watch
- Ebola day 100: why this outbreak could become the deadliest in history – video explainer—The Guardian
- After 100 days of the deadliest Ebola outbreak, it can be stopped. Here’s how | Jean Kaseya and Tedros Adhanom Ghebreyesus—The Guardian
New Issue of PxWire
AVAC’s latest issue covers PEPFAR funding cuts; generic licensing of alimatravir; and the latest developments for long-acting treatment and bNAbs for prevention.
What We’re Reading
- Political bickering follows two deaths related to measles in Pennsylvania—NPR
- NIH wants to shroud peer review scores. Here’s what you can do about it.—27UNIHTED
- Comments on OMB research rule mysteriously removed from federal website—STAT
- AP report: RFK Jr. said a Samoa trip had nothing to do with vaccines. New documents refute that—PBS Newshour
- CDC Director’s Promise to ‘Speak Truth to Power’ Is the Wrong Goal—MedPage Today
- The Cost of Slow Science—With & For Substack
- The next global health architecture cannot exclude women—The Lancet
- The Next Global Health Architecture Must Deliver More Than Reform—Health Policy Watch
- It’s Been a Slow Start for Lenacapavir PrEP in the U.S.; Are We Repeating Past Mistakes?—TheBodyPro
- We have better tools to fight HIV. Can we afford them?—Explain (SA)
- Some pharmacists can now apply for permits to provide HIV prevention pills without a doctor’s script—Spotlight (SA)
- NHS England is getting a breakthrough HIV drug – but the rest of the world needs it too—The Independent
- They Don’t Want Us to Talk About Race. But It’s the Only Way We’ll End HIV—TheBody.com
- The scourge of LGBTQ criminalisation moving across African countries – and its impact on HIV—aidsmap
- COMPASS Participation at IAS 2026—COMPASS
- The turbulent AI era is here. The choices we make now are critical.—Gates Notes
Webinar
Evolving Oral PrEP Guidance for Cis Women: What do we know, and what will it take?
Join The Choice Agenda for a conversation with Heather-Marie Anne Schmidt of UNAIDS, Simon Collins of HIV i-Base, Jenell Stewart of the University of Minnesota and Raphael Landovitz of UCLA on evolving PrEP science, discordant guidelines and what it will take to advance PrEP equity for cis women, trans and non-binary people.
PxWire Volume 16, Issue 3
This issue showcases updates presented at the AIDS 2026 conference in Rio de Janeiro, Brazil. As the field continues to grapple with the impact of PEPFAR funding cuts on HIV services, amfAR shared their latest analysis from the PEPFAR Pulse Study. AVAC’s latest infographic unpacks the current status of generic licensing agreements for long-acting PrEP products, including alimatravir (AMI), reflecting significant progress in speeding up access as new products enter the market, while also highlighting persistent and worrying gaps in these agreements. Recent trials on long-acting treatment and broadly neutralizing antibodies (bNAbs) for prevention were also shared at the conference. A new weekly pill for HIV treatment demonstrated non-inferiority, while a combination of two bNAbs did not provide protection from HIV. Both results provided important insights and implications for the current status of the HIV prevention and treatment pipelines.
Read below or download a PDF version of this issue.
Progress in PrEP Uptake

Source: PEPFAR Pulse Study
- Significant challenges persist in the wake of cuts to PEPFAR programs, as the ripple effects continue to be felt across the field and organizations grapple with how to maintain services with fewer resources.
- At the start of the conference, amfAR released a report detailing the results from their recent PEPFAR Pulse study. The study provides the first concrete evidence and key details on the impact of PEPFAR cuts: surveying 166 organizations in 46 countries, they found that nearly 2,000 service sites had been forced to shutter.
- The results from the study were significant: almost no organizations were able to fill the funding gap with other donors. Services for key populations (KPs) were “decimated”: 73% of implementing partners stopped at least one KP service and 67% stopped outreach services.
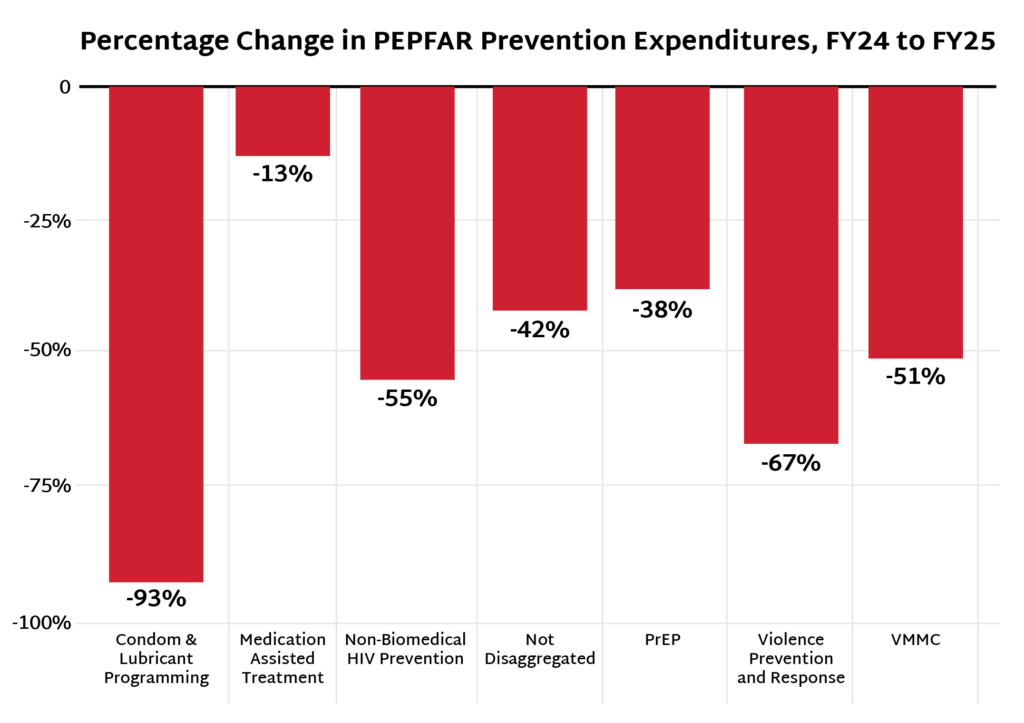
- HIV prevention services overall took a huge hit: PEPFAR expenditures for condoms and lubricants were almost completely cut, while non-biomedical HIV prevention and VMMC expenditures were cut in half and PrEP expenditures were reduced by 38%. Expenditures for associated services such as violence prevention and response were also cut by two-thirds.
- As a result, almost half of respondents reporting that they had halted key prevention activities such as condom or PrEP distribution. Two-thirds reported interruption of PMTCT and nearly one in four stopped providing prevention of mother-to-child transmission services entirely. As outlined in amfAR’s accompanying JIAS article analyzing service delivery data from PEPFAR-supported facilities, these cuts have resulted in drastic reductions in the number of people served.
- Additionally, the release of UNAIDS’ United to End AIDS special report and a companion KFF-UNAIDS analysis shared results on the global picture of the AIDS epidemic and donor funding landscape.
- The report shows HIV financing entering one of its most precarious periods in decades, with international assistance declining 18% between 2024 and 2025. Donor government funding fell by $2.1 billion in 2025—the largest annual decline since global HIV funding began scaling up—and epidemiological progress has stalled, with new HIV infections remaining essentially unchanged for the third consecutive year.
- Taken together, these findings underscore the broader challenges facing the field in effectively translating scientific progress into the impact needed to end AIDS as a public health threat by 2030.
PrEParing for New Products

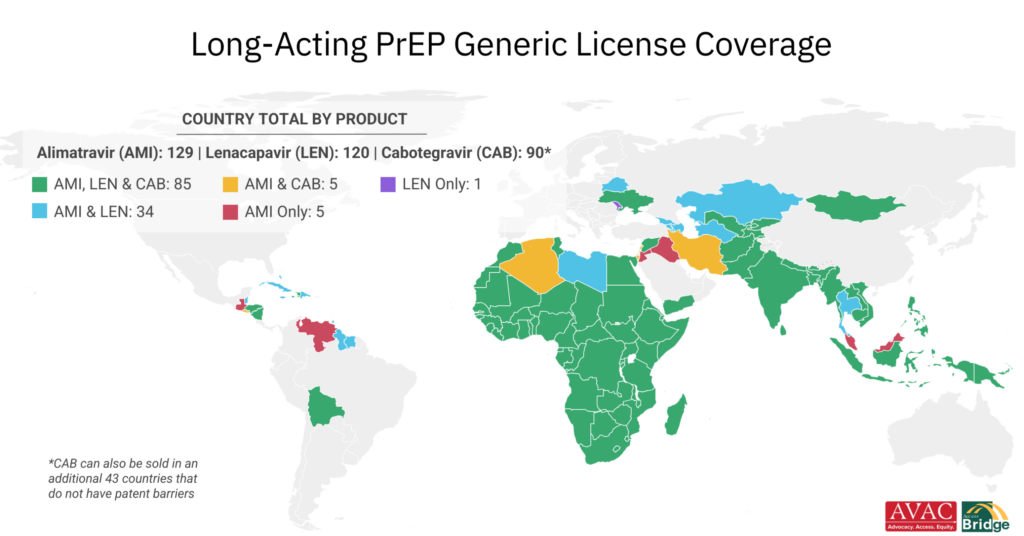
- Just before the AIDS 2026 conference, Merck/MSD announced that it had signed bilateral voluntary licenses for their investigational monthly PrEP pill, known as alimatravir (AMI, or MK-8527) with seven generic manufacturers to supply 129 low- and middle-income countries.
- Notably, the seven generic manufacturers for AMI include three based in Africa (Kenya, South Africa, and Uganda). This is an important step forward to secure local continuity of supply in high-burden countries.
- Merck/MSD’s decision to provide generic manufacturing agreements more than a year out from efficacy trial results is unprecedented. The move reflects the impact of deep engagement with advocates throughout the planning and implementation of the EXPrESSIVE clinical trial program and responsiveness to longstanding calls to accelerate the research to rollout process.
- But not all advocacy demands were met. A number of countries – including Brazil, the host country for AIDS 2026 and a site for clinical trials of AMI (and CAB and LEN, previously) – was again left out of the voluntary license territory. (Merck/MSD did subsequently announce they signed a memorandum of understanding with Fiocruz, a Brazilian manufacturer, to supply AMI for Brazil and the region, but the terms, timing and next steps remain unclear.)
- As the map above demonstrates, this reflects a broader trend of excluding Latin American countries, as well as some Asian countries, from voluntary licenses despite their participation in clinical trials for the same products, largely due to their World Bank economic categorization, and not their epidemiologic reality.
- Furthermore, these agreements do not address the access disparities in high-income countries that disproportionately impact key populations – men who have sex with men, people who use drugs, sex workers, transgender people, and others – especially in the United States where access to prevention products hinges on health insurance coverage.
- The World Trade Organization’s TRIPS Agreement does explicitly allow governments compulsory licensing under specific public health crises or anti-competitive practices. This could potentially authorize the production and use of a patented drug without the consent of Merck/MSD, but it can be a lengthy process that further delays access. An extended voluntary license to all low- and middle-income countries would allow for the quickest rollout and maximum impact.
What is Generic Licensing?
- Generic drugs are bioequivalent to originator products and are produced by a generic manufacturer. They are sold at much lower prices than the originator drug, usually because they are not manufactured in high-income countries and can make use of economies of scale.
- Generics manufacturers are allowed to sell their version of the product once the product’s patent and terms of exclusivity expire—usually after 10-20 years. However, a developer can choose to grant a voluntary license before patent expiration, allowing generics to be manufactured and marketed earlier. Original drug developers can either grant this license directly to manufacturers or via the Medicines Patent Pool.
- The developer decides which countries the license covers; normally high-income countries are excluded, as the developer will continue to sell the brand product in these markets at higher prices for a profit.
- Countries without a voluntary license to use generic versions of an originator drug may declare the drug to be in the public interest and issue a compulsory license enabling the purchase of the less expensive drug from generic manufacturers.
Time Saved on AMI Generics Licensing
- The successive introduction of each new PrEP product has gone faster than the previous one, including notable reductions in the amount of time to establish licensing agreements with generic manufacturers.
- Granting voluntary licenses while clinical trials for AMI are still enrolling, before it is known if the product is effective, sets a new benchmark for the field, potentially eliminating years of delay between evidence, licensing and generic production.
- This accelerated timeline gives the field ample opportunity to plan for broad and rapid access to AMI and should help preempt the supply constraints currently facing LEN and CAB.
- Local manufacturing in the three African countries included in the generic licensing agreement should also facilitate faster access in the region with fewer supply constraints.
The Latest R&D in the Prevention Pipeline


The latest development for long-acting treatment research
- The HIV treatment pipeline continues to evolve, especially around long-acting options. Over the past year, AVAC has added long-acting treatment (LA-ART) to our pipeline tracking efforts, reflecting the evolving continuum across ARV product development and the need for a comprehensive agenda for the development of novel and longer-acting products that includes PrEP, PEP, and treatment.
- At AIDS 2026, Merck and Gilead presented detailed results from the Phase 3 ISLEND trials, showing that an investigational weekly oral single-tablet treatment regimen combining islatravir (ISL) from Merck/MSD and lenacapavir (LEN) from Gilead sustained viral suppression as effectively as daily oral antiretroviral therapy (ART) at week 48; the studies will continue to week 96.
- Importantly, trial participants in ISLEND-2 reported strong satisfaction with the ISL/LEN treatment option and felt that it was easier to manage compared to standard HIV treatment options.
- Given the mechanisms of action of ISL and LEN, which target HIV at multiple stages of the viral life cycle, the combination regimen could offer an important, novel option for people with virologically suppressed HIV. The companies plan to file ISLEND data with regulatory authorities globally, with a potential launch in 2027.
- These Phase 3 data are an exciting indication of the evolving HIV treatment landscape, with additional long-acting options in the pipeline and oral options for people who may not prefer an injection.
Combo bNAbs get even more complicated
- Broadly neutralizing antibodies (bNAbs) remain at the center of research toward immune-based prevention. In particular, researchers are advancing the concept of “combo AMP,” i.e., passive delivery of a combination of bNAbs targeting multiple sites on the viral envelope, achieving broader and stronger protection than with a single bNAb.
- At the conference, the CAPRISA team from Durban, South Africa, announced results from the CAPRISA 012c Phase 2 trial examining a combination of two bNAbs as prevention.
- The trial, conducted with approximately 1,100 young women in South Africa and Zambia, found that a six-monthly combination of the CAP256 and VRC07 bNAbs was safe, but there was no statistically significant difference in HIV incidence rates between the bNAb and placebo arms, meaning it did not provide protection against HIV acquisition.
- One reason for the lack of efficacy was the high rate of viruses detected amongst the women who acquired HIV that were resistant to one or both of the bNAbs. This was unexpected, and one conclusion from this trial is that the evolving sensitivity of circulating viruses to the bNAbs manufactured for trials should be carefully considered.
- Antibody research has always been about more than product development. The CAPRISA 012c study continues to deepen understanding of HIV and the immune system, and will continue to inform vaccine design, cure research and the next generation of prevention strategies. But it is still not clear if bNAbs can be a prevention option on their own.
Prevention Playlist
AVAC develops a wide range of resources to inform decision making and action. Check out the latest:
Join
- Sign up for Global Health Watch: AVAC’s weekly newsletter to keep advocates informed, prepared and connected
- Sign up for AVAC’s STIWatch newsletter: a curated resource on the latest in STI vaccines, diagnostics and other prevention tools and strategies
Use
Watch/Listen
- AVAC’s AIDS 2026 video recaps
- The Choice Agenda webinar: The Persistence Paradigm: Ensuring the Longevity of Health Equity Research
- GBGMC podcast: Let’s Talk About PrEP: The Future of HIV Prevention
- ITPC podcast: The Future of PrEP: Lenacapavir & the Fight for Access
Read
- Accelerating Policy Approval and Uptake of the Dual Prevention Pill in Zambia through Early Stakeholder Engagement
- The State of HIV Prevention: Big News, Big Moves: Reflections from AIDS 2026 in Rio de Janeiro, Brazil
- A Rocky Rollout: A powerful new prevention drug could help end the HIV epidemic—but supply is falling far short
- The Future of the HIV Response: Sustaining Progress in an era of Political Uncertainty and Scientific Opportunity
Percentage Change in PEPFAR Prevention Expenditures, FY24 to FY25
This infographic, with data featured in amfAR’s PEPFAR Pulse study, examines the percentage change in PEPFAR prevention expenditures from FY24 to FY25. Significant challenges persist in the wake of cuts to PEPFAR programs, as the ripple effects continue to be felt across the field and organizations grapple with how to maintain services with fewer resources.
In The Spotlight | What are broadly neutralising antibodies and what do they mean for the fight against HIV?
Spotlight highlights research on broadly neutralising antibodies (bNAbs) and their potential role in the future of HIV treatment and prevention. As AVAC explains, “About 20 percent of people living with HIV naturally develop bNAbs, after many years. By the time bNAbs have developed in these individuals, the constantly mutating HIV has outpaced these defenders, changing too fast and too significantly for bNAbs to be effective in that individual. But that same bNAb, or a combination of them, may work in someone else.”