AVAC’s Executive Director Mitchell Warren spoke to Managed Healthcare Executive about the impact of the disruption in funding from the U.S. President’s Emergency Plan for AIDS Relief (PEPFAR). “We’re hearing about people who aren’t being tested and falling out of treatment. I think we’re beginning to see the enormity of bad decisions,” Warren said.
Mitchell Warren on the fallout from PEPFAR cuts | AIDS 2026
In ongoing trials, twice-yearly HIV prevention drug saw just one case
As lenacapavir is rolled out in 10 African countries, new findings indicate that the twice-yearly injection is highly effective for people who adhere to it. Also important: It is extremely popular. “Not only is this data reassuring for safety and efficacy, but it is a loud signal that the field needs to move with even greater speed, scale and equity in translating these results into public health impact,” AVAC Executive Director Mitchell Warren tells Devex.
The Future of the HIV Response: Sustaining Progress in an era of Political Uncertainty and Scientific Opportunity
Significant progress has been made in expanding access to HIV treatment and prevention, but major gaps in coverage and equity were further exacerbated and destabilized by changes in US government support in January 2025. This commentary by AVAC’s Executive Director Mitchell Warren examines the implications of this divergence and argues that the future of the HIV response depends less on new biomedical discoveries than on the capacity to deliver existing and emerging options sustainably and with speed, scale and equity.
Global Health Watch: Latest on White House OMB Federal Rx Grant Proposal, Global Fund Gains Stability, New Model for GH Partnerships
Issue 76
As the comment period to oppose the White House Office of Management and Budget’s (OMB) proposal to give political appointees greater authority over federal research grants closes next Monday, the Global Fund avoided new ideological restrictions on US funding even as it prepares for a new Executive Director. And new articles and analyses of US bilateral health agreements under the “America First Global Health Strategy” suggest the Administration’s vision for global health is shifting from supporting epidemic control to managing country transitions.
The Latest on the White House OMB’s Proposal Politicizing Federal Grants
The last day to submit comments opposing the OMB’s proposal to give political appointees greater authority over federal research grant decisions is Monday, July 13. The proposal has drawn major and widespread opposition from scientists, advocates, universities, associations, former government officials, the biotechnology industry and members of Congress, all calling out the weakening of a long-standing scientific peer-review process and injection of political considerations into federal funding. The proposal has already drawn more than 93,000 public comments and submissions opposing the rule. See AVAC’s submission. The US Administration aims to finalize the rule by October 1.
IMPLICATIONS: These rules, if adopted, would mandate that federally-funded science align with a politically motivated “America First” agenda aimed at dismantling decades of transformative global collaboration. These rules have the potential to dramatically reshape how federal dollars are spent and who decides, replacing evidence-based decision-making with political priorities. Notably, the published proposed rule specifically and falsely references PEPFAR as justification for increased political scrutiny of federal grants, linking HIV and global health programs to a broader debate over federal spending, oversight and executive authority. For the HIV field, these changes could affect the entire research-to-rollout continuum and global partnerships, at a time when scientific collaboration is necessary to achieving 2030 HIV targets and advancing global health equity.
TAKE ACTION: The proposed rule is still open for public comment through July 13. Click here to comment or see AVAC’s Action Alert for more instructions. Submitted comments could slow implementation of any changes to the process because the OMB must reply to them all. The outpouring of comments could also persuade Congress, which has repeatedly rejected the Administration’s previous proposals to gut research funding, to use its power to stop these changes. Comments also put into the public record that are not adequately addressed, could be raised again in lawsuits to stop the changes.
READ:
- Collins calls on OMB to rescind parts of controversial proposed grant rule—The Hill
- Defend Science Research dashboard
- Research!America Resources on OMB proposed rule
- A Proposed Rule Would Politicize Medical Research. Scientists Are Not Happy.—New York Times
- The New Trump OMB Rule: Organizations And The Public Raise Concerns—Forbes
- Trump’s federal grant overhaul plan draws strong pushback—Axios
- Trump administration pursues more durable changes to science policy after setbacks in court—STAT
Global Fund Gains Stability Amid Leadership Transition
The US government will continue funding the Global Fund without imposing its expanded global gag rule or other ideological funding conditions to US contributions. This will allow US funding to continue without restrictions related to abortion, diversity, equity and inclusion policies. At its Board meeting this week, the Global Fund also confirmed that its search for a new Executive Director will proceed as planned despite reports that the confidential nomination process might be restarted following media leaks. The Board is expected to appoint its next Executive Director in October.
IMPLICATIONS: While the decision not to impose the expanded global gag rule removes one immediate challenge, the Fund still faces significant financial uncertainty. Its next Executive Director will inherit an organization facing the major challenges of constrained resources, evolving donor expectations and increasing pressure to sustain impact in a changing global health landscape.
READ:
- Scoop: Global Fund, US agree on path around expanded gag rule—Devex
- Despite Frictions, Global Fund Asserts Confidentiality Rules and Schedule—Health Policy Watch
The New Model for US Global Health Partnerships
PEPFAR and US bilateral health agreements continue to evolve. This week, Think Global Health expanded its tracker of the US Administration’s bilateral health agreements, showing that 31 countries have now signed five-year agreements that increasingly shift financing and implementation responsibilities to national governments through co-investment and country ownership models. Andrew Green focuses on one country, South Sudan, in a Devex piece that looks at the country’s new three-year, $166 million MoU with the US, noting that while it preserves support for HIV and disease surveillance, funding may be insufficient to offset recent aid reductions and the country may struggle to meet its own financial commitments.
In a separate analysis, Jirair Ratevosian broke down what five reports from the US Department of State to Congress reveal about the Administration’s vision for global health. He writes, “Read together, these excerpts are overwhelmingly about the mechanics of transition: MOUs, implementation plans, co-investment, funding adjustments, corrective actions, benchmarks, workforce transfer, and reductions in US assistance. There is much less discussion of incidence, viral suppression, advanced disease management, prevention gaps, community systems, or epidemic control… It suggests they are no longer the organizing principle.”
IMPLICATIONS: These pieces reflect a move toward implementation of the new global health agreements. As implementation continues, we’ll be watching whether the financing assumptions, implementation systems and country commitments that are the foundation of these agreements are sufficient enough to sustain HIV and broader health gains. As Ratevosian notes, “Every Administration has its own priorities. But organizing principles matter because they determine what leaders measure, what they reward, and ultimately what they protect. When transition becomes the primary frame, there is a risk that epidemic control becomes something assumed rather than something actively managed.”
In a separate analysis, Jirair Ratevosian broke down what five reports from the US Department of State to Congress reveal about the Administration’s vision for global health. He writes, “Read together, these excerpts are overwhelmingly about the mechanics of transition: MOUs, implementation plans, co-investment, funding adjustments, corrective actions, benchmarks, workforce transfer, and reductions in US assistance. There is much less discussion of incidence, viral suppression, advanced disease management, prevention gaps, community systems, or epidemic control… It suggests they are no longer the organizing principle.”
READ:
- Tracking the “America First” Bilateral Health Agreements—Think Global Health
- Will the US funding deal rescue South Sudan’s health system?—Devex
- What Five Reports to Congress Reveal About the Future of Global Health—Lights. Camera. Equity! Substack
What We’re Reading
- The USA at 250: science in the new gilded age—The Lancet
- Africa’s vaccine sovereignty goal is set for its biggest hurdle—Semafor
- From Spider-Man to Mandela, the many influences in Professor Salim Abdool Karim’s remarkable scientific career—Spotlight
- Experimental Ebola Trials Begins in Congo as Death Toll Tops 500—Bloomberg
- The HIV prevention approach needs reprioritization, not acceleration—Devex
- RFK Jr. plans to create list of injuries caused by Covid-19 vaccines—STAT
- Don’t abolish the NIH. Fix it.—Monica Bertagnolli LinkedIn
- Africa Asserts Itself as WHO Pandemic Agreement Talks Resume—Health Policy Watch
- Lab-Leak Payback Has Begun—The Atlantic
- Faith groups urge White House to release funding for HIV/AIDS prevention—The Hill
- I fear a new HIV and Aids epidemic is coming – and the world won’t care, UN official warns—The Independent
- SAMRC and Ospedale San Raffaele Launch Phase I Trial of Long-Acting HIV Prevention Antibody—SAMRC
- Advancing the inclusion of pregnant and lactating populations in HIV PrEP research: ethical, regulatory, and surveillance recommendations from a multisectoral working group—Frontiers in Reproductive Health
Presenting at AIDS2026?
Access AVAC’s latest infographics on the research and development pipeline, prevention options, and the impact of US funding cuts.
AVAC Comment Submission on the White House OMB Proposed Federal Financial Assistance Rule
Best of AVAC’s Advocacy Guides
The AIDS 2026 conference is fast approaching. To help advocates stay informed and engaged, AVAC has curated a collection of its Advocates’ Guides covering the science, policy, implementation and advocacy conversations shaping the future of the HIV/AIDS response. Developed with partners across the field, these guides help translate complex science and policy to help inform advocacy before, during and after the conference.
For those presenting at AIDS 2026, please check out AVAC’s slide deck containing the latest infographics on the research & development pipelines, the delivery of new prevention options and the impact of US funding cuts on foreign assistance and on research and science. We will be continuously updating it, so be sure to check back for updates as the conference approaches.

The introduction of injectable lenacapavir for HIV PrEP (LEN) is underway–in some places at least. To ensure communities remain at the center of LEN rollout, this new Advocates’ Checklist for Lenacapavir for PrEP Introduction is an immediate, actionable blueprint. And read more in this blog by the co-chairs of the Civil Society Caucus of the Coalition to Accelerate Access to Long-Acting PrEP and AVAC staff.


Planning For MK-8527
Expanding prevention choice means investing in a diverse pipeline of HIV prevention options. MK-8527 is an investigational antiretroviral (ARV) once-monthly oral PrEP pill that is currently in Phase III clinical trials. If proven safe and effective, it could offer another important PrEP option. This resource provides advocates with an overview of the MK-8527, the science behind it and the latest on its clinical development.
Podcast: The Future of PrEP

AVAC’s Executive Director Mitchell Warren joined ITPC’s Make Medicines Affordable podcast to discuss the future of PrEP. While Lenacapavir is a transformative option for HIV prevention, Warren shares what it will take to ensure it reaches the people who need it most.
Download the Latest Infographics from AVAC
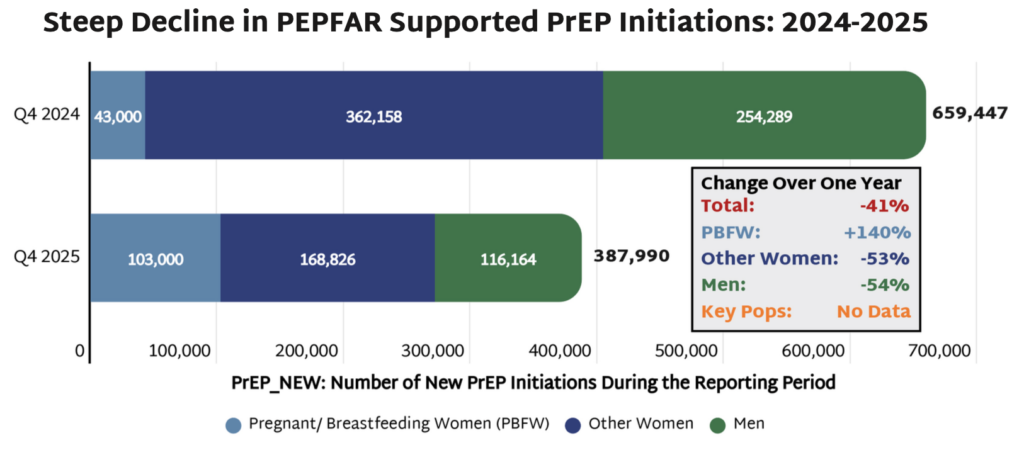
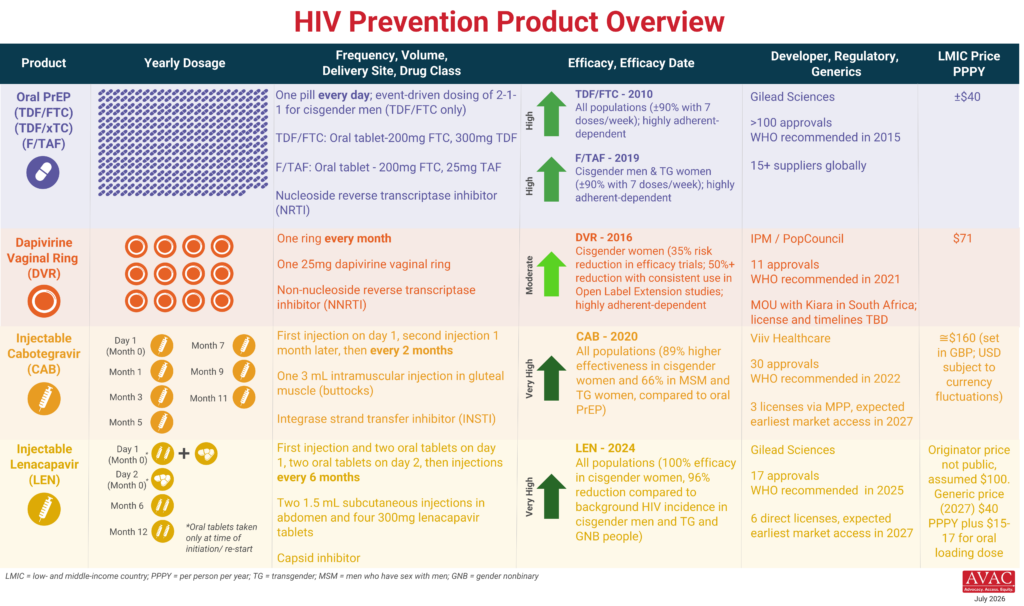
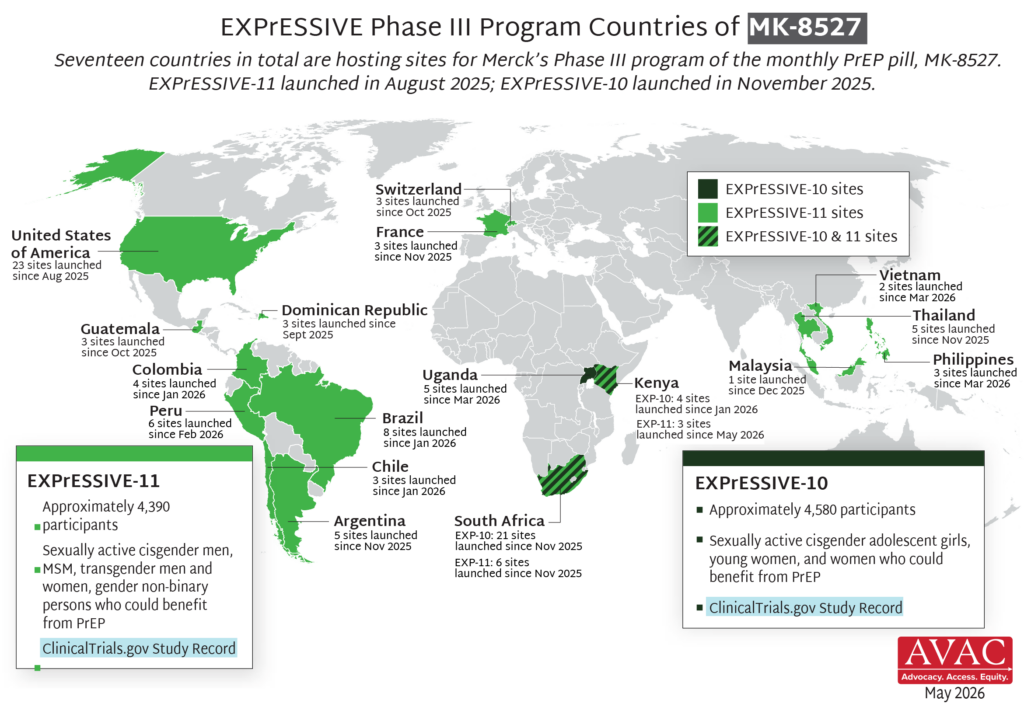
Presenting at AIDS 2026?

These graphics are updated regularly, so be sure to check back.
Additional Resources
- People’s Research Agenda: This people-centered framework guides equitable and accelerated HIV prevention research, development and product introduction. It tracks scientific progress, assesses whether investments align with community-defined priorities, and identifies critical gaps in the prevention pipeline needed to meet the diverse needs and preferences of all populations
- HIV Prevention Product Overview: The graphic provides an overview of PrEP products currently available and in late-stage clinical trials.
- Lenacapavir Resource Hub: Your one-stop resource for all things lenacapavir, this page brings together the latest news, advocacy resources, scientific updates, implementation tools and infographics to help advocates stay informed and ensure LEN rolls out with speed, scale and equity.
P.S. On Tuesday, July 14 AVAC and partners will share the impact stories of ten years of the Coalition to Accelerate and Support Prevention Research (CASPR). We hope you’ll join us.
The Future Won’t Build Itself: Sustaining the Movement CASPR Started
On Tuesday, July 14, AVAC and partners discussed the impact stories of ten years of the Coalition to Accelerate and Support Prevention Research (CASPR). Established in 2016, CASPR was funded by the United States Agency for International Development (USAID) and designed by AVAC in collaboration with leading civil society partners to influence HIV prevention research, policy and implementation.
CASPR was paused in early 2025 amidst sweeping cuts to US federal funding for foreign assistance and the dismantling of USAID. Yet the Coalition’s impact did not end there, it built an intergenerational movement that continues today.
And with attacks on global health and shrinking resources dismantling hard-won gains, the lessons from CASPR are a call for continued action: strong, community-led advocacy is indispensable to safeguard the future of HIV prevention.
Coalition members from APHA and Internews shared how they transformed HIV prevention – helping to shape ethical research practices, amplifying community leadership, influencing policy, and ensuring that the voices of those most affected by HIV help guide research and access agendas – as well as their action plan for the future.

We hope you’ll join us.
Global Health Watch: New Political Declaration on HIV/AIDS, End of US PEPFAR Support for South Africa + Treatment Declines
Issue 74
UN member states adopted a new Political Declaration on HIV/AIDS reaffirming global commitments to end AIDS by 2030, but for the first time since 2001, the declaration was not adopted by consensus – and with the US notably voting against it. At the same time, last week’s news that the US Department of State is assuming greater control over PEPFAR is followed this week by the phase-out of US PEPFAR support for South Africa and new analyses showing PEPFAR-supported HIV treatment declined in 2025, following the US Administration’s foreign aid freeze. Also, for organizations in the US, please consider signing Partners in Health’s Letter to Protect CDC PEPFAR Programs.
UN HIV Declaration Adopted Amid Deep Political Divisions
The UN General Assembly adopted a new Political Declaration on HIV/AIDS this week reaffirming global commitments to end AIDS as a public health threat by 2030. However, for the first time since political declarations on HIV began in 2001, the declaration was not adopted by consensus. And importantly, the US delegation voted against the declaration. Deputy US Representative to the UN, Tammy Bruce, said in a comment rejecting the declaration that it strayed too far from the targets for ending AIDS “by including divisive topics”. The declaration acknowledges that progress toward the 2030 goal is off track, highlighting widening funding gaps, disruptions to HIV services, and persistent barriers faced by populations at high risk of HIV. Advocates and civil society played an important role in ensuring the declaration included commitments to evidence-based, rights-based HIV responses and renewed calls for sustained investment in prevention, treatment and community-led services.
IMPLICATIONS: The divided vote underscores how geopolitical tensions and domestic politics in the US are shaping global health policy at a moment when the HIV response faces its greatest financing crisis. While the declaration provides an important political framework for countries and advocates, it carries no binding obligations and offers few concrete answers to address the growing funding shortfall as nationalism rises and development assistance falls. The US government’s opposition marks an insular, ideologically driven retreat from longstanding consensus for rights-based HIV programming, particularly for key populations who continue to bear a disproportionate burden of HIV. This is consistent with the harmful policies and positions the US Administration has taken against communities vulnerable to HIV including the Promoting Human Flourishing in Foreign Assistance (PHFFA) and the invisibility of vulnerable populations in the most recent PEPFAR data.
In response, global civil society groups led by Health GAP have elevated the People’s Declaration on HIV/AIDS as a counter to the resulting Political Declaration. Over 400 organizations signed onto the People’s Declaration, illustrating a major show of power and call for action by governments to reaffirm commitments, rights, and investments to end HIV for everyone, everywhere.
READ:
- US And Russia Vote Against UN Political Declaration On HIV/ AIDS—Health Policy Watch
- HIV political declaration proves surprisingly divisive—Devex
- United Nations High-Level Meeting on HIV/AIDS concludes with strong support for a bold political declaration for ending AIDS as a public health threat by 2030—UNAIDS
US Ending PEPFAR in South Africa
The US Administration abruptly announced its intention to end PEPFAR support in South Africa, with funding expected to terminate by early 2027. The decision is part of the Administration’s broader retrenchment from foreign assistance and is related to political disagreements with the South African government. South Africa receives more than $400 million annually through PEPFAR, which supports health workers, prevention programs and service delivery. This decision marks one of the most consequential changes to PEPFAR since its creation in 2003, with significant implications in envisioning an end to the HIV epidemic – in South Africa and globally. This news follows the Administration’s Executive Order in February 2025, which made baseless claims about South Africa, and the March 2025 decision to “hold all research awards” for South Africa after designating it a “country of concern”. At the time, AVAC told Bhekisisa, “It is very clear that the President is using budgets and terminations of previously agreed to programmes to redefine agendas… that defy science and are clearly political and ideological.”
IMPLICATIONS: The PEPFAR withdrawal from South Africa reinforces the shift away from evidence to ideology, moving from long-term global health partnerships toward a more transactional foreign policy model. These short-sighted decisions come despite the historical South Africa-USA partnership that has catalyzed scientific research and program impact for HIV prevention and treatment, where the country plays a vital role in clinical research, development of cutting-edge prevention technologies, and implementing models for treatment, care and prevention. Although South Africa finances its own antiretroviral medicines, PEPFAR supports important aspects of the health workforce, community-based prevention and services for key populations. A rapid withdrawal will disrupt testing, prevention and services, placing additional strain on the country battling the largest HIV epidemic. Furthermore, the end to PEPFAR funding along with the severance of National Institutes of Health (NIH) research partnerships, cuts off a country that is central to ending the global epidemic and one that continues to inform the science of HIV and tuberculosis treatment and prevention.
READ:
- Trump administration to end PEPFAR funding for South Africa—Semafor
- Trump administration to phase out HIV funding for South Africa—Politico
- The United States Is Ending PEPFAR in South Africa. Here’s What That Could Mean—Lights, Camera, Equity! Substack
- U.S. Plans to End AIDS Funding for South Africa—New York Times
- South African civil groups warn of dire impact as US phases out HIV program funding—Associated Press
- Top US official defends controversial global health deals—Devex
- What Johnny Figueroa’s nomination means for PEPFAR’s future—Devex
- South Africa’s TB and HIV Research at Risk: A Call to Catalyze Urgent Action by Funders—TAG
New Analysis Shows Decline in PEPFAR-Supported HIV Treatment
A new analysis published in Nature Health finds that PEPFAR-supported HIV treatment declined in 2025 following the US Administration’s foreign aid freeze, with approximately 2 million fewer people reported as receiving PEPFAR-supported antiretroviral therapy than in 2024 (a 10% decrease). Of the 26 countries examined, treatment support fell across all, though some of the decline reflects changes in how PEPFAR classifies and reports treatment support rather than patients losing access to care. South Africa was called out in the analyses, accounting for most of the treatment declines—individuals previously counted as receiving direct PEPFAR support were reclassified as benefiting from broader health system investments, resulting in a net treatment decline of about 95,000 people (1.8%). The authors conclude a “decline of ∼1.73 million individuals on direct PEPFAR-supported treatment and an increase of ∼1.64 million individuals on treatment benefitting solely from the programme’s broader support to health systems, yielding a net treatment loss of 94,881 (−1.8%)”.
IMPLICATIONS: As the authors conclude, “while the analysis cannot determine whether and to what extent declines will translate into reduced individual- or population-level treatment outcomes, a reduction in PEPFAR-supported treatment of this scale within a single fiscal year raises concerns.” The data underscore the significant disruptions caused by funding uncertainty and restructuring across the program.
READ:
Add Your Voice to Stop OMB’s Attack on American Science
Proposed new regulations by the White House Office of Management and Budget (OMB) would use budgetary and regulatory tools to bypass longstanding scientific peer-review and congressional processes, including withholding appropriated funds, restructuring federal agencies, and proposing rules that would give political appointees greater influence over research funding decisions. Public comments are due by July 13th – please consider taking action and visit Stand Up for Science’s STOP OMB portal now.
- Russell Vought’s Latest Plan to Gut the Government Should Terrify You—The Nation
- Act now: oppose a new threat to US federally funded work—The Lancet
- How The OMB Rule Could Hurt You And Your Town—Forbes
What We’re Reading
- ‘A matter of life or death’: the activists confronting Congress about slashing HIV funding—The Guardian
- Warnock, Cassidy Urge Senate Colleagues to Oppose Trump Administration Changes to CDC’s Global Disease Programs—US Senators Raphael Warnock and Bill Cassidy
- Zimbabwe Intensifies HIV Prevention Drive as Lenacapavir Gains Momentum—Herald Online
- ‘They’re in the wind’: How US cuts pushed trans people out of care—Bhekisisa
- Proposed CDC science office could tighten political control at agency—STAT
- Africa CDC chief says the continent needs to invest its own funds in Ebola response, vaccine—Associated Press
- Did Pete Hegseth single-handedly raise the R₀ of flu?—Inside Medicine
- I Served on Grant Review Panels for 12 Years. Let’s Not Romanticize NIH Peer Review.—MedPage Today
- Trump admin doubles down on Ebola strategy—Politico Pulse
- The Covid Czar People Still Trust—New York Times
- The HIV Equity Crisis: What the Data Says About Who We’re Still Failing—Contagion Live
- Clinical trial set to test two drugs for fast-growing Ebola outbreak—STAT
- We published in Nature Medicine in 2025 for free. In 2026, it cost us $12,850—STAT
Global Health Watch: Restructuring PEPFAR, Political Control Over Science; FDA + African Medicines Agency MoU
Issue 73
This week, the US Administration continues to move to consolidate control over science, restructure the systems that underpin PEPFAR and global health security, and redefine US global health engagement through regulatory influence rather than long-term public health partnerships.
Restructuring PEPFAR and Weakening the US CDC
The US Administration is moving forward with its plan to significantly reduce the US Centers for Disease Control and Prevention’s (CDC) vital role in PEPFAR and global health programs, shifting much of the authority and funding to the US Department of State, which many argue, does not have the expertise or capacity to manage the programs. In contrast to CDC’s historical role in implementing PEPFAR in-country programs, the plan would require countries to “purchase” CDC technical assistance services (ranging from disease surveillance to laboratory support) through new bilateral agreements in a “fee-for-service” public health model. The future of in-country CDC offices and technical staff is uncertain under this new plan.
The Administration already significantly weakened PEPFAR’s infrastructure by shutting down USAID last year and delaying HIV funding in an interagency transfer to CDC. This new proposal could further undermine the CDC from much of the work that helps deliver HIV services and supports disease detection around the world. As eight former CDC directors – appointed by both Republican and Democratic presidents – warned previously, the proposed restructuring could disrupt not only HIV services but also the laboratory networks, surveillance systems, trained workforce and trusted relationships with ministries of health that support outbreak detection and response worldwide.
IMPLICATIONS: “This will completely destabilize HIV work abroad,” former CDC official Michele Montandon told the New York Times. “We’ve seen service disruptions, deaths and babies born with HIV after shuttering USAID, and we can expect more to come if CDC is also shut out of this work.” The rapid restructuring of PEPFAR could decimate HIV programs, complicate the transition to country ownership, and fracture global disease surveillance and outbreak-response systems built through decades of US investment. While there is broad stakeholder agreement about the importance of increasing country ownership and transitioning away from donor dependence, the accelerated pace and structure of the proposed changes makes technical expertise and relationships precarious before sustainable alternatives are in place. These changes come at a time of a rapidly unfolding Ebola epidemic in Central Africa, complicating current crises and creating doubt in response capacity for future epidemics.
READ:
- New Plan Scales Back C.D.C.’s Work on Diseases Abroad—New York Times
- The Global Health Spending Stall is Worse than it Looks—Global Health Security Academy
- Protect PEPFAR & Protect CDC’s Global Health Work!—Action Network
- New Change to PEPFAR Will Slash CDC’s Presence Abroad—MedPage Today
- The State Department Say Foreign Countries Will Decide on US CDC Budget for Global Work—To End a Plague … Again Substack
- Congress should embrace strategic health diplomacy—STAT News
Political Control Over Science Moves Ahead
The proposed new regulations that would significantly expand political interference in federal funding decisions across all US government grants by the White House’s Office of Management and Budget (OMB) remains at the center of current controversy. In a recent New England Journal of Medicine editorial, editors warned that this Administration is increasingly using budgetary and regulatory tools to bypass longstanding scientific peer-review and congressional processes, including withholding appropriated funds, restructuring federal agencies, and proposing rules that would give political appointees greater influence over research funding decisions. At the same time, Hal Duncan, the nominee to serve as the Deputy Director of the OMB, defended the “pocket rescission” strategy during his confirmation hearings this week in front of Senate leaders. This strategy would allow the Administration to use additional spending cuts through “pocket rescissions,” which would allow funds to expire before Congress has an opportunity to act.
IMPLICATIONS: The moves by OMB signal increasing efforts to shift decision-making authority away from Congress and scientific peer review and toward the Executive Branch, giving the President more control over how federal money is spent and what research and programs get funded in alignment with ideology. For the last 18 months, the question of who gets to decide what scientific research and public health programming are funded and whether Congress’s decisions are carried out as intended continues to be raised, and the answer increasingly appears to be the White House rather than Congress or the broader scientific and public health community.
- How cuts to CDC are dismantling its capacity to protect Americans’ health—The Conversation
- Trump administration has its sights set on destroying international research collaborations—BMJ
Scientists Issue Bethesda Declaration: One Year Later
Nearly 40 former and current staff at the National Institutes of Health (NIH) authored a new report, The Bethesda Declaration One Year Later, Continuing Harms to the NIH Mission, which outlines nine deepening concerns at the NIH over the last year along with proposed solutions. This report comes one year after hundreds of NIH employees accused the Administration of politicizing biomedical research through the original Bethesda Declaration. The new report notes that the Administration is slowing medical research, disrupting international collaborations, weakening ethical safeguards, driving away experienced staff and undermining public trust in science. Approximately 24% fewer NIH research projects were funded in 2025 than in 2024 and more than 5,500 peer-reviewed grants were terminated. The report also warns that the White House’s proposed Office of Management and Budget (OMB) rule, which would subject federal grants to greater political review and require alignment with presidential priorities, would institutionalize many of the changes researchers have opposed in the last year.
IMPLICATIONS: The updated Bethesda Declaration shows growing concern from the scientific community about the politicization of science. The NIH has served as the foundation of HIV research, from supporting basic science, vaccine development, implementation of new prevention technologies and global research partnerships. As political oversight expands and international collaboration is deconstructed, the US risks undermining the scientific infrastructure that has fueled decades of innovation and partnership.
- OMB nominee ‘can’t commit’ to forgoing ‘pocket rescissions’ funding gambit this year—Politico
- The OMB and the Politicization of Science—NEJM
- House Budget Bill Threatens Public Health, Defend Public Health Says—Defend Public Health
US FDA and African Medicines Agency Enter Into New Partnership
The US Food and Drug Administration (FDA) and the African Medicines Agency (AMA) have signed a new Memorandum of Understanding (MoU) to create a shared framework for information sharing and regulatory cooperation. The agreement could allow African regulators to draw on FDA assessments and regulatory decisions when evaluating medical products, while also facilitating greater cooperation on inspections, scientific reviews and regulatory capacity building.
IMPLICATIONS: This agreement between two stringent regulatory authorities (SRAs) is another example of the Administration’s evolving approach to global health and in-line with the US government’s recent “America First” global health strategy. This partnership could be interpreted as a regulatory harmonization effort that would allow for the rapid influx of American-made health technologies for emerging markets in Africa. The expansion and procurement of US-made health commodities is a central feature to the US government’s new transactional approach to global health. However, this comes in stark contrast as the US cuts funding for global health programs, reduces the CDC’s international role and restructures PEPFAR, it is replacing long-term public health partnerships with narrower bilateral agreements focused on regulation and innovation. The disconnect between developing new health technologies and supporting the health systems needed to deliver them complicates the vision for greater regulatory cooperation between SRAs that is required for scale-up and access to the latest treatment and prevention modalities.
READ:
- African Regulators Will Share Information, Could Rely On US FDA Decisions—The Pink Sheet
- Statement of Cooperation Between the United States Food and Drug Administration and The African Medicines Agency Regarding Cooperation to Enhance Activities of Mutual Interest
A ‘perilous moment’ for the response to HIV
A new UNAIDS report released ahead of next week’s United Nations General Assembly’s High-Level Meeting on HIV/AIDS shows that external funding cuts, a strong push back on human rights and under investment and under prioritization of HIV prevention and community services are threatening to reverse years of gains in the AIDS response. Read AVAC’s UN High-Level Meeting on HIV/AIDS: What to Watch.
What We’re Reading
- HIV Response Faces ‘Biggest Storm’ in Its History After Funding Nosedive—Health Policy Watch
- Funding cuts drive sharp drop in HIV prevention, UNAIDS says—Reuters
- Inside Trump’s Reversal on HIV—Politico
- Zambian AIDS Patients Pay the Price of Dispute Over America’s Demand for Preferential Access to Minerals—The New York Sun
- HIV Prevention Is Solved. Delivering It Is Not—Forbes
- MSF pushes for affordable HIV medicine Lenacapavir—The Star (Kenya)
- The 3-Pronged Attack on Scientific Communication – Inside Higher Ed
- Game-changing HIV prevention medicine must be available for USD40 per year, everywhere—MSF
- Aid is being replaced by investment. That’s a dangerous mistake—Devex
- We published in Nature Medicine in 2025 for free. In 2026, it cost us $12,850—STAT
- NIH launches new office to advance human-based research and reduce animal use—National Institutes of Health
- Scientists Call Charges Against NIH Virologists ‘Chilling’—MedPage Today
- Kennedy Seeks to Expedite Appeal of Ruling That Blocked His Vaccine Policies—New York Times
- Scores Fall Ill at Air Force Base After Hegseth Makes Flu Vaccine Optional—New York Times
- REPORT ON ACCESS to PrEP in EUROPE, 2026—AIDS Action Europe
- Trump admin paying thousands of dollars per month to store ruined USAID contraceptives—The Hill
- ACTG Launches HIV Cure Study Evaluating Novel Approach Targeting the HIV Reservoir—POZ
- Global Fund partners with CIFF to bring new TB tests to 13 countries—Devex
- WHO launches first global database on the prevalence of sexually transmitted infections—WHO
- As a physician, I have never been more concerned about rates of congenital syphilis—STAT
- Trump Administration Global Health Agreements: Negotiations Tracker—Public Citizen
Avac Event
Inside the Decisions that Changed Global Health: An AVAC Conversation with Nicholas Enrich
On Wednesday, May 20, AVAC’s Mitchell Warren was joined by Nicholas Enrich, author of Into the Wood Chipper and former global health lead at USAID, and Rosemary Mburu, Executive Director of WACI Health, for Inside the Decisions that Changed Global Health: An AVAC Conversation with Nicholas Enrich.
During the call, Enrich shared an inside perspective on the decisions that led to the dismantling of USAID and the foreign aid freeze and what they mean for global health today.