Press Release

AVAC, Access Bridge Call for Accelerated Ambition to Reach at Least Three Million People with Lenacapavir for HIV Prevention by the End of 2027 

New, more ambitious target will accelerate impact, drive affordability, and build momentum toward ending the HIV epidemic

NEW YORK and NAIROBI, October 21, 2026 – AVAC and Access Bridge today issued a global call to action urging governments, donors, manufacturers, implementers, and advocates to work toward a bold but achievable goal: reaching at least three million people with injectable lenacapavir (LEN) for HIV prevention by the end of 2027. 

“Scientific breakthroughs only matter if they reach the people who need them,” said Mitchell Warren, Executive Director of AVAC. “LEN has the potential to transform HIV prevention and the overall epidemic response, but realizing that potential will require more urgency, more ambition, and more investment. Three million people reached by the end of 2027 is entirely feasible and an essential step toward ending new HIV infections. The field must commit to this: no less and no slower, with a push for more and faster.” 

Since results of efficacy trials were announced in 2024, injectable lenacapavir for PrEP (LEN) has generated enormous excitement. By the end of 2024, Gilead Sciences provided voluntary licenses to generic manufacturers and submitted multiple regulatory filings, and the Global Fund and PEPFAR initially committed to reach two million people over three years with LEN, and then increased it to three million in three years. As of October 2026, LEN is recommended by WHO; has 19 regulatory approvals, and counting; is being introduced in 36 implementation science projects; and is being introduced as part of public health programs in 29 countries, with support from the Global Fund and PEPFAR. 

“LEN represents one of the most promising advances in HIV prevention in decades. There is no time to waste. If we are to have any hope of ending AIDS as a public health threat by 2030, the global community must move beyond incremental implementation and seize the opportunity to rapidly scale access to a highly effective, long-acting prevention option, alongside treatment for all people living with HIV,” said Warren. 

Recent progress has demonstrated both the feasibility and demand for long-acting HIV prevention. Rapid regulatory approvals and national introduction efforts have laid the groundwork for broader access. At the same time, community demand for long-acting prevention options continues to grow, particularly among populations that face barriers to daily oral PrEP use. If stakeholders fumble the moment, demand risks outpacing supply by large margins, which will harm public trust in prevention efforts. 

The coming year represents a critical window for action. AVAC’s newly updated publication, Now What with Injectable LEN for PrEP: How to Translate Ambition into Accelerated Delivery and Impact outlines how to reach at least three million people with LEN by the end of 2027, including two potential scenarios for LEN market development, and where advocates can demand action. 

AVAC and Access Bridge have called for a LEN market development strategy that builds the market faster, secures lower product pricing, and achieves greater impact by 2030. The faster the market grows, the more transmission can be averted, more quickly the PrEP market can expand, and the greater the potential impact with LEN. This market development will also help build the programmatic infrastructure to expand choice and prepare for the possible introduction in 2028 of monthly oral alimatravir, if it is also shown to be safe and effective next year. 

“Three million people by the end of 2027 is a starting point, not an endpoint,” said Wawira Nyagah, Executive Director of Access Bridge. “We have a historic opportunity to reshape the trajectory of the HIV epidemic, and we are just getting started. The question is not whether the field can move quickly enough; it’s whether we choose to.” 

To reach at least three million people with LEN by the end of 2027 and 20 million by 2030, AVAC and Access Bridge are calling on:  

  1. Countries to provide ambitious forecasts based on actual demand and need and programmatic opportunity, not based on budget. 
 
  1. Global Fund and PEPFAR/GHSD to place orders now for enough doses for at least 2.4 million people in 2027 (given that 600,000 per years of LEN was ordered for 2026). In addition, advocacy needs to mobilize domestic resources and other new donors to increase volumes further. 
  1. National regulators to ensure rapid approval and/or regulatory waivers of generic LEN so that there are no delays in transitioning from Gilead to lower-priced generics, which should begin happening early next year, and that there is adequate and consistent access to product in-country. 
  1. Gilead and the approved generic manufacturers to commit the supplies to make this delivery schedule in 2027 and ensure commodity security.  
  1. Countries and communities to develop the programmatic infrastructure and robust demand creation to deliver that quantity as part of comprehensive prevention choice programs, so that product reaches people who need and want it and that no product is wasted. 

AVAC and Access Bridge emphasize that scaling LEN must be part of a broader commitment to prevention choice. The HIV prevention landscape is entering a new era: beyond LEN is the potential inclusion of new methods like the investigational monthly PrEP pill alimatravir (AMI), which is undergoing clinical trials now. The PrEP market from 2028 could be far more complex and competitive. 

No single product will meet everyone’s needs, but expanding access to a diverse range of prevention options is essential to ensuring that all individuals can find methods that work for them. AVAC and Access Bridge urge partners across sectors to align around a common objective now: turning the promise of LEN into measurable public health impact for millions of people around the world. 

Read the full Now What with Injectable LEN for PrEP: How to Translate Ambition into Accelerated Delivery and Impact here. 

No Time to Lose: Reaching At Least Three Million with LEN for PrEP by 2027

AVAC and Access Bridge today issued a global call to action and new publication urging governments, donors, manufacturers, implementers, and advocates to work toward a bold but achievable goal: reaching at least three million people with injectable lenacapavir (LEN) for HIV prevention by the end of 2027. This new, more ambitious target will drive affordability, build a sustainable PrEP market, and accelerate impact.

“Scientific breakthroughs only matter if they reach the people who need them. LEN has the potential to transform HIV prevention and the overall epidemic response, but realizing that potential will require more urgency, more ambition, and more investment. Three million people reached by the end of 2027 is entirely feasible and an essential step toward ending new HIV infections. The field must commit to this: no less and no slower, with a push for more and faster.”

Mitchell Warren
Executive Director, AVAC

Since results of efficacy trials were announced in 2024, injectable lenacapavir for PrEP (LEN) has generated enormous excitement. By the end of 2024, Gilead Sciences provided voluntary licenses to generic manufacturers and submitted multiple regulatory filings, and the Global Fund and PEPFAR initially committed to reach two million people over three years with LEN, and then increased it to three million in three years. As of October 2026, LEN is recommended by WHO; has 19 regulatory approvals, and counting; is being introduced in 36 implementation science projects; and is being introduced as part of public health programs in 29 countries, with support from the Global Fund and PEPFAR. 

Recent progress has demonstrated both the feasibility and demand for long-acting HIV prevention. Rapid regulatory approvals and national introduction efforts have laid the groundwork for broader access. At the same time, community demand for long-acting prevention options continues to grow, particularly among populations that face barriers to daily oral PrEP use. If stakeholders fumble the moment, demand risks outpacing supply by large margins, which will harm public trust in prevention efforts. 

The coming year represents a critical window for action. Our publication, Now What with Injectable LEN for PrEP: How to Translate Ambition into Accelerated Delivery and Impact outlines how to reach at least three million people with LEN by the end of 2027, including two potential scenarios for LEN market development, and where advocates can demand action. 

To reach at least three million people with LEN by the end of 2027 and 20 million by 2030, AVAC and Access Bridge are calling on:

  1. Countries to provide ambitious forecasts based on actual demand and need and programmatic opportunity, not based on budget.
  2. Global Fund and PEPFAR/GHSD to place orders now for enough doses for at least 2.4 million people in 2027 (given that 600,000 per years of LEN was ordered for 2026). In addition, advocacy needs to mobilize domestic resources and other new donors to increase volumes further.
  3. National regulators to ensure rapid approval and/or regulatory waivers of generic LEN so that there are no delays in transitioning from Gilead to lower-priced generics, which should begin happening early next year, and that there is adequate and consistent access to product in-country. 
  4. Gilead and the approved generic manufacturers to commit the supplies to make this delivery schedule in 2027 and ensure commodity security.
  5. Countries and communities to develop the programmatic infrastructure and robust demand creation to deliver that quantity as part of comprehensive prevention choice programs, so that product reaches people who need and want it and that no product is wasted.

“Three million people by the end of 2027 is a starting point, not an endpoint. We have a historic opportunity to reshape the trajectory of the HIV epidemic, and we are just getting started. The question is not whether the field can move quickly enough; it’s whether we choose to.”

Wawira Nyagah
Executive Director, Access Bridge

Scaling LEN must be part of a broader commitment to prevention choice. The HIV prevention landscape is entering a new era: beyond LEN is the potential inclusion of new methods like the investigational monthly PrEP pill alimatravir (AMI), which is undergoing clinical trials now. The PrEP market from 2028 could be far more complex and competitive. 

No single product will meet everyone’s needs, but expanding access to a diverse range of prevention options is essential to ensuring that all individuals can find methods that work for them. AVAC and Access Bridge urge partners across sectors to align around a common objective now: turning the promise of LEN into measurable public health impact for millions of people around the world. 

Read the full Now What with Injectable LEN for PrEP: How to Translate Ambition into Accelerated Delivery and Impact here. 

From Research to Access: The Community Statement from the Global Community Advisory Group (GCAG) on the Future of Alima (Alimatravir) for HIV Prevention

The EXPrESSIVE-10 Global Community Advisory Group (GCAG) released a statement on the future of alimatravir and HIV prevention. The statement reflects community perspectives and priorities around prevention choice, meaningful community engagement, equitable access, and ensuring that communities have a voice as research progresses toward potential introduction. As the GCAG writes, “The test is now whether early planning can translate into faster, more equitable action. An access plan is valuable not because it is announced, but because it creates a pathway that can be tracked, challenged, and delivered.”

SA and Zambia’s HIV shot dilemma: Demand versus supply

Early data shows South Africa and Zambia have high demand for lenacapavir (LEN), the twice-yearly HIV prevention injection. But clinics don’t yet have enough doses for everyone who wants it. In Bhekisisa, AVAC’s Executive Director Mitchell Warren weighs in on the excitement surrounding LEN and what a successful rollout will require.

Anxiety in Paradise: Highlights From the 26th International AIDS Conference in Rio de Janeiro

Following AIDS 2026 in Rio de Janeiro, TheBody reflected on the stark disparities on display. “There were all of these tensions there,” AVAC’s Executive Director Mitchell Warren said. “Between the amazing science and the difficult political and economic time we’re in. Between the opportunity of new, long-acting prevention tools and the fact that we were in a region of the world where access to them doesn’t exist. And between what could be and what currently is.”

Merck’s alimatravir licensing deal receives mixed response

In July, Merck announced licensing agreements with seven manufacturers for generic production of its HIV drug alimatravir, though access and equity concerns remain. As AVAC’s Executive Director Mitchell Warren explained, AVAC hopes to see Merck pledge to reach at least 2 million people with alimatravir within the first year of product launch and 5 million within the first 2 years, and guarantee it will be available in LMICs within 3 months of first approval. “These targets are a bare minimum and entirely feasible. We need this to jump-start the scale of the market, drive down prices and, most importantly, deliver impact”, Warren said.

Aids is no longer exceptional. What happens now?

Following AIDS 2026, Bhekisisa’s Mia Malan reflects on the annual conference that took place amid an unprecedented funding crisis and the dwindling political will to address HIV. As AVAC Executive Director Mitchell Warren said, “What comes out of a conference [or movement] is more important than what happened at the conference. Three to six months from now, we need to ask: are we working differently because we gathered in Rio? …I hope the answer will be clear: coming together and planning together strengthened our Aids response. That’s the measure of success.”

The Second Injection

In her Substack, Skye Grove unpacks the distance that still lies between products and services and the people who need them. Reflecting on AIDS 2026 conversations and sessions, she shares insights from AVAC’s Executive Director Mitchell Warren, Access Bridge’s Executive Director Wawira Nyagah, and AVAC partners like Yvette Raphael and Adaobi Lisa Olisa.

Accelerating policy approval and uptake of the dual prevention pill in Zambia through early stakeholder engagement

The Dual Prevention Pill (DPP), a combination of PrEP and combined oral contraception (COC), offers a novel, female-controlled option for HIV and unintended pregnancy prevention. However, new technologies like the DPP often face delays in regulatory approval and uptake due to limited stakeholder involvement early in the introduction process. This article in AIDS Care, authored by AVAC Fellow Rhoda Msiska, AVAC staff members Kate Segal and Cindra Feuer, and Newton Donkola, demonstrates how early, multisectoral stakeholder engagement could accelerate DPP approval and adoption in Zambia.

Read the article.

Beyond AIDS 2026: AVAC’s Top 10

Our team compiled a list of AVAC’s top 10 takeaways from AIDS 2026. These topics sparked discussions and ideas among our team and AVAC’s larger partner network, and will carry our work well into the future. 

1. The implications of US government cuts 

The implications of the US administration’s efforts to dismantle its longstanding role as the global leader in the HIV response are coming into focus – and it’s not a pretty picture. 

Credit: amFAR

First, amfAR released a report providing the first concrete detail on the impact of PEPFAR cuts: surveying 166 organizations in 46 countries, they found that nearly 2,000 service sites had been forced to shutter.

Almost no organizations were able to fill the funding gap with other donors. Services for key populations (KPs) were “decimated”: among implementing partners, 73% stopped at least one KP service and 67% stopped outreach services.

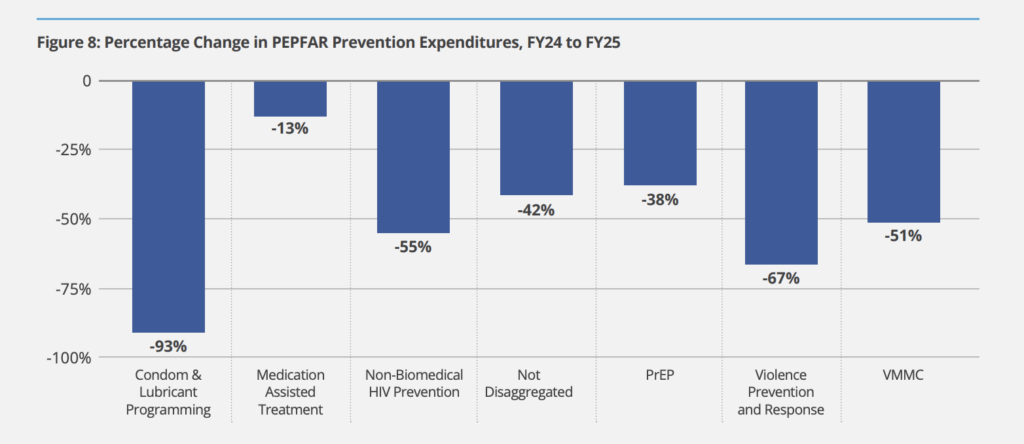
Prevention overall took a huge hit: almost half of respondents stopped activities like condom or PrEP distribution. Two-thirds reported interruption of PMTCT and nearly one in four stopped providing prevention of mother-to-child transmission services entirely. As AVAC’s Navita Jain told POZ, when foreign aid funding was frozen, “We were in year eight of a 10-year project, really getting momentum going and accelerating prevention research, and the cuts had a massive effect, with no guidance provided or a plan for a way forward.”  

As widely reported, first by former AVACer Emily Bass, and then by most major media outlets, a US State Department official displayed a mislabeled map of African countries, with African government officials in the room. As Jirair Ratevosian said, the map “should never have made it onto the screen, especially during a presentation about partnerships with African governments,” but more importantly, it’s a disappointment “that this mistake became one of the conference’s biggest media stories. Because AIDS 2026 produced important science, serious policy analysis and real progress on issues ranging from PrEP delivery to global aid transitions.”  

2. Prevention innovation includes speed, scale and equity…

One of the most exciting developments arrived days before the conference, when Merck/MSD announced seven direct licenses to generic manufacturers to produce their investigational monthly pill for HIV prevention, known as alimatravir, while Phase 3 clinical trials are still enrolling.

The announcement reflects responsiveness to advocates’ longstanding calls to accelerate access to PrEP options, and deep engagement with advocates throughout the clinical trial program. Since 2012, each successive PrEP introduction has gone faster than the previous one, yet the time to market and to public health impact remains too slow.

Granting licensing agreements to generic manufacturers while clinical trials are still enrolling, before it is known if the product is effective, should significantly reduce the time to market for the product. The current timeline gives the field ample opportunity to work with ministries of health, donors, communities, and Merck to plan for broad access to the monthly PrEP pill, which lends itself to innovative delivery models – from pharmacies to community-based distribution approaches.

3. …but too often, Latin America is still left behind  

It is cruel irony that Brazil was host country to the conference, a key site for clinical trials of cabotegravir, lenacapavir and alimatravir, but has been left out of voluntary licenses for all three products.

While Merck/MSD shared information about a memorandum of understanding with Fiocruz to manufacture alimatravir for the region, the timing and next steps remain unclear: “Now is the time to plan for even speedier and wider access if alimatravir works,” said Access Bridge Executive Director Wawira Nyagah. “This must include pricing transparency from Merck and their generic licensees, accelerated investments by donors to design and implement integrated programs that offer the monthly pill as part of choice of product and service delivery models that actually reach people who need it, everywhere. This should be based on public health imperatives; not on World Bank country classifications or geographical location. Anywhere the HIV epidemic is increasing must be included, full stop.”

4. Innovative delivery and community involvement are expanding access… 

AIDS 2026 showcased exciting models for HIV prevention service delivery that are removing barriers to access, reducing stigma and burden on healthcare systems. In São Paulo, vending machines delivering HIV tests, PrEP and PEP are available in subways, normalizing widespread access to HIV prevention.

Sri Lanka and the Ukraine have introduced mobile PrEP delivery programs, and in Kenya and South Africa, pharmacy delivery is reducing the load on health clinics following the drastic cuts to PEPFAR service delivery programs. The recently launched SCALE-IT project in Zambia is implementing a model for community-based delivery of PrEP options, including injectable PrEP, with more information expected soon. As we look ahead to alimatravir, the potential for a monthly PrEP pill opens the door to innovative delivery models. While alimatravir trials are still enrolling, AVAC has called on the stakeholders to ensure models are well-conceived and planned, adequately funded, and set up for success. With this timeline in hand, there’s no excuse for getting it wrong.

5. …but supply issues pose a serious threat to LEN rollout. 

From countries across the globe, the same message echoed across AIDS 2026: there is demand for LEN now and the current supply is not enough. While recent commitments from PEPFAR and the Global Fund are encouraging, demand is rapidly outpacing supply across the globe – and there is an urgent need from donors to address bottlenecks and place more orders.

Access Bridge’s Nyagah reinforced this point: “People are being offered products that fit their lives, but the systems are not growing fast enough to supply it.” If supply issues are not urgently addressed, the field risks losing the demand, community trust, and current progress in LEN uptake that we have collectively worked so hard to achieve. For more on this topic, Jon Cohen’s recent piece in Science provides a deep dive into the challenges facing LEN rollout in South Africa and Zambia amidst the current political and funding landscape.

6. The urgency of vaccines: advancing the science, deepening our understanding  

At a plenary session, Sandhya Vasan described why a vaccine is still needed, even with expanded PrEP options like lenacapavir, echoing AVAC’s recent commentary on the scientific challenges and emerging insights in the vaccine field and what’s in the research pipeline. Vasan highlighted long-standing partnerships with communities as foundational to vaccine research and vaccine confidence, as well as the need for continued investment and support for upstream vaccine research.

Community engagement was on full display at the HIV Cure & Prevention Research Networking Zone, where one of the best-attended sessions was the People’s Research Agenda Think Tank on HIV vaccines. AVAC’s resources on preventive vaccines and bNabs explain the science behind vaccine research.

In addition, the CAPRISA team announced results from the CAPRISA 012c Phase 2 trial examining a potential combination of two broadly neutralizing antibodies (bNAbs) as prevention. The trial found that a six-monthly combination of the CAP256 and VRC07 bNAbs was safe but did not provide protection against HIV acquisition in young women in South Africa and Zambia. As AVAC Executive Director Mitchell Warren noted, “We had hoped that combining two bNAbs in this study would provide greater protection than a single antibody, but sadly it did not.” Antibody research has always been about more than product development – research shared at the conference continues to deepen the understanding of HIV and the immune system and will continue to inform the next generation of vaccine and cure strategies. 

7. Cure took another step forward 

Two case presentations at the conference shared two more patients with HIV and cancer were cured following stem cell transplants for cancer treatment.

As AVAC’s senior program manager for HIV cure, Jessica Salzwedel says, “Thirteen people have now been cured via stem cell transplant. Every cure is an exciting step forward, but we must stay focused on the inequity of all 13 of these occurring in high-income countries – and ensure that our work expands access to cure information, research opportunities, and solutions.” 

Cure strategies must go well beyond the science: efforts must include confronting the stigma of HIV and expanding research advocacy and engagement, especially in Africa.  At pre-conference and conference sessions, along with a session at the HIV Cure & Prevention Research Networking Zone, attendees explored promising elements of the “kick and kill” strategy, gene editing technologies, the role of broadly neutralizing antibodies in “control” strategies, and how community members can get more involved.  

8. Harnessing the power of AI for HIV while centering communities in the response

Many sessions explored the promise of AI to strengthen design and delivery of HIV programs, while highlighting potential pitfalls if we neglect to prioritize transparent regulatory frameworks and partnership with communities in the design, use, and oversight of AI systems.

ITPC Executive Director and AVAC Board member Solange Baptiste noted the urgency of approaches to AI that are human-centered: “We need a community governance layer built into the AI ecosystem…one that ensures communities help shape priorities, oversee the implementation, identify harms and hold systems accountable throughout the AI lifecycle.” The final plenary of the conference for the first time included a presentation on AI by Global Fund’s Izukanji Sikazwe, highlighting the dangers when the right innovations fail to scale and balancing the concept of AI as a partner with the risks AI can bring. For more insights from AVAC on the evolving discussions around AI, check out our quarterly AI and HIV Newsletter and Advocates Guide to AI and HIV Programs.

9. Partnerships power the HIV response by advancing community-centered priorities 

As the field faces devastating funding cuts, strong partnerships between national, regional and global advocates are more important than ever. AVAC’s partnerships underpinned so much of the critical work discussed at AIDS 2026: to ensure key populations are not left behind, to advance community-led monitoring and community-based delivery, and translate choice into impact.

In each case, success was made possible by bringing together diverse stakeholders with the singular goal of developing innovative, community-centered approaches to the HIV response. As AVAC’s Warren reflected following the conference, “Communities are the leaders of AIDS programming. All over the conference they led plenaries, symposia, abstracts. These are not recipients, they are leaders who are driving the conversations.”

10. Communities are the heart of the AIDS response, and the Global Village is the heart of the AIDS conference.  

In conversations, meet-ups, and protests coordinated across the Global Village, the power of advocates and coalition-based advocacy was a key theme of the conference. AVAC’s HIV Cure and Prevention Research Networking Zone brought delegates, researchers, advocates, and community members together for interactive discussions, expert-led sessions and networking conversations.

The Zone featured the “HIV Funding Saves Lives” quilt created by COMPASS and the Global Advocacy Data Hub to convey the impact of funding cuts on communities. Attendees signed the quilt, adding their voices to the demands for HIV funding to be restored. As advocates look ahead, connections built at the Networking Zone will strengthen for future coalition-based advocacy.