AIDS 2026: Rising Above to Meet the Moment 

The World Must Act with Speed, Scale and Equity

By Mitchell Warren, Executive Director, AVAC 

One of the most memorable moments for me at AIDS 2026 wasn’t a scientific presentation. It wasn’t a late-breaking abstract, or a standing-room-only session. It was a conversation with a ministry of health official from one of the first countries preparing to introduce lenacapavir (LEN) for HIV prevention. We weren’t discussing whether people wanted the product. We weren’t debating whether it worked. We were talking about running out.

Countries preparing for rollout of this groundbreaking prevention method – one that provides near-perfect protection from infection – are already worried they won’t have enough supply to meet demand.

For decades, the HIV field has worried about generating demand for prevention. At AIDS 2026 in Rio, we confronted a very different challenge: the demand is building. The question now is whether the world is prepared to meet it.

This was a conference defined by something arguably more important than any single scientific breakthrough. It was the recognition that as a field, we must confront the pressing challenge of political will and moral decision-making. As Raphy Landovitz asked in a stirring plenary session: do we have the courage, partnerships, and urgency to fight for science, which remains under attack?

After this week in Rio, I believe we absolutely have the courage, and the conference theme – Rethink. Rebuild. Rise. – provides a roadmap for how we turn it into impact.

Slides presented at AIDS 2026 by AVAC partner Access Bridge during a session on the promise of long-acting PrEP

First, we must rethink what success looks like. For years, success in HIV prevention meant developing new products to prevent new infections. Today, though, success means ensuring people can actually get the option that best meets their needs – how do we deliver this extraordinary range of options?

The range of HIV prevention options has grown in ways we only dreamed of a decade ago: beyond condoms which remain as essential today as they were at my first AIDS conference 30 years ago, we now have injectable PrEP which provides near-perfect protection in clinical trials and is becoming more widely available; a vaginal ring that provides a unique female-initiated option; and a monthly oral PrEP pill is in late-stage trials (and accelerated access planning).

But more options do not automatically mean more choice. Choice is not simply a shelf full of medicines. Choice is a health system capable of delivering them. It is procurement systems that can purchase multiple options instead of one. It is healthcare workers trained to welcome diverse individuals and counsel people without bias, rather than steering everyone toward the same intervention or the one the health provider thinks is best for them. It is financing that rewards access instead of rationing it.

In Rio, I heard government representatives, implementers, and community advocates ask operational questions about choice that would have sounded impossible just a few years ago. How do we effectively forecast demand and introduce multiple long-acting options? How can we ensure speed, scale and equity across environments, from rural clinics to urban hospitals? How can we simplify delivery and offer PrEP where people want it, and not just where systems want them?

We must think big. In a matter of months, a once-in-a-generation opportunity will present itself as generic lenacapavir becomes available, and this highly effective prevention option, hopefully, becomes more accessible. Governments, donors, manufacturers, and global procurement agencies should be planning for millions of people—not thousands—to access long-acting PrEP. Importantly, we also heard in Rio how the new interest in LEN is actually motivating people who had not come forward to test and are found to already be living with HIV. The novelty of LEN is becoming a catalyst for universally testing and connecting all people with the products and services they need – whether or not they are living with HIV.

The HIV response has always moved fastest when those most affected have shaped research questions, demanded accountability, challenged institutions, and insisted that innovation reach the people who need it most.

As countries begin introducing long-acting prevention, community leadership becomes even more important. Communities that trust delivery systems, prevention methods and messages are much more likely to accept new methods. And ultimately, it will be communities that tell us whether products are truly accessible, whether health systems are delivering meaningful choice, and whether equity is more than just a conference slogan.

The “HIV Funding Saves Lives” quilt, created by COMPASS and the Global Advocacy Data Hub to convey the impact of funding cuts on communities

Second, we must rebuild. Rio was also the first global AIDS conference that had data presentations about the impacts of the dismantling of USAID and the dramatic restructuring of U.S. foreign assistance.

Since then, prevention programs have been diminished, services for key populations have been interrupted, research has been halted, partnerships have been strained. Organizations have closed their doors. Communities are feeling those consequences every day. Jerop Limo, an AVAC advocacy partner and adolescent HIV programming expert, summed it up perfectly in the recent POZ piece on the impact of funding cuts, “People are disengaging from healthcare spaces and missing appointments. This is not the system we had, the one that was working.”

The release of UNAIDS’ United to End AIDS special report and a companion KFF-UNAIDS analysis show the challenge of translating scientific progress into the impact needed to end AIDS as a public health threat by 2030. The report shows HIV financing entering one of its most precarious periods in decades, with international assistance declining 18% between 2024 and 2025. Donor government funding fell by $2.1 billion in 2025—the largest annual decline since global HIV funding began scaling up. This is not just a warning. It’s not just a ‘cautious stabilization of where things are. It is an alarm bell that we have to change how we do what we do, and how we fund what we do, if we want to succeed.

As colleagues from Duke and Friends of the Global Fight underscore, rebuilding cannot mean returning to the systems that existed before.

We can’t go back, but we also can’t stay still. We have to build something new.

The good news is that new opportunities and promising signs are emerging. Countries are assuming greater ownership of their HIV responses. Regional institutions are stepping forward. New partnerships are forming, and new institutions are stepping up to lead.

Across conversations in Rio, there was broad consensus that sustainability of the HIV response cannot remain overly reliant on any one country government and the whims of its leadership. A broad coalition of countries, communities, philanthropy, industry, and global institutions working toward shared goals must equally share responsibility for the future of the HIV response.

In fact, hosting the conference in Brazil was a powerful reminder that political commitment to universal HIV services can achieve a lot. But even Brazil cannot introduce every new prevention technology without strong partnerships. Manufacturers must be willing to expand access, multilateral organizations must be willing to commit to volume guarantees and investments that meet demand, and donors must prioritize and be willing to invest in what’s required to ensure equitable rollout.

Raphy Landovitz’s plenary highlighted the critical choices the field has ahead of us to ensure we meet this moment.

Lastly, we must rise to meet this moment. After every setback, whether political or scientific, the global HIV community has found a way to turn adversity into action, setbacks into solidarity, and uncertainty into progress. That was on display more than ever in Rio, where we were reminded that disappointment also moves science forward.

One of the week’s significant scientific presentations came from the CAPRISA antibody study. The results were disappointing: the trial found that a six-monthly combination of two broadly neutralizing antibodies (bNAbs) was safe but did not provide protection against HIV acquisition in young women in South Africa and Zambia. Researchers concluded that while the antibody combination demonstrated strong potency in laboratory studies, it did not achieve antibody levels needed for protection in people.

With this study, we had hoped that combining two bNAbs would provide greater protection than a single antibody, but sadly it did not. But antibody research has always been about more than product development. The CAPRISA 012c study continues to deepen our understanding of HIV and the immune system, and will continue to inform vaccine design, cure research and the next generation of prevention strategies.

Every carefully conducted study answers important questions. Every unexpected result helps redirect investments toward more promising approaches. That is how scientific progress works.

AIDS 2026 convened at a pivotal time: we now have just four years until 2030—the deadline for global HIV targets and the Sustainable Development Goals.

By the end of this year, we should know whether long-acting PrEP is reaching people at scale. By the International AIDS Society conference in Geneva next July, we should know whether generic lenacapavir is expanding access, whether research investments are holding, whether community-led programs have been restored, and whether countries are closing the equity gap. If those indicators are moving in the wrong direction, we must change course in real-time.

The legacy of Rio will be determined by whether we seize this extraordinary moment. Even as we rethink and rebuild things, we must ensure that we center communities, follow their lead, and rise up to support the populations that need this work more than ever. And just like a well-conducted clinical trial, a conference should answer some questions and raise new ones:

Will donors and governments purchase enough lenacapavir to meet demand instead of limiting access? Will pharmaceutical companies accelerate voluntary licensing and affordable pricing so new innovations reach everyone, everywhere without years of delay? Will donors invest boldly enough to match the science? Will countries protect community-led organizations and programs for key populations, recognizing that these are not optional additions but essential pillars of an effective response? Will researchers continue pushing the boundaries of vaccines, antibodies, cures, and long-acting treatment, even when some studies disappoint?

The science has never been stronger, communities have never been more ready, and the need has never been more urgent. Rio reminded us that ending HIV is no longer limited by what we know, it is limited only by the courage to act.
Potential Lenacapavir Supply, 2026-28

Lenacapavir has the potential to reach millions — and the momentum is building. Using the current oral PrEP market as a baseline, this graphic estimates what demand for LEN could look like through 2028 and shows how current donor commitments stack up against that opportunity.

PxWire Volume 16, Issue 2

This issue showcases AVAC’s analysis of the recent PEPFAR data release, assessing how uptake of prevention programs—particularly PrEP initiations—have declined over the last year. As the field grapples with the lasting impact of the US government’s cuts to PEPFAR programs, AVAC takes a closer look at what the data show and what is still missing.

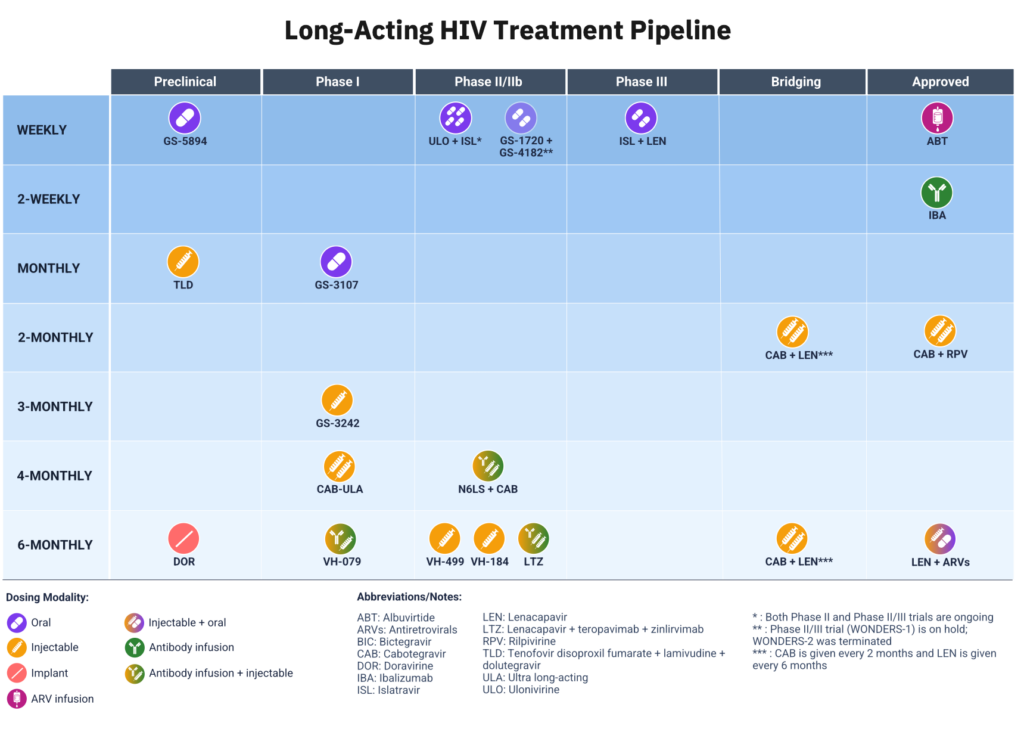
This is especially timely, given the recent announcement from PEPFAR and the Global Fund of their additional commitment to scale-up lenacapavir (LEN) for PrEP. AVAC’s recent infographic unpacks the enduring gap between current donor commitments, LEN volume capacity and potential market size. Lastly, AVAC’s newest infographic depicts the long-acting HIV treatment R&D pipeline. Coupled with research on long-acting prevention and vaccines, long-acting treatment is an important component of an integrated approach to ending HIV as a global health threat.

Read below or download a PDF version of this issue.

Progress in PrEP Uptake

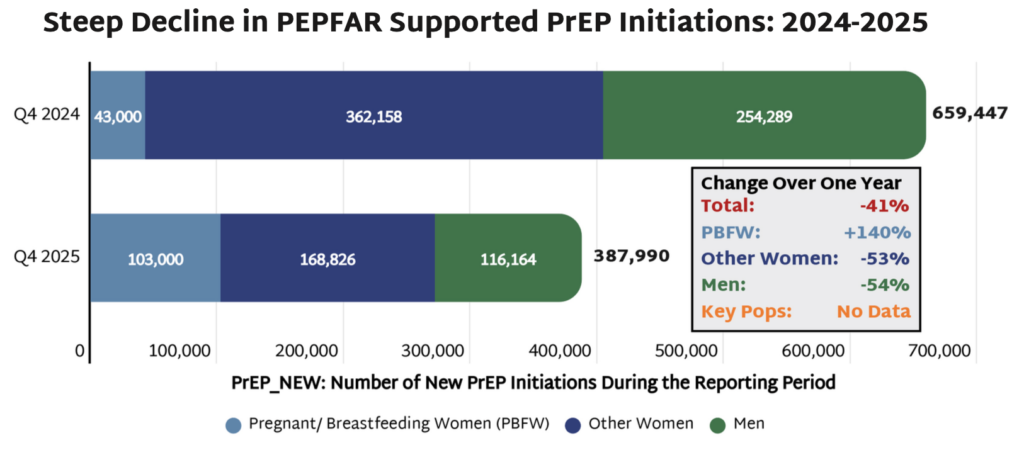
  • On April 17, the US State Department released long-awaited PEPFAR data from the last quarter of Fiscal Year 2025 (FY25), representing the only data available on the status of PEPFAR programs following the US government’s drastic cuts to foreign assistance programs. Only one quarter of data, covering the fourth quarter of FY25 (July-September 2025) was released, and no data are available from the last six months of implementation.
  • While PEPFAR promoted the data release as reflecting significant progress in curbing the epidemic, the data actually reveal stark declines in HIV testing, diagnosis, and treatment. HIV prevention programs were some of the hardest hit by both cuts to PEPFAR programs and the narrowing focus on prevention for pregnant and breastfeeding women (PBFW).
  • In FY25, the number of individuals newly initiated on PrEP decreased by 41% as compared to the same quarter in FY24, with an overall decrease of 54% among all men and 53% among women who are not pregnant or breastfeeding. While PEPFAR touted a 140% increase in PrEP initiation among PBFW, the disaggregated data is historically inconsistent and not available in the latest data release; therefore it cannot be independently verified.
  • Especially worrying was PrEP initiations among adolescent girls and young women (AGYW) aged 15-24, which fell by 39% as compared to a 26% drop among women aged 25-49. AGYW previously benefited from PEPFAR’s DREAMS programs—packages of prevention services to address the high incidence of HIV among AGYW—but the number of program recipients decreased by 86% in FY25 as many of these programs were defunded.
  • Most alarmingly, the data do not include any information on HIV prevention services or PrEP initiation among key populations, including men who have sex with men, transgender people, and sex workers. This lack of data, coupled with the elimination of prevention programs for these populations, reflect an erasure of individuals at high risk for HIV that face life-threatening cuts to services.

Achieving Global 2030 Prevention Targets

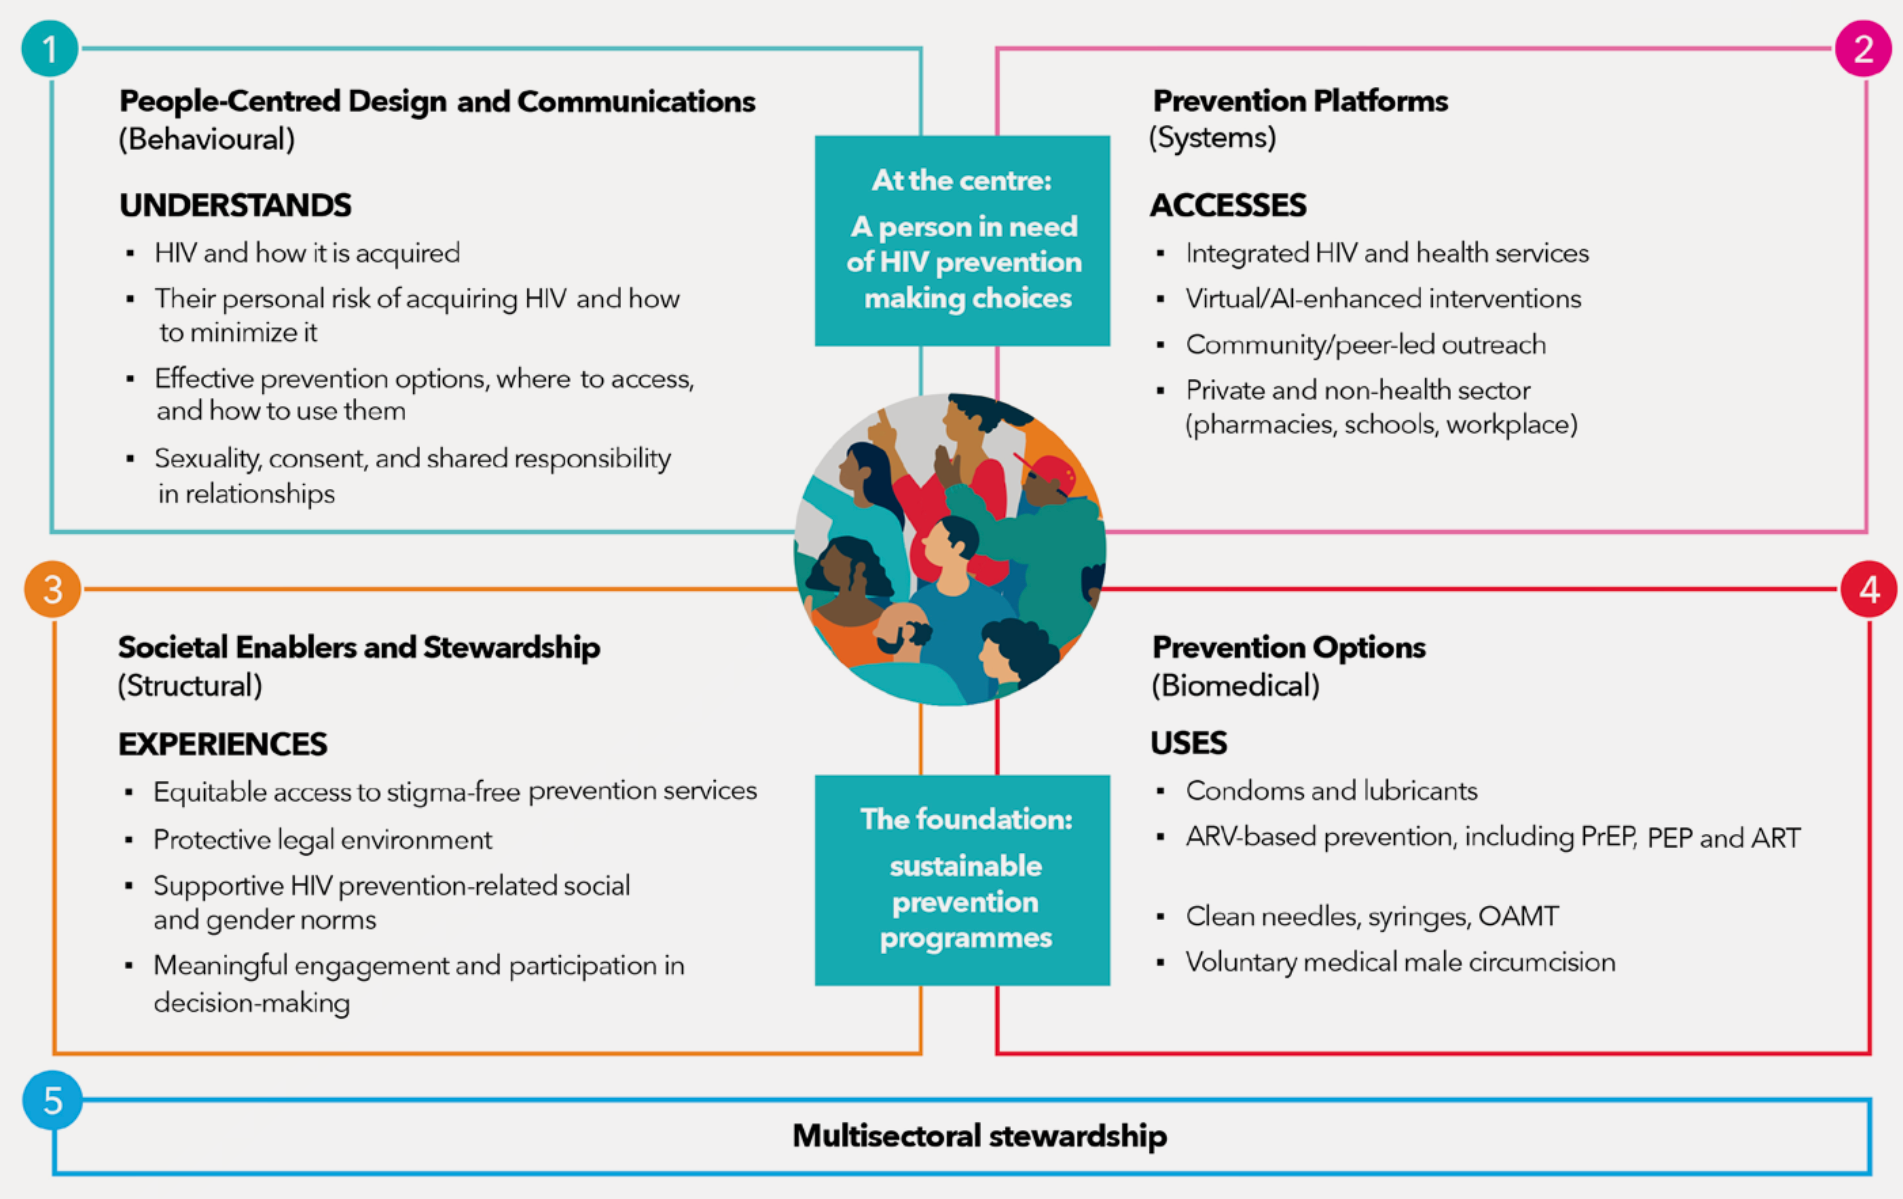
The Global HIV Prevention Coalition (GPC) recently launched its HIV Prevention 2030 Global Access Framework, outlining how, by 2030, countries can ensure that 90% of people in need of HIV prevention services have access and that 90% of people living with HIV are virally suppressed. This, in combination, would lead to a 90% reduction in new HIV infections globally. “Innovations, especially lenacapavir, have added to the array of prevention choices. History will judge us harshly if we as a global community fail to meet this scientific moment,” said Mitchell Warren, GPC Co-Chair on a recent webinar. Actions must be country-led, sustainable, people-centered, and rooted in community leadership to achieve these targets.

graphic from UNAIDS report graphic from UNAIDS report

Graphics: HIV Prevention 2030 Global Access Framework

PrEParing for New Products

  • On April 14, the US State Department and the Global Fund announced an increase of their original commitment of LEN for PrEP, from two million to three million people over three years.
  • Gilead has confirmed that it is not supply constrained and can supplement generic supply until it is steady, as long as they receive orders within time, based on their sixto nine-month production lead time needed. Generic supplies are expected to reach the market by the middle of 2027, but their capacity and lead times are not yet known.
  • While this is an important step, it does not go far enough to have meaningful impact on rapid scale-up of LEN, and there are no guarantees that the product will reach those who need it most, including key populations and adolescent girls and young women.
  • AVAC and Access Bridge see more potential to build the market by meeting market demand, leading ultimately to a reduced price, higher annual volumes and significantly increased impact.
  • To achieve this, key priorities over 2026 and 2027 must be advanced:
    • Global Fund and PEPFAR need to raise the floor of their commitment to reach at least four million people in two years.
    • Global Fund must ensure that they have the resources to procure these volumes and meet demand, requiring resource mobilization beyond the recent GC8 replenishment.
    • Global Fund and PEPFAR need to provide clear, transparent LEN access plans, with volumes and countries, ensuring a more comprehensive joint strategy in more countries, as well as volumes and prices with Gilead and generics.
    • All procurers must place orders for 2027 by June 2026 with both Gilead and generics to ensure uninterrupted supply and expanded global access, whether through the Global Fund or directly with manufacturers.
    • Ministries of Health must collaborate with implementation partners and civil society to ensure people-centered approaches to rollout, and to address supply and demand issues as they emerge and develop robust forecasts for 2027.
    • Generic manufacturers must specify their lead-times from order to delivery to coordinate and ensure timely procurement.
    • Gilead must urgently finalize license and supply agreements for middle-income countries, especially in Latin America and Asia.

The Latest in the HIV Research Pipeline

  • AVAC has recently begun to track the research pipeline for long-acting HIV treatment (LA-ART). This focus aligns with AVAC’s work to advance an integrated approach to ending HIV transmission, including a comprehensive agenda for the development of novel and longer-acting products beyond PrEP, inclusive of PEP and treatment.
  • A rapidly expanding pipeline for LA-ART has the potential to introduce new regimens with dosing frequencies that range from weeks to months to, eventually, years. The benefits of LA-ART include reduced drug dosing, frequency, and number of drugs, with the potential for associated decreases in the cost of medications and the burden on health systems. New drug classes could close treatment gaps in children, adolescents, and those with high viremia, comorbidities and resistance.
  • CROI 2026 highlighted the potential future LA-ART landscape beyond today’s 2-month CAB + RPV injections. The range of products in development includes novel characteristics such as new ART classes and monoclonal antibodies, new ARV combinations, delivery via oral, implantable and injectable formulations, and longer regimens—currently up to six-months.
  • Ongoing clinical research will hopefully further demonstrate whether there are trade-offs (treatment failures or resistance) between LA-ART and highly effective daily oral ART. In addition to the new long-acting products, simplified single-tablet daily regimens are also in development.

Building the Market for New Products from the Trial Stage

MK-8527 is currently in Phase III trials (EXPrESSIVE-10 and EXPrESSIVE-11) across 17 countries. To build a supportive environment around the concept of a monthly oral PrEP pill, AVAC supported the development of communications materials for use in the EXPrESSIVE-11 trial which can be adapted for future market entry. AVAC worked with local partners and MSM, transgender, and non-binary communities in 8 trial countries in Africa, Asia, and Latin America to co-create the materials, ensuring that focus populations contributed to the design. The result is a global campaign with a localized feel that is generating awareness on MK-8527 early.

English poster example
Portuguese poster example
Spanish language poster
Swahili language poster

Prevention Playlist

AVAC develops a wide range of resources to inform decision making and action. Check out the latest:

Join

Use

Watch/Listen

Read

AVAC Year in Review 2025

2025 underscored the vital role that AVAC plays in the global health ecosystem, and why our work and our partnerships have never been more essential.

This report highlights AVAC’s role as a trusted voice, a translator of science and catalyst for action and advocacy. It reflects an organization ready for the future: supporting African leadership, strengthening bridges from R&D to delivery and preparing for a new chapter as we move forward into our fourth decade as an organization. Read the PDF below or view as a webpage.

An Overview of Lenacapavir for PrEP Trials

The PURPOSE trials evaluate the safety and efficacy of injectable lenacapavir (LEN), an investigational antiretroviral (ARV) drug being studied as a potential PrEP product. This graphic shows the latest status of all five trials including the groundbreaking results of PURPOSE 1 and PURPOSE 2.

HIV Prevention R&D at Risk

Tracking the Impact of US Funding Cuts

The US presidential administration is actively working to dismantle HIV research and demolish the architecture of global health. The entire HIV response — from basic research and clinical development to policy, programs, and global access to life-saving treatment and prevention — is now under attack, and the world runs the risk of reversing the strides made to end HIV.

AVAC has put together this report, highlighting the impact of US cuts on the pipeline of HIV prevention research and development. AVAC will continue to track these cuts and their impact, to amplify the damage they will cause, and to fight for their reversal.

HIV-Specific Neutralizing Antibodies by Target

A number of broadly neutralizing antibodies that target various regions of HIV’s Env protein are being developed for HIV prevention.

Broadly Neutralizing Antibody Combinations

Overview of the combinations of broadly neutralizing antibodies (bNAbs) under investigation in early clinical studies for HIV prevention.

Avac Event

The Future of HIV Prevention: A People’s Research Agenda for Speed, Scale and Equity

First developed in 2024 in partnership with global advocates and communities, the People’s Research Agenda sets out a people-centered framework for equitable and accelerated R&D and product introduction. The PRA tracks the science, shows where investments align—or fail to align—with community-defined priorities, and spotlights critical gaps in the pipeline of prevention options needed to meet the diverse realities of all populations.

  • Featured speaker Jeanne Marrazzo, CEO of the Infectious Diseases Society of America and AVAC board member.
  • We covered what the People’s Research Agenda tracks, why it matters, and the advocacy priorities that will shape the future of prevention R&D.

View Recording / Download Slides

Moving a Product to the Real World

The rollout of oral PrEP demonstrates that people don’t take PrEP simply because it’s available—there needs to be a demand for it, and it needs to be accessible, acceptable and used effectively by those who need and want it. These are the lessons the field is applying to the rollout of the dapivirine vaginal ring (DVR), and injectable cabotegravir (CAB) and lenacapavir (LEN) for PrEP. To reach the UNAIDS target of 10 million PrEP users by 2025, initiations of oral PrEP alone will not be enough—and this graphic shows that the field is beginning to apply past lessons to accelerate introduction of injectable PrEP options.

And for the latest on lenacapavir, visit here.