Global Health Watch: Hepatitis B vaccine trial halted, HIV advocates demand action, LEN for PrEP access, Global Fund’s malaria accelerator

Issue 91

International pressure halted a controversial hepatitis B vaccine trial in Guinea-Bissau; HIV advocates rallied to protect US research funding as the midterm elections approach; and AVAC and Access Bridge call for accelerated access to LEN for PrEP. Meanwhile, the Global Fund prepares to select a new leader at its board meeting next week and vote on a proposed $2-3 billion malaria funding mechanism that could reshape the role of private philanthropy and country ownership in global health financing.

Guinea-Bissau Trial Halted, But Broader Vaccine Policy Concerns Remain 

Following last week’s uncertainty, the controversial US-funded hepatitis B vaccine trial in Guinea-Bissau was halted following international criticism and a police investigation. As The Guardian reports, judicial police seized vaccine doses earlier this week, and the study’s lead investigator confirmed that the trial would not proceed because it lacked government approval. The $3.2 million study, which received $1.6 million from the US Centers for Disease Control and Prevention (CDC), would have restricted hepatitis B vaccination from 7,000 newborns during their first six weeks of life. The global health community condemned the trial as unethical, especially given high rates of hepatitis B infection in the country and the WHO’s recommendation that all infants receive a birth dose within 24 hours. This week, a new US modeling study found that delaying the universal hepatitis B birth dose could increase chronic infections, adding to concerns about proposals to replace routine newborn vaccination with individualized decision-making. 

IMPLICATIONS: The Guinea-Bissau trial involved Danish researchers Peter Aaby and Christine Stabell Benn, whose work US Health Secretary Robert F. Kennedy Jr. has repeatedly praised and cited in support of his anti-vaccine policy agenda. This controversy reflects broader concerns about US vaccine policy and scientific independence. This week, the board overseeing the NIH Clinical Center publicly criticized the establishment of a new vaccine injury research clinic without prior consultation, raising concerns about political interference and public trust. Meanwhile, the US continues to experience a resurgence of measles, which is likely a result of growing gaps in vaccinations. Taken together, these developments highlight the importance of independent scientific oversight, ethical research practices and evidence-based immunization policies, both in the US and globally. 

READ:

HIV Advocates Demand Action to Protect HIV Research as US Midterm Elections Approach

Last Friday, the NIH finally released the long-delayed Notice of Funding Opportunity (NOFO) for the Centers for AIDS Research (CFARs), which is important. However, the long-awaited NOFOs to renew NIH’s HIV clinical trials networks remain outstanding. This week, 139 organizations sent an urgent letter to the US Congress, warning that overdue clinical trial funding, political interference in scientific research and the potential diversion of research funding jeopardizes decades of scientific progress with consequences extending far beyond HIV. Many of these organizations gathered during IDWeek 2026 for the Save HIV Funding campaign’s #CutsKill rally alongside panels of the AIDS Memorial Quilt to demand action. As Jeanne Marrazzo, CEO of the Infectious Diseases Society of America (IDSA), reminded partners at the rally, “Nothing has hurt me as much in the last year as the cruel and devastating cuts and attempts to silence us around HIV care, advocacy and research. Please keep fighting; we really need to just not look away for a second.” AVAC’s Mitchell Warren added, “It is possible today, and it’s possible because of science. But it’s going to be made real because of choices we all get to make.”  

IMPLICATIONS: The US mid-term elections are Tuesday, November 3, where new members of the US Congress will be elected. Their job will be to determine the future of federal HIV research funding and oversight. Advocates’ actions show the importance of sustained advocacy, and its success, in protecting decades of scientific progress. The release of the CFAR funding opportunity is a positive development, but the work is far from over. Watch the video from the rally and take action through Save HIV Funding. 

READ:

No Time to Lose: A Call to Reach Three Million People with LEN by 2027

AVAC and Access Bridge issued a global call to action and new publication urging governments, donors, manufacturers, implementers and advocates to accelerate the rollout of injectable lenacapavir (LEN) for PrEP to reach at least three million people by the end of 2027. This new, more ambitious target will drive affordability, build a sustainable PrEP market, and accelerate impact. It is a significant acceleration from the Global Fund and PEPFAR’s existing commitment to reach three million people over three years. AVAC and Access Bridge call on the Global Fund and PEPFAR to place orders now for enough doses to reach at least 2.4 million people in 2027, building on the 600,000 person-years ordered for 2026. Countries must forecast based on actual need rather than available budgets, regulators must accelerate approval of lower-cost generics, manufacturers must ensure sufficient supply, and additional donors are needed to be even more ambitious in 2027 and beyond. Equally important are investments in community-led demand creation and delivery systems that make LEN accessible as part of comprehensive prevention choice. 

IMPLICATIONS: The coming year represents a critical window for action and whether LEN’s extraordinary scientific promise translates into access at the speed and scale needed to reduce new HIV infections. Faster scale-up can create a larger, more sustainable PrEP market, driving prices down and expanding access to future prevention options. The ambition must extend beyond three million people in 2027 toward 20 million by 2030. As Access Bridge’s Wawira Nyagah says, “Three million people by the end of 2027 is a starting point, not an endpoint.” 

READ:

Global Fund’s Proposed Malaria Accelerator Tests the Future of Country-Led Financing

The Global Fund is considering a new funding mechanism that could mobilize an additional $2-3 billion for malaria programs through its proposed Malaria Impact Accelerator (MIA). This mechanism could expand access to existing malaria interventions and accelerate new innovations in countries with the highest malaria burden and lowest economic capacity. The New York Times calls the proposal “a potentially transformative shift” in global health financing, as technology entrepreneurs and investors anticipate substantial new philanthropic wealth from artificial intelligence (AI) companies. The proposed investment would give donors unprecedented influence over which interventions countries implement. The Global Fund Board is expected to vote on the mechanism at its board meeting next week, where it is also expected to elect its new leader.  

IMPLICATIONS: The prospect of billions in additional funding offers an important opportunity to accelerate malaria prevention and treatment amid shrinking development assistance. New donors bring resources and ambition, but sustainable progress against HIV, tuberculosis, malaria and other health threats depends on strong national health systems and community priorities that cannot always be captured through short-term metrics. But as the New York Times article highlighted, “In the documents outlining the terms of the deal to the Global Fund board, the organization’s executives said the arrangement would give a donor unprecedented power to decide what interventions a country will use, upending the model the Global Fund has used for nearly 25 years, and noted that the amount and duration of the support is uncertain, tied to a volatile industry.” As the Global Fund Board considers the proposal alongside upcoming leadership changes, its decisions could help define how emerging philanthropic investments complement, rather than reshape or replace, country-led global health financing.

READ:

Reaching Key Populations with Long-Acting PrEP

The need for PrEP amongst key populations (KPs) is high yet KPs remain underserved in many PrEP programs. To help address this need, Global Black Gay Men Connect, Access Bridge, and AVAC, alongside local partners in Eswatini, Kenya, and Zambia, convened Human Centered Design (HCD) Lite workshops to gather insights to develop KP-focused messaging on long-acting PrEP.  The resulting findings were synthesized into a demand generation toolkit, consisting of summary insights, guidance for developing materials, and sample materials.

Register

What We’re Reading

Resources

Aftershocks Roundtable: How do we rebuild our HIV and public health infrastructure?

Join The Choice Agenda and IAPAC’s José M. Zuniga – author of the new book “Aftershocks: Trump 2.0, Public Health, and Our Better Angels” – and a dynamic panel to discuss the profound disruption of public health systems over the past almost two years and the urgent need for a coordinated movement to defend and ultimately rebuild them.


Register

No Time to Lose: Reaching At Least Three Million with LEN for PrEP by 2027

AVAC and Access Bridge today issued a global call to action and new publication urging governments, donors, manufacturers, implementers, and advocates to work toward a bold but achievable goal: reaching at least three million people with injectable lenacapavir (LEN) for HIV prevention by the end of 2027. This new, more ambitious target will drive affordability, build a sustainable PrEP market, and accelerate impact.

“Scientific breakthroughs only matter if they reach the people who need them. LEN has the potential to transform HIV prevention and the overall epidemic response, but realizing that potential will require more urgency, more ambition, and more investment. Three million people reached by the end of 2027 is entirely feasible and an essential step toward ending new HIV infections. The field must commit to this: no less and no slower, with a push for more and faster.”

Mitchell Warren
Executive Director, AVAC

Since results of efficacy trials were announced in 2024, injectable lenacapavir for PrEP (LEN) has generated enormous excitement. By the end of 2024, Gilead Sciences provided voluntary licenses to generic manufacturers and submitted multiple regulatory filings, and the Global Fund and PEPFAR initially committed to reach two million people over three years with LEN, and then increased it to three million in three years. As of October 2026, LEN is recommended by WHO; has 19 regulatory approvals, and counting; is being introduced in 36 implementation science projects; and is being introduced as part of public health programs in 29 countries, with support from the Global Fund and PEPFAR. 

Recent progress has demonstrated both the feasibility and demand for long-acting HIV prevention. Rapid regulatory approvals and national introduction efforts have laid the groundwork for broader access. At the same time, community demand for long-acting prevention options continues to grow, particularly among populations that face barriers to daily oral PrEP use. If stakeholders fumble the moment, demand risks outpacing supply by large margins, which will harm public trust in prevention efforts. 

The coming year represents a critical window for action. Our publication, Now What with Injectable LEN for PrEP: How to Translate Ambition into Accelerated Delivery and Impact outlines how to reach at least three million people with LEN by the end of 2027, including two potential scenarios for LEN market development, and where advocates can demand action. 

To reach at least three million people with LEN by the end of 2027 and 20 million by 2030, AVAC and Access Bridge are calling on:

  1. Countries to provide ambitious forecasts based on actual demand and need and programmatic opportunity, not based on budget.
  2. Global Fund and PEPFAR/GHSD to place orders now for enough doses for at least 2.4 million people in 2027 (given that 600,000 per years of LEN was ordered for 2026). In addition, advocacy needs to mobilize domestic resources and other new donors to increase volumes further.
  3. National regulators to ensure rapid approval and/or regulatory waivers of generic LEN so that there are no delays in transitioning from Gilead to lower-priced generics, which should begin happening early next year, and that there is adequate and consistent access to product in-country. 
  4. Gilead and the approved generic manufacturers to commit the supplies to make this delivery schedule in 2027 and ensure commodity security.
  5. Countries and communities to develop the programmatic infrastructure and robust demand creation to deliver that quantity as part of comprehensive prevention choice programs, so that product reaches people who need and want it and that no product is wasted.

“Three million people by the end of 2027 is a starting point, not an endpoint. We have a historic opportunity to reshape the trajectory of the HIV epidemic, and we are just getting started. The question is not whether the field can move quickly enough; it’s whether we choose to.”

Wawira Nyagah
Executive Director, Access Bridge

Scaling LEN must be part of a broader commitment to prevention choice. The HIV prevention landscape is entering a new era: beyond LEN is the potential inclusion of new methods like the investigational monthly PrEP pill alimatravir (AMI), which is undergoing clinical trials now. The PrEP market from 2028 could be far more complex and competitive. 

No single product will meet everyone’s needs, but expanding access to a diverse range of prevention options is essential to ensuring that all individuals can find methods that work for them. AVAC and Access Bridge urge partners across sectors to align around a common objective now: turning the promise of LEN into measurable public health impact for millions of people around the world. 

Read the full Now What with Injectable LEN for PrEP: How to Translate Ambition into Accelerated Delivery and Impact here. 

Global Health Watch: World Health Summit highlights, UN pandemic declaration, Guinea-Bissau vaccine trial, NIH peer-review changes

Issue 90

Challenges and scientific progress took center stage at the World Health Summit in Berlin, the UN adopted a new pandemic preparedness declaration, concerns continue over the proposed US-funded hepatitis B vaccine trial in Guinea-Bissau, and proposed changes to NIH’s scientific peer-review process raise new questions about transparency and political influence over research funding.

World Health Summit Highlights Challenges, Leadership and HIV Cure Progress

In Berlin, the World Health Summit (WHS) brought global health leaders together this week to discuss the future of global health financing, governance, scientific innovation and the growing impact of conflict on health systems. Jirair Ratevosian summarizes WHS and whether global health institutions are keeping pace with a changing world and highlights the featured public discussion with prospective candidates for WHO Director-General, which gave some insight into their priorities for the organization’s future. Sara Jerving of Devex covered the summit, as well, and concluded, “The global health sector can innovate, collaborate, and come up with all the clever solutions it can. But that will continue to fall drastically short when wars continue to rob millions of people of any chance of living healthy lives.” And at the opening of its new HIV cure research center, the Charité medical school and hospital in Berlin publicly named the “second Berlin patient” cured of HIV, Thomas Kahlert.

IMPLICATIONS: The WHS highlighted challenges facing global health institutions amid declining official development assistance (ODA), growing conflicts that are disrupting essential services and increasing calls from countries and communities for greater ownership and accountability. The news of the “second Berlin patient” shows what sustained investment in science can achieve, even as researchers work toward innovations that are effective, safe and accessible to all. 

READ:

UN Adopts Pandemic Preparedness Declaration 

The United Nations General Assembly adopted the Political Declaration on Pandemic Prevention, Preparedness and Response on Monday with 153 countries voting for the Declaration and three dissenting – Argentina, Isreal and the United States – and two countries, New Zealand and Paraguay, abstaining. Consensus on the text was not achieved at the September 25 Second High-Level Meeting on Pandemic Prevention, Preparedness and Response (PPPR), and negotiations continue over the Pathogen Access and Benefit-Sharing (PABS) annex to the separate WHO Pandemic Agreement, which would establish how countries sharing pathogens and genetic data benefit from the medical products developed using them.

IMPLICATIONS: The Declaration shows international support for pandemic preparedness, but as Friends of the High-Level Meeting on Pandemic Prevention, Preparedness and Response warn, the Declaration “contains few measurable or time-bound commitments,” and they challenge all Member States “to set ambitious, time-bound targets to ensure that we are truly able to prevent, prepare for, and respond to health emergencies and pandemic threats.” The disagreements over PABS speak to the division over access to vaccines, treatments and diagnostics, with many arguing over whether access should depend on voluntary arrangements or enforceable guarantees of equitable benefit-sharing. WHO and advocates are urging countries to reach an agreement over PABS by May, so the Pandemic Agreement can move forward. US government and other high-income country objections to PABS provisions, along with their failure to support the finalized Declaration, loomed over negotiations. The US government, in particular, used hardline rhetoric in expressing disagreement over the use of WTO waivers and uncompensated technology transfers. It also took divisive ideological positions, rejecting the Declaration’s references to climate change and sexual and reproductive health and rights. Moreover, the US government sought to ban international support for “gain-of-function” research. Overall, the experience illustrates the US government’s preference for entering into bilateral agreements rather than multilateral accords, while maintaining domestic oversight of biomedical research and intellectual property. 

READ:

Guinea-Bissau Denies Approving Controversial hepatitis B US-Funded Vaccine Trial 

New reporting raises further concerns about a proposed US-funded hepatitis B vaccine trial in Guinea-Bissau, which has raised significant questions over African public health leadership, ethical research standards and sovereignty. As we reported previously, the proposed trial would delay birth-dose vaccination for thousands of newborns despite overwhelming evidence and WHO guidance that immediate vaccination saves lives. This week, The Guardian reports that Guinea-Bissau’s government denied approving the study, which contradicts claims that researchers had received authorization to proceed. Meanwhile, the US Centers for Disease Control and Prevention (CDC) is said to have begun efforts to allocate $1.6 million in global health security funding for the trial. 

IMPLICATIONS: The proposed study and questions surrounding its approval continue to raise fundamental concerns about research ethics, national sovereignty, the use of US global health funding and the continued anti-vaccine ideology of US Health and Human Services Secretary Robert F. Kennedy Jr. Delaying access to a proven, effective vaccine could expose newborns to preventable infections. Guinea-Bissau’s rejection of claims that it approved the trial reinforces the importance of country leadership, independent ethical review and protecting research participants, particularly vulnerable populations. 

READ:

NIH Peer Review Proposal Highlights Transparency and Scientific Independence Risks

The US National Institutes of Health (NIH) closed its public comment period on proposed changes to its scientific peer-review process, which informs research funding decisions. The Infectious Diseases Society of America (IDSA) and HIV Medicine Association (HIVMA) were among the organizations submitting a comment. The proposed process would replace numerical peer-review scores with three broad categories: “most competitive,” “competitive” and “not discussed.” NIH leadership argues the change would give the agency greater flexibility to consider factors beyond small differences in scores as part of its proposed Unified Funding Strategy. However, scientists and research organizations warn that removing numerical scores from subsequent funding decisions could weaken accountability and make it harder to determine whether grants are awarded based on scientific merit.  

IMPLICATIONS: This proposal is yet another development that raises concerns about transparency and political influence over which studies receive support. NIH’s peer-review system has long been a foundation of independent, merit-based scientific research. Replacing numerical scores with broader categories could give NIH officials greater discretion over funding decisions while reducing the information available to researchers and advisory councils. 

READ:

HIV advocates sound alarm as NIH hits ‘pause’ on new HIV clinical trials

Following last week’s New York Times report on the NIH’s directive that its four HIV clinical trials networks temporarily pause launching new HIV clinical trials amid delays in renewing funding for its HIV research networks, Positively Aware highlights advocates’ growing concerns about the future of HIV research.

Next Wednesday, October 21 at 12:15pm during IDWeek in Washington DC at the Convention Center, join the Save HIV Funding campaign for a rally demanding the US Congress to release federal HIV research funding and for an opportunity to experience the #CutsKill quilt panels.

Read More

What We’re Reading

Resources

Investing in Biomedical Innovation for Health and Economic Growth

This Financial Times webinar will bring together policymakers, funders, researchers, philanthropies and industry leaders to explore how to keep medical innovation moving forward. The conversation will examine how to create the right conditions for future breakthroughs – and deliver clear benefits for patients, health systems, economies and society.

Register Now

Global Health Watch: NIH Orders Pause on HIV Trials, Zimbabwe + Zambia Health MoUs, WHO + Global Fund leadership, Foreign Assistance Funds

Issue 89

The US National Institutes of Health (NIH) said its HIV clinical trial networks should “temporarily hold off on launching new studies that had not yet enrolled participants and that would not be complete by November 30, 2027, when their current funding is set to expire.” This potentially devastating development comes as new questions emerge about how billions in US foreign assistance funding were spent, and details on the impacts of an end of US health assistance to Zimbabwe emerge. Also, a new candidate for WHO leadership and growing civil society calls to protect UNAIDS.

NIH Orders Pause on New HIV Clinical Trials Amid Funding Delays 

The National Institutes of Health (NIH) instructed leaders of its four HIV clinical trials networks to temporarily pause launching new studies that have not yet begun enrolling participants and would extend beyond November 30, 2027 (when funding expires). As The New York Times reports, this comes amid continued delays in releasing Notices of Funding Opportunities (NOFOs) to renew the networks and the Centers for AIDS Research (CFARs) for the next seven years, threatening research infrastructure built over decades and potentially disrupting clinical trials and services for participants. In response, AVAC, along with allies PrEP4All, HIVMA, TAG, and AIDS Action Baltimore as part of the Save HIV Funding Campaign are inviting sign-ons to a letter to Congress demanding that the US Department of Health and Human Services (HHS) authorize the long overdue funding announcements. Organizations can sign-on by October 15. 

IMPLICATIONS: The affected clinical trial networks include the Advancing Clinical Therapeutics Globally for HIV (ACTG), HIV Prevention Trials Network (HPTN), HIV Vaccine Trials Network (HVTN), and the International Maternal Pediatric Adolescent AIDS Clinical Trial Network (IMPAACT). The delayed renewal of the networks and the directive to hold off on launching new studies create uncertainty for the research pipeline, potentially delaying scientific advances, disrupting services for trial participants and weakening infrastructure built over decades. These networks have yielded critical advancements for HIV treatment and prevention and are important catalysts for tuberculosis treatment and prevention research, and for other emerging infectious diseases. Simultaneously, the proposed NIAID reorganization raises questions about the future of centralized clinical research oversight and support. As AVAC shared with the NIAID Council and the AIDS Research Advisory Committee (ARAC) at their meeting September 27, “Collectively, these programs have saved millions of lives over the last several decades and advanced some of the most important scientific discoveries and implementation science advances. Delays in the release of the NOFOs are forcing clinical trial sites to prepare for lapses in funding that could harm study participants, halt promising clinical trials, and erode the scientific workforce and infrastructure that has taken decades to develop.” In sum, the continued attacks on the HIV research infrastructure could reshape the trajectory of research for years to come.

READ:

US Health Assistance Ends in Zimbabwe as Zambia Signs New Agreement 

The US Department of State was said to begin implementing its America First Global Health Strategy across 35+ partner countries on October 1, the start of the US fiscal year. But this is all evolving differently across countries. In Zimbabwe, US bilateral health assistance ended September 30 after the two countries failed to reach an agreement. Health GAP details the disagreements, which include sharing health data and biological specimens, but more importantly, major reductions in US funding and co-financing requirements that would have required Zimbabwe to increase its contributions by 290% in the first year. It proposes several next steps to avert the crisis. Health Policy Watch reports that “researchers project that there could be over 75,000 new HIV infections in Zimbabwe within a year ‘as a consequence of full PEPFAR withdrawal and no additional government or international support’.” 

In contrast, the US and Zambia signed a five-year, $2.49 billion health agreement yesterday, following months of negotiations. Zambia reports that requirements to share patient-level health data and biological specimens were removed, while negotiations over critical minerals were separated from the health agreement. Meanwhile, South Africa is preparing for the phaseout of PEPFAR support by March 2027, raising concerns about the future of community-based HIV prevention and treatment services. 

IMPLICATIONS: The withdrawal of US health assistance in Zimbabwe could dismantle decades of progress against HIV, TB and malaria, with consequences beyond the immediate term. Health GAP warns that the crisis could disrupt Zimbabwe’s introduction of injectable lenacapavir for HIV PrEP, jeopardizing access to one of the most important recent advances in HIV prevention. The implications are particularly alarming because these are interconnected programs: disruptions to community health workers, laboratories, supply chains and service delivery can undermine responses to all three diseases simultaneously. 

READ:

Foreign Assistance Funds Committed as Questions Over Spending Persist 

The US 2026 fiscal year ended on September 30, and the picture is becoming slightly clearer on how billions of dollars of Congressionally-appropriated global health funding was actually spent. According to Devex and in court filings, the US Department of State committed more than $4 billion in foreign assistance funding just before the end of the fiscal year, preventing much of that money from expiring. A new filing in the Global Health Council and AVAC court cases shows that only $18,919 in Global Health Programs funding for which the State Department was responsible expired without being committed. However, the filing also identifies funds committed to covering the costs of closing out USAID, rather than supporting health and development programs as Congress had intended.  

IMPLICATIONS: This adds to concerns raised last week about the transfer of $2.5 billion originally intended for global health and development assistance into an alternative or ‘miscellaneous’ account. While the government appears to have met much of the deadline for committing funds, questions remain about where the money is going, whether it is being used as Congress intended and when it will actually reach programs and communities. As AVAC’s Mitchell Warren summarized last week, “the issue extends beyond foreign assistance or the HIV response; it is fundamentally about Congress’s constitutional power of the purse.” 

READ: 

WHO and Global Fund Leadership Updates

Last week, leadership candidates for the Global Fund to Fight AIDS, Tuberculosis and Malaria, and WHO were announced. This week, China confirmed its nomination for WHO Director-General, expanding the known candidates to seven and raising questions about geopolitical influence as the US withdraws from the organization. On his Global Health Insights Substack, former WHO Adviser Peter Singer published a scorecard examining how specifically candidates have articulated plans to deliver measurable results and protect WHO’s scientific independence. And in Lights. Camera. Equity!, former Global Fund Board member Jirair Ratevosian called for greater public engagement in the Global Fund’s selection process. He reported that the Fund confirmed it has no plans for a public candidate forum, with engagement instead taking place through Board constituencies. 

IMPLICATIONS: These developments raise questions about transparency and accountability in choosing the next generation of global health leadership. These new leaders will face immediate decisions that will shape how these institutions define their roles in an evolving architecture. WHO is already reducing its staff significantly after the US refused to support it, and the Global Fund is facing difficult decisions about where and how to invest its smaller Grant Cycle 8 budget. 

READ:

Civil Society Calls for Protecting UNAIDS

Ahead of the October 26 UNAIDS Programme Coordinating Board (PCB) meeting, more than 225 civil society organizations signed an open letter urging members of the PCB to protect the Joint Programme from being dismantled through proposed funding, staffing and operational cuts. Advocates warn that proposals to reduce UNAIDS to a $30 million budget and just 34 staff could undermine its ability to coordinate the global HIV response, defend human rights and ensure meaningful community leadership and accountability. 

IMPLICATIONS: The upcoming UNAIDS PCB meeting will be a defining moment in determining the Joint Programme’s essential functions and whether and how reform can preserve UNAIDS’ leadership, accountability and community engagement.

READ:

What We’re Reading

Resources

The Latest Resources from AVAC: The Power of Coalition Advocacy

Advocacy has always been the heartbeat of progress in the fight against HIV/AIDS. Now, more than ever, it is especially needed to ensure that innovation translates into real choices, equitable access and meaningful impact. In this issue, we highlight the power of coalition advocacy – from advocates working in partnership to shape research agendas and oppose policies that threaten progress, to ensuring communities have a voice in AI development and use, to the lessons learned from sustained, coalition-based advocacy that will shape what comes next. 

Protecting HIV Research Amidst Threats to NIH

Following advocacy by AVAC, advocates, researchers, scientific institutions and members of the US Congress, the White House dropped plans for an Executive Order that would have given an external review committee decision-making power over billions of dollars in biomedical research funded by the National Institutes of Health (NIH).  

The reversal came as the National Institute of Allergy and Infectious Diseases (NIAID) Council and AIDS Research Advisory Committee met to discuss the proposed reorganization of NIAID that would eliminate the Division of Clinical Research and redistribute clinical research functions across the Institute – a move that threatens the incredible progress that has been achieved toward HIV treatment and prevention as well as potentially putting lives at risk. AVAC delivered a public comment at the meeting, urging NIH to withdraw the proposal, provide greater transparency and meaningful opportunities for community input, and immediately release delayed funding opportunities for the HIV Clinical Trials Networks and Centers for AIDS Research (CFARs).  

Now, the picture has become even more complicated, with the NIH notifying HIV researchers last Friday that they should pause launching any new studies that had not yet enrolled participants and that would go beyond November 30 of next year when current funding expires. 

The Save HIV Funding Campaign, which AVAC co-founded with PrEP4All and the HIV Medicine Association (HIVMA), requests organizations to consider signing on to this letter that urges Members of Congress to demand that the US Department of Health and Human Services approve the release of overdue Notices of Funding Opportunities (NOFOs) that fund the NIH HIV clinical trials networks and the CFARs for the next seven years. This funding is essential to the continuation of HIV research, including clinical trials that involve people who receive vital services. The deadline for signing on is Thursday, October 15th.  For individuals in the US, please consider sending emails to your members of Congress through this link.

Read AVAC’s remarks on the proposed NIAID reorganization 

Advocates Lead in Rio: Moving from a seat at the table to the head of the table 

At AIDS 2026, advocates didn’t just join the conversation – they drove it. From HIV prevention choice and equitable access to community-led research and the future of HIV prevention, advocates brought bold priorities, lived experience and accountability to the center of the global HIV response. Across panels, protests, satellites and strategic meetings, communities made clear: there is no effective HIV response without community leadership. As WHO Director-General Dr. Tedros Adhanom Ghebreyesus put it, communities are “its architects.” In AVAC’s latest blog, Senior Program Manager Navita Jain reflects on the power of communities at the conference, and AVAC’s top ten list compiles the takeaways influencing the field well beyond the conference.  

Read how advocates led the narrative at AIDS 2026

The Clinical Trial Design Academy: Equipping Advocates to Shape HIV Prevention Research Decisions and Move the Research Agenda Forward 

AVAC’s Clinical Trial Design Academy (CTDA) brings together advocates with diverse perspectives and technical expertise to strengthen their ability to shape HIV prevention research. Through the network, members share knowledge, engage directly with researchers and work collectively to ensure community priorities inform research agendas and trial decisions. From shaping the People’s Research Agenda to influencing the design of the EXPrESSIVE trials of monthly oral alimatravir for PrEP, CTDA members are demonstrating the power of a connected, technically informed advocacy network to move research forward. As Kenyan CTDA member Simon Ondiek shared, “beyond the technical skills, the biggest impact has been the network we’ve built—a community that continues to learn from one another and ensure research remains responsive to community realities”. The CTDA meets in person this week—stay tuned for updates and outcomes. 

Read about the CTDA’s collective impact on HIV prevention research 

AVAC’s AI & HIV Newsletter

Artificial Intelligence (AI) is already being used in HIV programming, making the need for community leadership an urgent matter. “Community governance must be part of that infrastructure, not an advisory layer added at the end, but a legitimate source of expertise and authority in setting the rules,” writes ITPC Executive Director, Community Working Group Co-Lead of the Lancet Commission on AI + HIV, and AVAC Board Member Solange Baptiste. AVAC’s quarterly AI and HIV newsletter provides advocates with the information and resources to advance community prioritization in AI. The latest issue looks across important perspectives like Baptiste’s, alongside data from AIDS 2026 emerging tools, policy developments and research shaping how AI is developed, governed and used across HIV and global health.  

Read the AI & HIV Newsletter 

CASPR Impact Report: Celebrating Growth, Inspiring the Future 

The CASPR Impact Report: Celebrating Growth, Inspiring the Future captures what is possible when long-term investment in African leadership, partnerships and coalition-based advocacy is matched with shared purpose. The Coalition to Accelerate and Support Prevention Research (CASPR) is an Africa-led movement that connects communities, researchers, policymakers, journalists and funders to transform HIV prevention advocacy. Over the past decade, CASPR proved that community-led coalitions are central to turning innovation into action and ensuring that advances in HIV prevention are shaped by the people they are meant to serve, while offering a blueprint for the future HIV prevention advocacy. 

Read the CASPR Impact Report 

Additional Resources from AVAC and Our Partners

Sign up for newsletters from AVAC and our partners

Access Bridge is an independent, Africa-anchored organization advancing timely, sustainable, and equitable introduction of and access to HIV prevention and related health products. To receive updates on Access Bridge’s work and impact, sign up for the newly launched newsletter.

STIWatch is AVAC’s resource for the sexual and reproductive health and rights (SRHR) community to better understand and advocate for STI vaccine and diagnostics research, development and rollout. To receive the latest on data and new resources, sign up to receive updates on STI prevention.

Advocates Lead at AIDS 2026: Moving from a seat at the table to the head of the table  

By Navita Jain, AVAC Senior Program Manager & Team Lead: Partnership Network

The power and leadership of advocates were on full display at AIDS 2026. Following global funding cuts and concerns about de-prioritization of communities and civil society, advocates brought evidence of their impact and the value of continued investment in communities to Rio. On topics ranging from HIV prevention access to the future of artificial intelligence in HIV programs, advocates were driving conference discussions to ensure the community agenda was seen, heard and acted upon.

During the HIV prevention pre-conference, we were reminded that the time to engage communities in research was “yesterday” – but the next best time to act is now.

Adaobi Olisa of Root to Rise in Nigeria highlighted the impact of AVAC’s Clinical Trial Design Academy as an example of what “getting it right looks like.” Platforms like the Academy focus on translating complex scientific concepts to inform specific and nuanced research advocacy priorities for the field.

“This [trials] is the hardest place to get community engagement right and is also the easiest place to skip it…if communities are not at the table when solutions are being conceived, being conceptualized, or when trials are being designed, then we’re already missing the point.”  

Advocates also brought a reality call to the conference, illustrating what the HIV community is up against – from combatting vaccine hesitancy to maintaining confidence in research. Ntando Yola of Advocates for the Prevention of HIV in Africa (APHA) drew on the People’s Research Agenda‘s recommendations and priorities for HIV vaccine R&D, reminding stakeholders that in the current environment “we need to continue fighting against all of these agendas that are anti-vaccine, as well as threaten a lot of work that we have put into advancing HIV prevention, and in particular, HIV vaccine research and development.” 

AVAC Regional Program Manager Grace Kumwenda leads advocates through a discussion around HIV vaccine research and development.

Throughout the conference, on panels, at protests and in private meetings, advocates seized opportunities to directly communicate where the field is falling short in delivering equitable access to HIV prevention. They pushed for the expansion of licensing of HIV prevention products, price transparency, ambitious supply volumes and a commitment to prioritize key populations. In a satellite session co-hosted by AVAC and Global Black Gay Men Connect (GBGMC), Josephine Aseme of the Nigeria Key Populations Health and Rights Network and the first person to receive lenacapavir (LEN) for PrEP in Nigeria stated, “It is good for stakeholders to understand that communities build trust, and without trust there is no prevention option that is going to have effective impact.” Erasure of key populations cannot be tolerated and leads to the breakdown of trust among communities. Danielle Campbell echoed this message in a satellite on long-acting HIV prevention implementation. 

“Scientific breakthroughs alone do not end epidemics. We do. People do. Community does. Innovation only changes lives when it reaches the people who need it most…that’s representative of every individual stakeholder that you see on the stage and how we can bring to bear long-acting injectables for our respective communities.” 

The African Women’s Prevention Community Accountability Board (AWPCAB), a leader in advancing HIV prevention choice for women, convened critical discussions on public stages and via strategic meetings with country leadership, gaining tangible commitments from heads of government around choice. Ministry of health representatives from South Africa and Zimbabwe endorsed moving forward a framework toward integrated, domestically-owned and -managed, primary health care-centered systems in which HIV prevention and treatment remain visible and community-based and community-led platforms are recognized as essential. The AWPCAB also advanced its focus on women across their lifecycle – ensuring young women had a platform to speak and providing critical mentorship to the next generation of advocates while also emphasizing care and support for women living with HIV as they age. Yvette Raphael, AWPCAB co-chair and advocacy leader in South Africa and globally, reminded audiences to look at women holistically and not just based on clinical results: 

“We are made vulnerable when systems refuse to see us, listen to us, fund us, or design care around our real lives.” 

Yvette Raphael
APHA ED & AWPCAB co-chair, Report from The Lancet HIV commission on HIV and ageing satellite

AVAC’s Navita Jain and Victor Adula, Executive Director at Consolation East Africa in Kenya and member of the Global Advocacy Data Hub (GADH), in front of the community quilt

Throughout the conference, AVAC’s HIV Cure and Prevention Research Networking Zone served as a space to connect researchers and advocates, refine advocacy strategies and tactics, share advocacy tools and resources, and network with influential stakeholders. Advocates came together to discuss new research on HIV cure, challenges across geographies for access to LEN for PrEP, ongoing trials of monthly oral alimatravir (AMI) for PrEP and HIV vaccine and antibody research. The Zone also hosted the launch of a new community quilt, created by the Global Advocacy Data Hub, the Coalition to build Momentum, Power, Activism, Strategy & Solidarity (COMPASS) and the Save HIV Funding campaign, that builds on the history of community quilts for AIDS advocacy. Participants added personal advocacy messages to the quilt to drive home a key message: community and civil society data is critical to advocacy.

In looking to the future, ITPC Executive Director and AVAC Board member Solange Baptiste elevated the role of community in innovation, noting “the future of AI in HIV should be shaped with communities, not simply built from data about them.”  

Solange Baptiste speaks at AI and HIV: Who owns the future of public health? satellite

As Dr. Tedros Adhanom Ghebreyesus, World Health Organization (WHO) Director-General said, “Communities have never been an optional partner in this response. They are its architects. They reach the people health systems cannot. They defend human rights. They hold all of us to account. The next chapter of the HIV response must be written not only for communities but with communities.”  

This is the collective impact and leadership of communities. Since AIDS 2026, advocates have continued to come together to write the next chapter in the HIV response – working diligently to advance priorities and ensure civil society and community leadership are built into new and evolving global health platforms. AVAC and partners continue to fight for a future where advocates chart the course for the HIV response.   

Global Health Watch: Billions in Question, NIH + America First Plans, WHO + Global Fund Leadership & PPPR Rejection

Issue 88

The US fiscal year ended this week amid questions about the billion dollars in Congressionally-appropriated foreign assistance, while new strategies for HIV research at the National Institutes of Health (NIH) and the America First Global Health strategy theoretically move into implementation phases. Also, the Global Fund announced five candidates for its Executive Director, and six candidates were shared as possible leaders of the World Health Organization (WHO), just after the US rejected the UN pandemic preparedness declaration at the end of last week.  

Fiscal Year Ends with Billions in Global Health Funding in Question 

The US 2026 fiscal year ended Wednesday, September 30, and it is not at all clear how billions of dollars of Congressionally-appropriated global health funding were actually spent – and even if it was spent. Lawmakers, including Senate Appropriations Committee Chair Susan Collins (Republican from Maine, who is up for re-election), pressed the Administration to release all funds and raised concerns that some global health and development assistance resources were instead being redirected toward costs associated with closing USAID. According to Devex, “not all foreign aid money will be used as originally intended by Congress.” The State Department moved $2.5 billion previously slated for global health and development assistance into a miscellaneous, non-expiring account, preventing the funds from immediately expiring. However, the Administration has indicated that those funds will be used toward closing out USAID.  

Separately, the Administration tried to cancel $810 million of other Congressionally-appropriated funds via a so-called “pocket rescission,” submitting the request just days before the end of the year. These are funds Congress approved, but the Administration is seeking to withhold as the fiscal year ends. The US Government Accountability Office (GAO) concluded that it is not legal for the President to withhold these appropriations beyond the end of the fiscal year without Congress approving their rescission. 

IMPLICATIONS: These year-end actions bring a sense of déjà vu. One year ago, at the end of the US 2025 fiscal year, the Supreme Court ruled in their “shadow docket” in litigation brought by AVAC and the Global Health Council (GHC) and partners that allowed the Administration to continue withholding billions in Congressionally-appropriated foreign assistance funding. In a new development this week, Judge Amir Ali who oversees the GHC and AVAC’s case, suspended the September 30 expiration date for any disputed funds that State or USAID failed to obligate, meaning those funds remain available while the court examines what happened. As AVAC Executive Director Mitchell Warren said this week, “the issue extends beyond foreign assistance or the HIV response; it is fundamentally about Congress’s constitutional power of the purse.” Congressional appropriations mean little if funding approved for HIV, TB, malaria, maternal and child health and other programs is delayed, redirected or allowed to expire before it can reach programs and people. Delays in transferring funding to programs force them to re-budget or stop or limit certain functions, until funding is received. A year after AVAC and GHC went to court over the withholding of foreign assistance, the same fundamental fight over whether the executive branch can decline to spend funds Congress has appropriated remains unresolved. 

READ:  

New 5-Yr NIH Plan Released and America First Global Health Plans Said to Begin 

October 1 marked the start of the new US fiscal year and, in theory, two new strategies are beginning to be implemented. The US National Institutes of Health (NIH) released its FY2026–2030 Strategic Plan for HIV and HIV-Related Research, which describes priorities for the next five years across the HIV research continuum. At the same time, the US Department of State planned the start of country implementation plans under the America First Global Health Strategy, which is reshaping how the US funds and delivers global health assistance across 35 countries. Yet according to Devex, as implementation begins, those country plans have not been publicly released or provided to Congress, even as the Administration moves ahead with new bilateral agreements and greater government-to-government financing. 

IMPLICATIONS: The NIH’s new HIV research strategy calls for strengthening research capacity and infrastructure and moving discoveries across the “research-to-practice continuum”, including an emphasis on implementation. However, it is released just as a restructuring of NIAID is proposed, including plans to do away with its Division of Clinical Research and redistribute some core clinical research functions across the Institute. Meanwhile, the America First Global Health Strategy is reshaping how US-supported programs are financed and delivered in countries. These changes from preclinical work to develop new innovative products to ensuring they get to the people who need them most, is in a major transition, which makes implementation very hard to plan for.   

READ:

Global Fund and WHO Leadership

The Global Fund for AIDS, TB and Malaria named five finalists to take over as Executive Director after Peter Sands steps down at the end of the year. The Global Fund Board will engage with the finalists over the coming weeks and is scheduled to appoint the next Executive Director at its October 28–30 meeting. The World Health Organization (WHO) also identified six prospective candidates to succeed Director-General Tedros Adhanom Ghebreyesus. The complete official slate will not be announced until on or after October 29, with a candidates’ forum beginning November 18 and the final election at the World Health Assembly in May 2027.  

IMPLICATIONS: These leadership changes come amid much uncertainty as the global health architecture is being reshaped by many factors including reduced assistance, calls for greater country ownership and domestic financing, institutional reform and the US withdrawal from the WHO. WHO is already reducing its staff significantly after the US refused to support it, and the Global Fund is facing difficult decisions about where and how to invest its smaller Grant Cycle 8 budget. These new leaders will face immediate decisions that will shape how these institutions define their roles in an evolving architecture. 

READ:

US Rejects UN Pandemic Preparedness Declaration

Last Friday at the UN General Assembly’s (UNGA) High-Level Meeting, the United States declined to support a new UN Political Declaration on Pandemic Prevention, Preparedness and Response (PPPR), which breaks consensus around a declaration intended to demonstrate global political commitment to prepare for future pandemics. The US cited “divisive ideologies that lack definitional consensus” and objected to references to the ongoing negotiations over pathogen access and benefit sharing (PABS). The European Union raised separate objections around intellectual property and technology transfer; Italy also rejected the declaration; and India and Germany expressed reservations. The declaration is expected to be voted on by the General Assembly where it could still be adopted.   

IMPLICATIONS: The fact that consensus was not reached shows a major divide over the architecture being built to prevent and respond to the next pandemic. As Georgetown University’s Lawrence Gostin wrote, “UN high-level meetings are designed to showcase uniform geopolitical alignment against universal threats like pandemics. By breaking consensus, the US has signaled that domestic sovereignty outweighs collective diplomatic solidarity on global health architecture.” 

The declaration is important in that it helps outline who pays, who gets access to vaccines, diagnostics and treatments, how technology and pathogen information are shared and the role of multilateral institutions. As this system for pandemic preparedness is being updated, it’s happening alongside the uncertainty of financing, institutional leadership and mandates and national commitments that would make it operate.  

READ:

Aftershocks Roundtable: How do we rebuild our HIV and public health infrastructure?

Who controls the data that makes AI possible, and who benefits from it?

Register

What We’re Reading

Global Health Watch: White House Drops NIH Review Plan, NIAID Reorg Moves Fwd, Prep for Generic LEN Access, Accra Reset

Issue 87

There is no shortage of global health news this week. Against the backdrop of the UN General Assembly (UNGA 81), this issue covers efforts to reshape the global health architecture through the Accra Reset, proposed and withdrawn Executive Orders affecting NIH grant making, NIAID restructuring developments, and preparations to expand access to generic lenacapavir for PrEP.

White House Drops NIH Review Plan and NIAID Reorganization Moves Forward 

In response to significant opposition from advocates, researchers, scientific institutions and members of the US Congress, the White House withdrew plans to issue an Executive Order (EO) that would have created an ‘external review committee’ with decision-making power over billions of congressionally-appropriated biomedical research dollars. The EO would have marked a significant overstep by politicizing NIH grantmaking review to fit ideology and in opposition of a process historically based on scientific merit and rigor. The review committee would have included political appointees, including Office of Management and Budget (OMB) Director Russell Vought.  

The reversal of this plan came just as the NIAID Council and AIDS Research Advisory Committee (ARAC) met Wednesday to discuss the proposed reorganization of NIAID that would eliminate the Division of Clinical Research and redistribute clinical research functions across the Institute. This proposal to fundamentally change the US biomedical research enterprise under which federally funded HIV research occurs was open for public comment for a mere five days. AVAC delivered a public comment at the meeting, raising concerns about the potential disruption to HIV research, global research partnerships and community engagement, and urging NIH to withdraw the proposal, provide greater transparency and meaningful opportunities for community input, and immediately release delayed funding opportunities for the HIV Clinical Trials Networks and Centers for AIDS Research. 

IMPLICATIONS: The White House’s decision not to move forward with the EO to establish an external review committee is one step in reducing greater political control over NIH grantmaking, and an example of advocacy and bipartisan congressional oversight in pushing back against political interference. However, the NIAID reorganization, delays in critical HIV research funding opportunities and disputes over how NIH grants are reviewed and funded are continuing. As US Senator Patty Murray (D-WA) and ranking member on Senate Appropriations said, “Whether lifesaving medical research gets funded or not should be determined by experts at the NIH—not a panel of lackeys…,” as she underscored the need for stronger statutory protections against political interference in research funding.

READ:

Global Fund Prepares for Generic Lenacapavir for HIV PrEP

The Global Fund announced Thursday that it is preparing for an expansion of lenacapavir for HIV PrEP (LEN) as milestones for generic introduction approaches. This builds on the two new agreements announced last week from Gilead Sciences, the developer of lenacapavir – one with the Pan American Health Organization (PAHO) to expand access to LEN in Latin America (although no clear volume or price was named) and the other to expand the six generic licenses to include the potential once-yearly option still in development (in addition to the current every six-months)—see last week’s Global Health Watch for more details.  

The Global Fund says it anticipates initial generic supply in late 2026 and wide scale availability in 2027, when it expects a significant acceleration in access to LEN. It also reiterated the goal, shared with PEPFAR, of reaching 3 million people with LEN by the end of 2028, and pointed to its existing expedited review and pooled procurement mechanisms as pathways for generics.  

IMPLICATIONS: While the announcement underscores growing demand for LEN and the importance of combining Gilead supply with generics to meet it beginning in 2027, it offers few new details about how or when that expansion will happen, including which generic manufacturers will supply product, expected volumes, pricing or specific next steps. Early implementation is already illustrating strong demand for LEN, which is outpacing available supply. AVAC previously forecasted that there could have been up to 1.5 million LEN users in 2026 in the top 16 LMIC PrEP markets – IF enough product had been procured – including 1.3 million in the 12 Global Fund and PEPFAR early adopter countries. And while the goal of reaching three million people over three years with LEN moves the rollout faster than previous PrEP options, as AVAC documented in July 2025, it does not meet the true demand for PrEP, nor will it deliver population-level impact. AVAC is pushing to accelerate orders and deliveries now, so that the three million LEN user target is achieved in two years, instead of three, in order to increase volumes, reduces price, build a durable market and sustain impact. Additionally, it is essential to build and strengthen prevention platforms now that can more quickly and efficiently integrate new products beginning in late 2027 and 2028 and avoid an innovation pile-up with the pipeline.  

READ:

The Accra Reset Shares Blueprint for a New Global Health Architecture 

On the sidelines of the UN General Assembly (UNGA) this week, a High-Level Panel of the Accra Reset launched its report, A Sovereign Future for Health – a 10-point blueprint for restructuring global health financing and governance. The Accra Reset, an initiative launched by Ghanaian President, John Dramani Mahama in 2025, calls for moving from aid dependence toward country-led financing and systems. The new blueprint makes the case for global health cooperation to be organized around priorities and capabilities defined by countries themselves rather than separate donor institutions and funding streams. The report’s ten recommendations include aligning partners behind one national health plan, budget and coordination platform; increasing domestic and pooled financing; strengthening regional research, manufacturing, regulatory and procurement capacity; and reforming global health institutions under a framework of “Commit, Collaborate, Consolidate and Close”. This includes potentially sunsetting institutions when their functions can be transferred elsewhere. Importantly, the report calls for a managed transition rather than abrupt withdrawal of international support. 

IMPLICATIONS: This blueprint comes as some organizations who have historically been at the center of the current global health architecture look ahead to their future. UNAIDS is considering significant reform, the Global Fund is determining its future with significantly reduced funding and selecting its next Executive Director, and Gavi is looking at ways for countries to finance more of their own health priorities. Notably, Global Fund Executive Director Peter Sands and Gavi CEO Sania Nishtar participated in the Accra Reset launch at UNGA, alongside the WHO and the Pandemic Fund. 

READ: 

AI + HIV Newsletter

Who controls the data that makes AI possible, and who benefits from it?

Read the September Issue

What We’re Reading

STIWatch September 2026 Newsletter

This quarter’s STIWatch newsletter looks at how advocates are turning evidence into action, from advancing country-led STI priorities and strengthening syndromic management to tracking new data, guidance and perspectives shaping STI prevention, diagnosis and care.

Read the Issue

Global Health Watch: LEN Access Pathways, NIAID Reorganization, Global Fund Report, NIH Lawsuit

Issue 86

This week’s issue covers developments shaping access to HIV prevention and the future of US biomedical research, including new pathways to accelerate access to lenacapavir for HIV PrEP, calls for greater transparency around a proposed NIAID restructuring, and a new lawsuit challenging NIH’s screening of research grants. With today as the final day to comment on the NIAID proposal, make your voice heard. And read on for a provocative Lancet commentary on the challenges of trying to reform global health architecture.

Lenacapavir Access Pathway

Two new agreements from Gilead Sciences, the developer of lenacapavir, this week could expand access to lenacapavir for HIV PrEP (LEN), both for the current every six month injectable and a potential once-yearly option still in development. Gilead and the Pan American Health Organization (PAHO) announced new steps to establish a procurement pathway through PAHO’s Regional Revolving Funds that will allow 14 countries in Latin America and the Caribbean – including Argentina, Brazil, Peru and Mexico (all of which participated in one of the pivotal efficacy trials) – to procure twice-yearly LEN. This mechanism complements the 24 countries already covered in the region by Gilead’s existing voluntary licensing agreements. Gilead also committed to advance a technology-transfer process in Brazil, although timelines, prices, and volumes were not defined in the release. Separately, Gilead expanded its six royalty-free voluntary licenses for lenacapavir to include the investigational once-yearly formulation being studied in the Phase 3 PURPOSE 365 trial. This would extend once-yearly LEN generic plans for 120 high-incidence, resource-limited countries before efficacy results or regulatory approval.

IMPLICATIONS: These LEN announcements are a step forward in rolling out new HIV prevention options with speed and scale, but equity continues to remain a central issue. Advocacy partners, ITPC Global and Make Medicines Affordable, welcomed the PAHO mechanism as an important step for countries that were initially excluded from Gilead’s voluntary licenses. However, they warned that important details including price, volumes, supply commitments and delivery timelines remain unknown and that governments cannot plan national scale-up without that information.

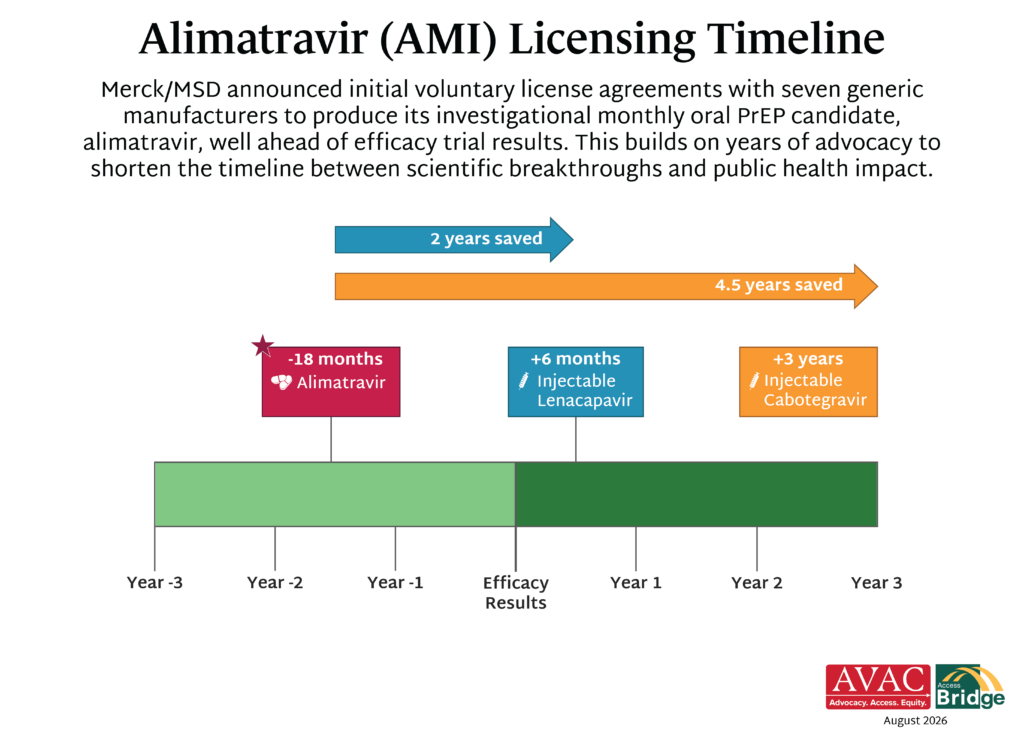
At the same time, expanding voluntary licenses to the prospective once-yearly formulation while it is still in Phase 3 development is an important step forward in early access planning and could shorten the gap between approval and generic supply, should the once-yearly formulation prove safe and effective. This early licensing approach mirrors Merck/MSD’s recent licensing agreements for their investigational monthly oral PrEP option, alimatravir. AVAC’s projections of potential LEN supply and demand through 2028 illustrate the scale of the opportunity—and the gap that remains between potential demand and current commitments. Whether these two LEN access agreements translate into affordable, predictable supply that countries can actually finance and deliver at scale and speed will be the true test of equity.

READ:

NIAID Reorganization: Last Day for Public Comment 

Advocates led by the Save HIV Funding campaign, founded by PrEP4All, HIVMA and AVAC, are demanding more transparency and a withdrawal of the proposed restructuring of the National Institute of Allergy and Infectious Diseases (NIAID) to allow time for meaningful opportunities for the HIV community to provide input on the reorganization proposal. Last week, the National Institutes of Health (NIH) released a proposed reorganizational chart with public comments due today, September 18. The proposal would eliminate NIAID’s Division of Clinical Research and redistribute clinical research functions across the Institute. Little accompanying detail has been provided about the rationale for the changes, how responsibilities would be reassigned or what the restructuring could mean for NIAID’s domestic and international clinical research infrastructure.  
 
The Save HIV Funding campaign developed a template for comments for individuals and organizations that would like to comment on the NIH proposed reorganization of NIAID.

IMPLICATIONS: The proposed restructuring comes at a particularly uncertain moment for the HIV research infrastructure NIAID has built over decades. The long-delayed announcement for the next seven-year cycle of the trial networks creates the possibility of funding gaps that could disrupt ongoing trials, research sites, staff and study participants; infectious-disease groups have warned that lapses could destabilize research capacity that has contributed to advances across HIV, TB, hepatitis and other infectious diseases. With fundamental questions about the reorganization still unanswered, advocates are pressing NIH not to restructure that system without greater transparency and meaningful community input. The uncharacteristically shortened timeline for public comment and scant details available about the proposed reorganization has been criticized as obfuscating meaningful community engagement and involvement in NIAID processes. Furthermore, NIAID has provided little justification for eliminating pertinent divisions such the Division of Clinical Research – which provides substantial clinical and regulatory support for NIAID-funded studies.  

READ:

Global Fund Releases New Report: Treatment Sustained, Prevention Impacted

The Global Fund to Fight AIDS, TB and Malaria released its 2026 Results Report, which positions sustained progress against all three diseases in 2025 despite the decimation of global health foreign assistance and financing. In Global Fund invested countries, the report shows that 26.9 million people received antiretroviral therapy for HIV, which is an increase from 25.6 million in 2024. However, despite sustainability of treatment, the report also documents the effects on prevention where programs were scaled back or suspended altogether in some countries. Notably, the number of people receiving PrEP in Global Fund-supported countries fell from 1.4 million in 2024 to 1.1 million in 2025

IMPLICATIONS: These findings suggest a similar pattern across recent analyses of the global HIV response, including the recent UNAIDS report and latest PEPFAR data. HIV treatment programs have so far proved relatively resilient to the funding pitfalls, while HIV prevention has been much more severely disrupted. AmfAR’s Brian Honerman and co-authors, Jirair Ratevosian, KFF and AVAC’s own analysis of the latest PEPFAR data, all sound the alarm that the front end of the HIV response is weakening.

READ:

Scientists Sue NIH Over Grant Screening Process 

Seventeen US researchers filed a class-action lawsuit challenging a new National Institutes of Health (NIH) grant-screening process that they say unlawfully allows political considerations to override scientific merit. According to the complaint, NIH is using a computational tool to flag at least 235 terms—including “gender,” “health disparities,” “racist” and “climate change”—in new and existing grants, and in some cases requiring researchers to remove or change flagged language before funding can proceed. The lawsuit alleges that the process violates First Amendment protections against viewpoint discrimination as well as federal requirements governing how NIH awards and terminates grants. They are asking the court to halt the screening policy, restore terminated grants and reconsider applications denied under the process.  

IMPLICATIONS: The lawsuit represents a new legal challenge to the Administration’s efforts to reshape federally funded research. Following the mass grant terminations in early 2025, this evolution of political overstep is being played out in a new way. The 17 researchers argue that requiring scientists to remove terms related to populations or subjects they are studying can alter how research is described and, in some cases, undermine its scientific design. Because this lawsuit is filed as a class action, its implications could extend beyond their specific grants and to researchers around the country affected by the screening policy. This new challenge follows AVAC’s lawsuit, which unlocked the payment of millions of dollars of development assistance for work that was done in January and February 2025. 

READ:

Webinar: What’s Next for bNAbs?

On September 30, join AVAC for a global webinar: Combo bNAbs for HIV Prevention – Latest Developments.

Register

What We’re Reading

All things alimatravir (AMI)

Alimatravir (AMI, known as MK-8527) is an investigational monthly pill being studied for PrEP in the EXPrESSIVE program. The addition of a monthly PrEP pill, if proven safe and effective in the EXPrESSIVE trials, will expand the number of prevention options and open the door to new and innovative delivery models.

AVAC and partners have been engaging with Merck/MSD since the very start of the Alimatravir product development program and helped conceptualize the EXPrESSIVE efficacy trial design. Building on this foundation of community-centricity, advocates can now push for AMI to be rolled out with speed, scale and equity. Since 2012, each successive PrEP introduction has gone faster than the previous one, yet the time to market and to public health impact for PrEP remains too slow. Read on for AVAC’s insights on AMI, from accelerated licensing and affordability to community priorities and meaningful engagement.

The Latest on AMI

Just before the AIDS 2026 conference in July, AMI developer Merck/MSD granted seven direct licenses to generic manufacturers to produce and market the drug in 129 low- and middle-income countries, including all of Africa and much of Asia, while the trials are still enrolling. These agreements are in place 18 months before a possible efficacy result, and substantially earlier than for lenacapavir or cabotegravir. If AMI is found safe and effective, these agreements could greatly accelerate the introduction process. AVAC and Access Bridge welcomed the announcement, highlighting the challenges that remain to ensure future access is equitable and widespread among the populations that need it most.  

While overall good news, several countries that are hosting the EXPrESSIVE 11 trial are left out of the voluntary license territory, reflecting a broader trend of ;excluding Latin American countries and some Asian countries from voluntary licenses. Merck/MSD did subsequently sign a memorandum of understanding with Fiocruz, a Brazilian manufacturer, to supply AMI for Brazil and the region, but the terms, timing and next steps remain unclear. Furthermore, key populations in high-income countries also face access disparities.

Find all the latest updates on AVAC’s alimatravir page.

PxWire Explores AMI Generic Licensing Agreements

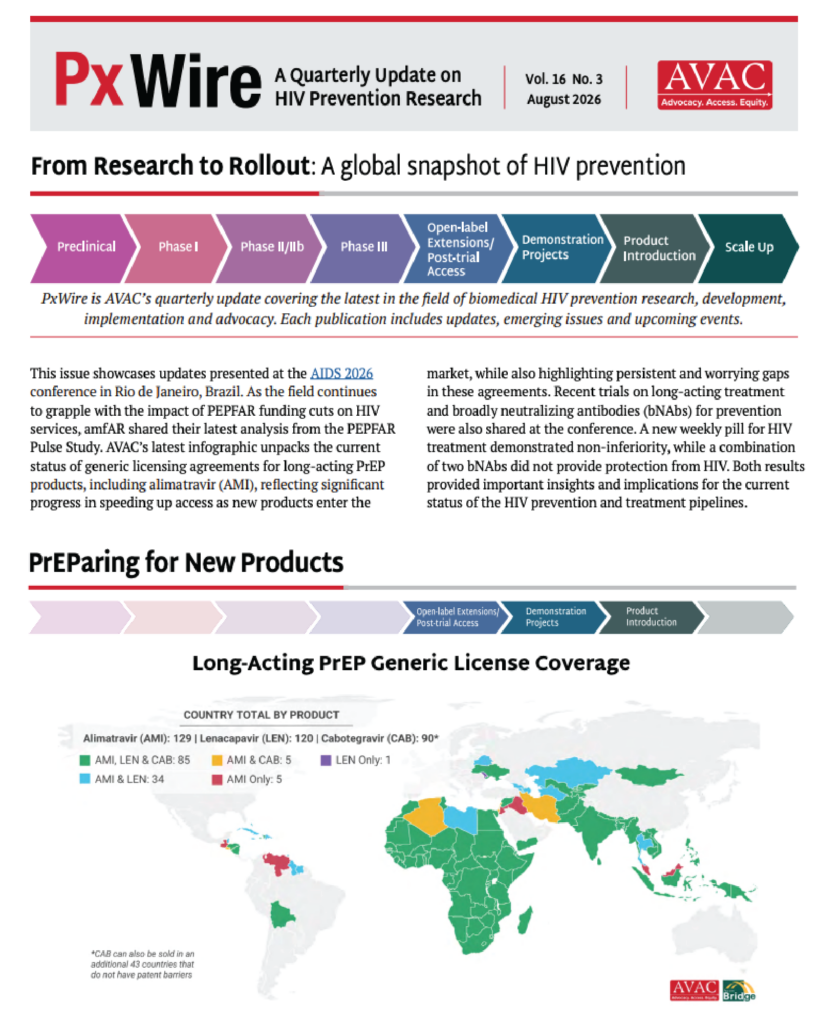
AVAC’s latest edition of PxWire features an analysis of generic licensing for AMI and what it means for the field, and an explainer on generic licensing agreements and current coverage across long-acting prevention products. The explainer examines the promise of generics for advancing affordable, equitable access and raises questions about the persistent and worrying gaps in these agreements. 

Read the latest edition of PxWire.

AMI Could Be the Cheapest HIV Prevention Option Yet, But Does Affordable Mean Accessible? 

Photo credit: aidsmap

A new academic analysis presented at AIDS 2026 suggests that AMI could be manufactured at large scale by generic companies and sold for as low as $3 per person per year, and a separate New York Times report highlighted estimates that generic AMI could be sold to national health systems for as little as $5 per person per year. But an affordable product is only impactful if people can access it. As the Gates Foundation’s Max Lataillade said in an AVAC satellite session at AIDS 2026, “Innovation without global access or implementation does not create the impact that we want. Science creates the possibility, collaboration creates the impact, but communities create the future.”

Read AVAC’s coverage of the AMI modeling data presented at AIDS2026.

From Research to Access: Community Statement from the Global Community Advisory Group (GCAG) on the Future of Alimatravir for HIV Prevention 

Following Merck/MSD’s generic licensing announcement for AMI, the EXPrESSIVE-10 Global Community Advisory Group (GCAG) released a statement on community perspectives and priorities around prevention choice, meaningful community engagement, equitable access and ensuring that communities have a voice as research progresses toward potential introduction. As the GCAG writes, “The test is now whether early planning can translate into faster, more equitable action. An access plan is valuable not because it is announced, but because it creates a pathway that can be tracked, challenged, and delivered.” 

Read the EXPrESSIVE-10 GCAG statement.

Putting Communities at the Center of EXPrESSIVE 

The EXPrESSIVE program includes two phase 3 efficacy trials studying AMI for HIV prevention—EXPrESSIVE-10 among cisgender women and EXPrESSIVE-11 among cisgender men who have sex with men, transgender men, transgender women and gender non-binary individuals. The trials are anticipated to have results in the latter half of 2027. With support from the Gates Foundation, AVAC is supporting strong, consistent community engagement across the program. As a part of this work, AVAC partnered with community-based organizations in Argentina, Brazil, Kenya, Peru, the Philippines, South Africa, Thailand and Vietnam to develop educational materials for EXPrESSIVE-11 through a participatory human-centered design (HCD) process. Luciana Kamel, the Community Education Team Lead for HIV studies at Fiocruz, AVAC’s partner in Brazil for this work, described how this approach changed what was possible: “The trust, openness and respect for our work with the community made it possible to move beyond simply producing recruitment materials and instead build something that reflected the people and contexts the study was intended to engage.”  

Learn more about community-led design in EXPrESSIVE-11.

Check out all the communications materials here.

Additional AMI Resources